Related Experiment Video
Updated: Apr 14, 2026


Echocardiographic Approaches and Protocols for Comprehensive Phenotypic Characterization of Valvular Heart Disease in Mice
Published on: February 14, 2017
Evaluation of aortic stenosis: an update--including low-flow States, myocardial mechanics, and stress testing
Luc A Pierard1, Raluca Dulgheru
1Department of Cardiology, CHU Sart Tilman, University of Liege, 4000, Liege, Belgium, lpierard@chu.ulg.ac.be.

Abstract:
Degenerative aortic stenosis (AS) is one of the most frequent valvular heart diseases in Western countries. Echocardiography plays a central role in the evaluation and management of patients with AS. To overcome the inherent inconsistencies between the echocardiographic parameters defining severe AS and to unify concepts, a new classification based on the interplay between flow and gradients has recently been adopted. Outcome studies of asymptomatic patients with preserved left ventricular ejection fraction (LVEF), as classified by this new approach, have shown that low-flow (LF) states are associated with poor outcome, that the classical normal-flow/high-gradient pattern has an intermediate outcome, while normal-flow/low-gradient severe AS seems to have an outcome comparable to moderate AS and such patients do not benefit from aortic valve replacement. Patients with LF/low-gradient severe AS with preserved LVEF, also known as "paradoxical LF/low-gradient AS," have the worst outcome and benefit greatly from surgical or percutaneous valve replacement, provided that severity is proven. In patients with LF/low-gradient and depressed LVEF, dobutamine stress echocardiography has an important role to distinguish severe from pseudo-severe AS and to assess surgical risk. Assessment of aortic valve calcium score, as well as computation of projected effective orifice aortic area at normal trans-valvular flow rates, has proved to be very useful to distinguish severe from pseudo-severe AS in LF/low-gradient AS with both reduced and preserved LVEF. Asymptomatic patients with normal flow/gradient should be submitted to an exercise test; exercise echocardiography can identify patients at increased risk when mean gradient increases by >18-20 mmHg and/or pulmonary arterial hypertension develops during exercise.
More Related Videos
 06:39
Ultrasound Based Assessment of Coronary Artery Flow and Coronary Flow Reserve Using the Pressure Overload Model in Mice
Published on: April 13, 2015
 09:24
O-Ring Aortic Banding Versus Traditional Transverse Aortic Constriction for Modeling Pressure Overload-Induced Cardiac Hypertrophy
Published on: October 6, 2022
Related Concept Videos
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:27
Mitral Stenosis IV: Nursing Management
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:26
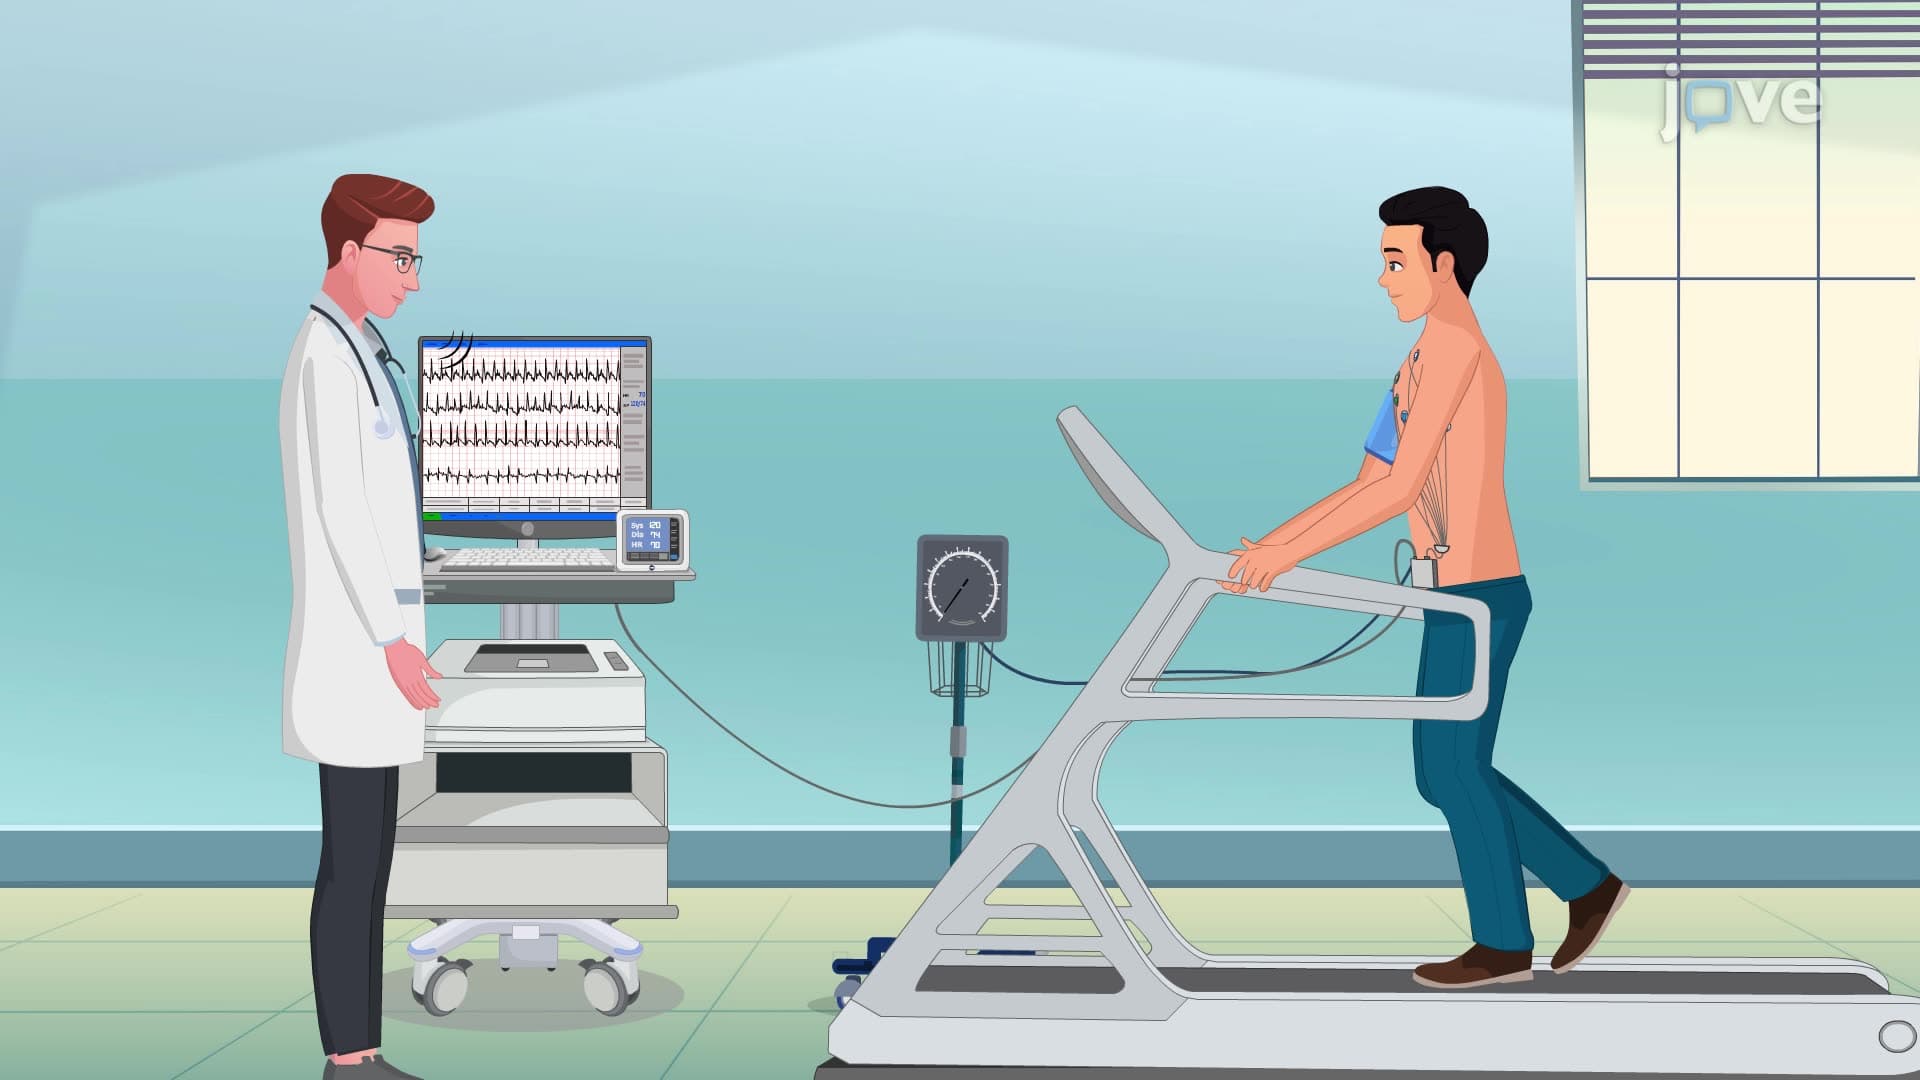
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes