Related Experiment Video
Updated: Apr 14, 2026
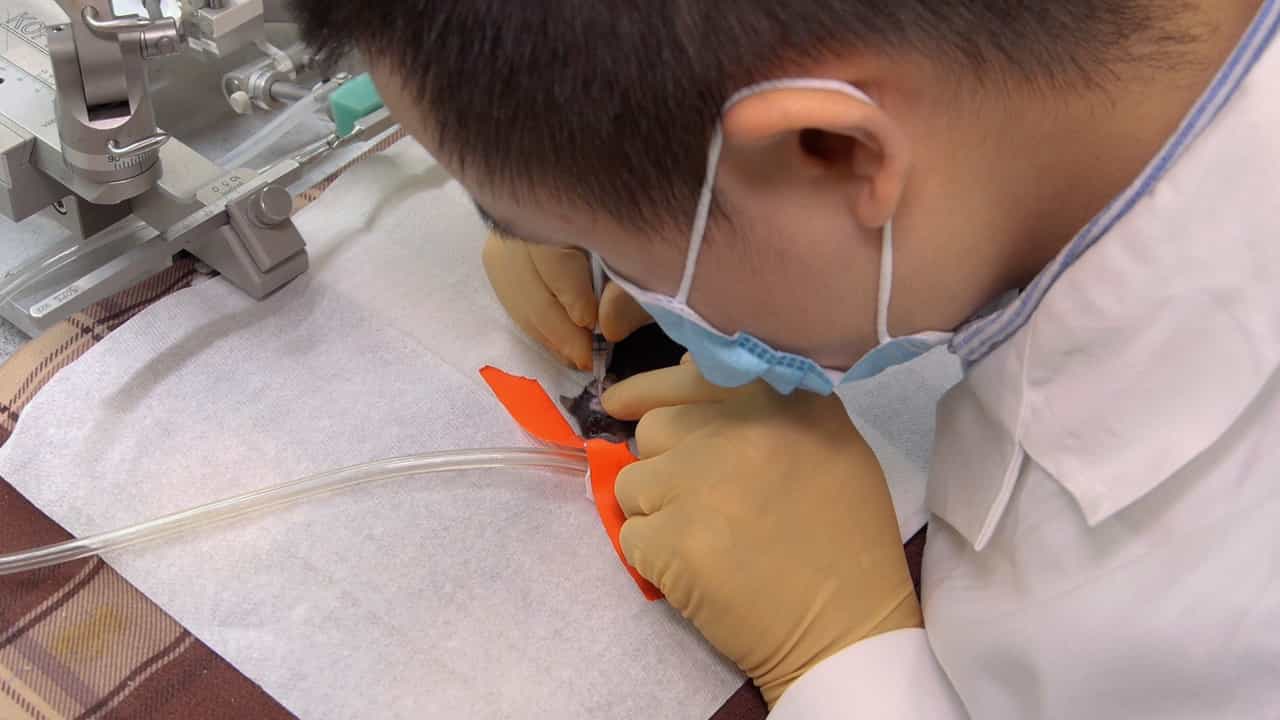

Temporomandibular Joint Pain Measurement by Bite Force and Von Frey Filament Assays in Mice
Published on: September 13, 2024
Hypnosis/Relaxation therapy for temporomandibular disorders: a systematic review and meta-analysis of randomized

Aims:
To conduct a systematic review and meta-analysis to evaluate the effectiveness of hypnosis/relaxation therapy compared to no/minimal treatment in patients with temporomandibular disorders (TMD).
Methods:
Studies reviewed included randomized controlled trials (RCTs) where investigators randomized patients with TMD or an equivalent condition to an intervention arm receiving hypnosis, relaxation training, or hyporelaxation therapy, and a control group receiving no/minimal treatment. The systematic search was conducted without language restrictions, in Medline, EMBASE, CENTRAL, and PsycINFO, from inception to June 30, 2014. Studies were pooled using weighted mean differences and pooled risk ratios (RRs) for continuous outcomes and dichotomous outcomes, respectively, and their associated 95% confidence intervals (CI).
Results:
Of 3,098 identified citations, 3 studies including 159 patients proved eligible, although none of these described their method of randomization. The results suggested limited or no benefit of hypnosis/relaxation therapy on pain (risk difference in important pain -0.06; 95% CI: -0.18 to 0.05; P = .28), or on pressure pain thresholds on the skin surface over the temporomandibular joint (TMJ) and masticatory muscles. Low-quality evidence suggested some benefit of hypnosis/relaxation therapy on maximal pain (mean difference on 100-mm scale = -28.33; 95% CI: -44.67 to -11.99; P =.007) and active maximal mouth opening (mean difference on 100-mm scale = -2.63 mm; 95% CI: -3.30 mm to -1.96 mm; P < .001) compared to no/minimal treatment.
Conclusion:
Three RCTs were eligible for the systematic review, but they were with high risk of bias and provided low-quality evidence, suggesting that hypnosis/relaxation therapy may have a beneficial effect on maximal pain and active maximal mouth opening but not on pain and pressure pain threshold. Larger RCTs with low risk of bias are required to confirm or refute these findings and to inform other important patient outcomes.


Related Concept Videos
 01:24
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...
 01:29
Relaxation of Skeletal Muscles
When an action potential reaches the axon terminal, it depolarizes the membrane and opens voltage-gated sodium channels. Sodium ions enter the cell, further depolarizing the presynaptic membrane. This depolarization causes voltage-gated calcium channels to open....
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:23
Sedatives and Hypnotics: Overview
Sedative-hypnotics are categorized into barbiturates, benzodiazepines (BZDs), and non-benzodiazepines or Z-drugs. These drugs work by suppressing central nervous system activity, and this suppression is dose-dependent. Older sedative medications, like barbiturates, follow a linear curve in...
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
 01:19
Sedatives and Hypnotics Drugs: Benzodiazepines
Benzodiazepines work by enhancing the effects of the inhibitory neurotransmitter GABA. They bind to the GABAA receptor, increasing its affinity for GABA, which opens chloride...