Craniofacial fellowship training: where are we now?
Related Experiment Video
Updated: Apr 14, 2026
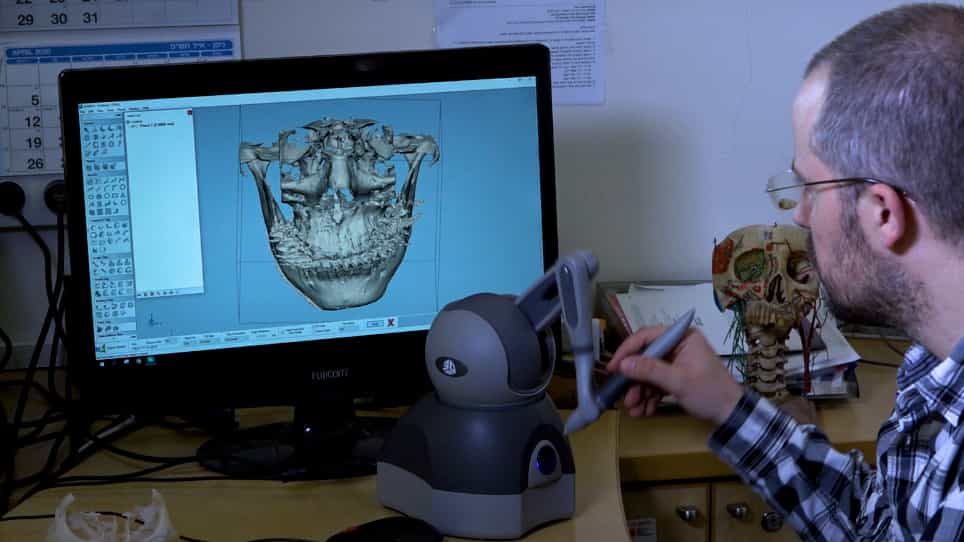
Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Niyant Patel1, Kanlaya Dittakasem, Jeffrey A Fearon
1Akron, Ohio; and Dallas, Texas From the Craniofacial Clinic and Plastic and Reconstructive Surgery Center at Akron Children's Hospital; the Medical City Children's Hospital; and The Craniofacial Center.

Background:
The authors sought to evaluate current craniofacial training in the United States to achieve perspective on changes over time and to gain insights into possible process improvements.
Methods:
Following a review of the San Francisco Match listings and an Internet search, an anonymous online survey invitation was sent to all fellows finishing in 2013.
Results:
Thirty-three fellows were identified in 29 listed programs and 30 responded (91 percent). All had completed plastic surgery training. A mean caseload of 380 cases (95 percent CI, 307 to 452) was reported. Case analyses permitted subclassification of fellowships into five areas of relative strengths: cleft/intracranial/midface, 35 percent; cleft/general pediatrics, 20 percent; cleft/adult plastics, 20 percent; cleft/facial trauma, 15 percent; and adult plastics/facial trauma, 10 percent of programs. Eighty-six percent were residency-type programs, whereas only 14 percent remained apprenticeships. Fellows cited confidence in any procedure following participation in more than 12 cases, but 20 percent reported not feeling adequately trained following fellowship. Over half (52 percent) thought training could be improved by establishing core areas of exposure and case category minimums.
Conclusions:
Fellowships identified as "craniofacial" are actually fairly heterogeneous, offering diverse clinical experiences. Currently, only a minority emphasize traditional cleft, intracranial, and midfacial procedures, with the majority focused more on cleft care, general pediatric plastic surgery, and trauma. Concomitant with an increase in fellowship-trained surgeons has come a change in program structure from apprenticeships to residency-type models. Prospective fellows should consider matching their individual training goals with each program's unique clinical strengths.
Related Concept Videos
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:08
Overview of the Skull
The cranial vault surrounds and protects the brain and houses the middle and inner ear structures. This cavity is bounded superiorly by the rounded top of the skull, which...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:21
Association Areas of the Cortex
Prefrontal Association Area: This area is located in the frontal lobe and is involved in planning, decision-making, and moderating social behavior. It connects with primary motor areas,...
 01:14
Muscles for Facial Expressions
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...