Effectiveness of CT for the detection of glenoid bone graft resorption following reverse shoulder arthroplasty
Related Experiment Video
Updated: Apr 13, 2026
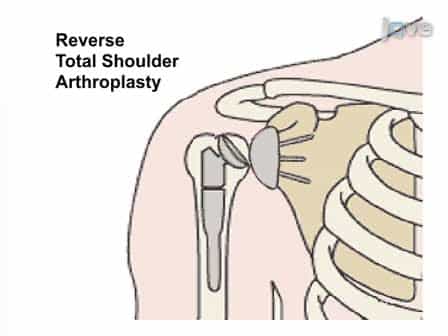
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
L M Ferreira1, N K Knowles2, D N Richmond3
1Roth|Mcfarlane Hand and Upper Limb Centre, Surgical Mechatronics Laboratory, St. Josephs Health Care, London, ON, Canada; Department of Mechanical and Materials Engineering, University of Western University, London, ON, Canada; Schulich School of Medicine and Dentistry, University of Western University, London, ON, Canada.

Introduction:
Glenoid bone grafting is often used in cases of reverse shoulder arthroplasty (RSA) with glenoid deficiency. Additionally, bony increased-offset RSA (BIO-RSA) uses a cylindrical bonegraft harvested from the humeral head and is positioned beneath the glenoid baseplate to increase lateralization. Postoperative computed tomography (CT) has been used to detect glenoid bonegraft resorption, which is typically identified by a gap between the bonegraft and baseplate; however, CT images are often degraded by implant metal artifact. The purpose of this CT imaging study was to determine if a simulated bonegraft resorption gap is detectable following RSA with glenoid bone grafting.
Hypothesis:
CT is unable to detect bone graft resorption following reverse shoulder arthroplasty conducted with bone grafting beneath the glenoid baseplate.
Materials And Methods:
RSA with glenoid bone grafting was performed on four cadaver shoulders. Glenoid bonegraft resorption gaps were simulated by fixing the implant at six different gap widths (0, 1, 2, 4, 6 and 8mm). Clinical CT scans were acquired for each gap resulting in 6 scans per specimen. Two experienced observers (blinded) analyzed DICOM images in the axial and coronal directions, and measured gap widths using Mimics(®) software. Each observer had access to approximately 200 images per condition per specimen.
Results:
The sensitivity of CT imaging to positively identify bonegraft resorption was 38%, with an accuracy of 46%. Inter-observer agreement was 92%. Observers tended to visualize no-gap for most conditions. Resorption gap width measurements were consistently underestimated.
Discussion:
Metal artifact prevented identification of simulated bonegraft resorption gaps and observers most often determined that there was bonegraft-to-implant "healing" on CT, when in fact a gap was clinically present. This study illustrates the need for more effective imaging techniques to determine if bonegraft resorption has occurred following RSA.