Related Experiment Video
Updated: Apr 13, 2026

Deep Neuromuscular Blockade Leads to a Larger Intraabdominal Volume During Laparoscopy
Published on: June 25, 2013
Influence of different body positions in vital capacity in patients on postoperative upper abdominal
Bruno Prata Martinez1, Joilma Ribeiro Silva2, Vanessa Salgado Silva3
1Hospital Aliança, Salvador, BA, Brazil; Escola Baiana de Medicina e Saúde Pública (EBMSP), Salvador, BA, Brazil; Faculdade Social da Bahia (FSBA), Salvador, BA, Brazil.

Rationale:
The changes in body position can cause changes in lung function, and it is necessary to understand them, especially in the postoperative upper abdominal surgery, since these patients are susceptible to postoperative pulmonary complications.
Objective:
To assess the vital capacity in the supine position (head at 0° and 45°), sitting and standing positions in patients in the postoperative upper abdominal surgery.
Methods:
A cross-sectional study conducted between August 2008 and January 2009 in a hospital in Salvador/BA. The instrument used to measure vital capacity was analogic spirometer, the choice of the sequence of positions followed a random order obtained from the draw of the four positions. Secondary data were collected from the medical records of each patient.
Results:
The sample consisted of 30 subjects with a mean age of 45.2 ± 11.2 years, BMI 20.2 ± 1.0 kg/m(2). The position on orthostasis showed higher values of vital capacity regarding standing (mean change: 0.15 ± 0.03 L; p=0.001), the supine to 45 (average difference: 0.32 ± 0.04 L; p = 0.001) and 0° (0.50 ± 0.05 L; p = 0.001). There was a positive trend between the values of forced vital capacity supine to upright posture (1.68 ± 0.47; 1.86 ± 0.48; 2.02 ± 0.48 and 2.18 ± 0.52 L; respectively).
Conclusion:
Body position affects the values of vital capacity in patients in the postoperative upper abdominal surgery, increasing in postures where the chest is vertical.
More Related Videos
 04:48
Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
 05:39
Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
Related Concept Videos
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:15
Respiratory Volumes
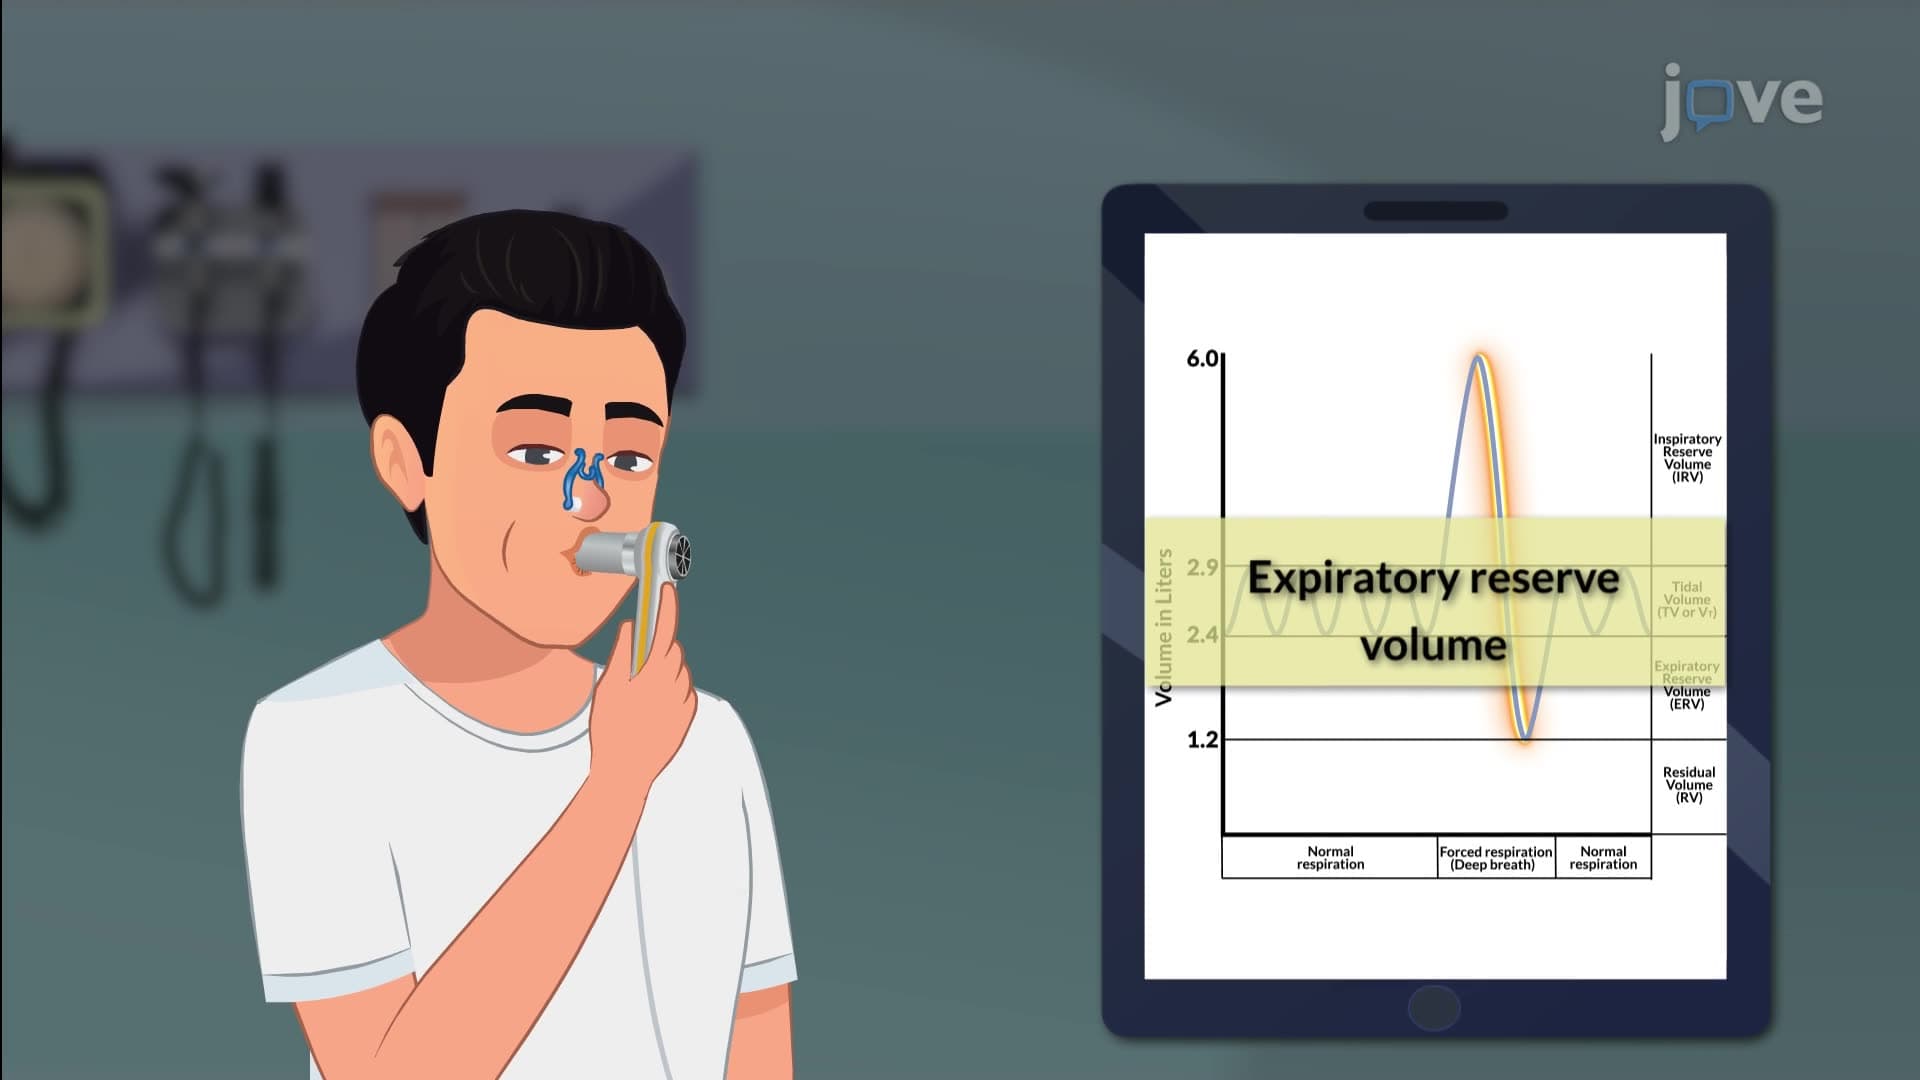
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: