Related Experiment Video
Updated: Apr 13, 2026
Fertility Preservation Through Oocyte Vitrification: Clinical and Laboratory Perspectives
Published on: September 16, 2021
Individualized recombinant human follicle-stimulating hormone dosing using the CONSORT calculator in assisted
Olaf Gj Naether1, Andreas Tandler-Schneider2, Wilma Bilger3
1Reproductive Endocrinology, MVZ Fertility Center Hamburg, Hamburg, Germany.

Purpose:
This postmarketing surveillance survey was conducted to investigate the utility of the CONsistency in r-FSH Starting dOses for individualized tReatmenT (CONSORT) calculator for individualizing recombinant human follicle-stimulating hormone (r-hFSH) starting doses for controlled ovarian stimulation (COS) in routine clinical practice.
Methods:
This was a 3-year, open-label, observational study evaluating data from women undergoing COS for assisted reproductive technology at 31 German fertility centers. Physicians stated their recommended r-hFSH starting dose, then generated a CONSORT-recommended r-hFSH starting dose. Physicians could prescribe any r-hFSH starting dose. The primary objective was to compare the r-hFSH starting dose recommended by the physician with the CONSORT-calculated dose and that prescribed. Statistical analyses were conducted post hoc.
Results:
Data were collected from 2,579 patients; the mean (standard deviation [SD]) age was 30.5 (2.93) years (range: 19-40 years). The mean (SD) CONSORT-calculated r-hFSH starting dose was significantly lower than the physician-recommended dose (134.5 [38.0] IU versus 164.6 [47.1] IU; P<0.0001); the mean (SD) starting dose prescribed was 162.2 (48.4) IU. CONSORT-calculated doses were prescribed for 27.3% (number [n] =677) of patients, and non-CONSORT-calculated doses prescribed for 72.7% (n=1,800). The mean (SD) number of oocytes retrieved per patient was 10.6 (6.15) and 11.4 (6.66) in the CONSORT and non-CONSORT groups, respectively; the mean (SD) number of embryos transferred per patient was 1.98 (0.41) and 2.03 (0.45), respectively. Clinical pregnancy rates per COS cycle were 38.8% (CONSORT) and 34.8% (non-CONSORT) (P=0.142); clinical pregnancy rates per embryos transferred were 45.0% and 39.5%, respectively (P=0.049). Miscarriage occurred in 14.8% of all clinical pregnancies (
Consort:
12.5%; non-
Consort:
15.3%). The rate of grade 3 ovarian hyperstimulation syndrome (OHSS) was 0.3% (n=2) in the CONSORT group and 0.6% (n=11) in the non-CONSORT group. OHSS led to hospitalization in 0.81% (n=21) of cases (CONSORT group: 0.74% [n=5]; non-CONSORT group: 0.83% [n=15]).
Conclusion:
Physician-recommended r-hFSH starting doses were generally higher than those calculated by CONSORT; most patients were prescribed a higher starting dose than that recommended by CONSORT.
More Related Videos
 05:32
Author Spotlight: Investigating the Relationship Between FSH and Pathophysiological Changes in Perimenopausal Women - Insights from a Mouse Model
Published on: August 11, 2023
 06:40
Collection of Human Follicular Fluid, Follicle Somatic Cells, and Immature Oocytes from Individuals Undergoing In Vitro Fertilization
Published on: October 24, 2025
Related Concept Videos
 01:24
In Vitro Fertilization
The IVF process begins with ovarian stimulation, during which reproductive endocrinologists prescribe hormonal medications to stimulate the ovaries to produce multiple eggs instead of the single...
 01:01
Dosage Regimen: Fixed Dose
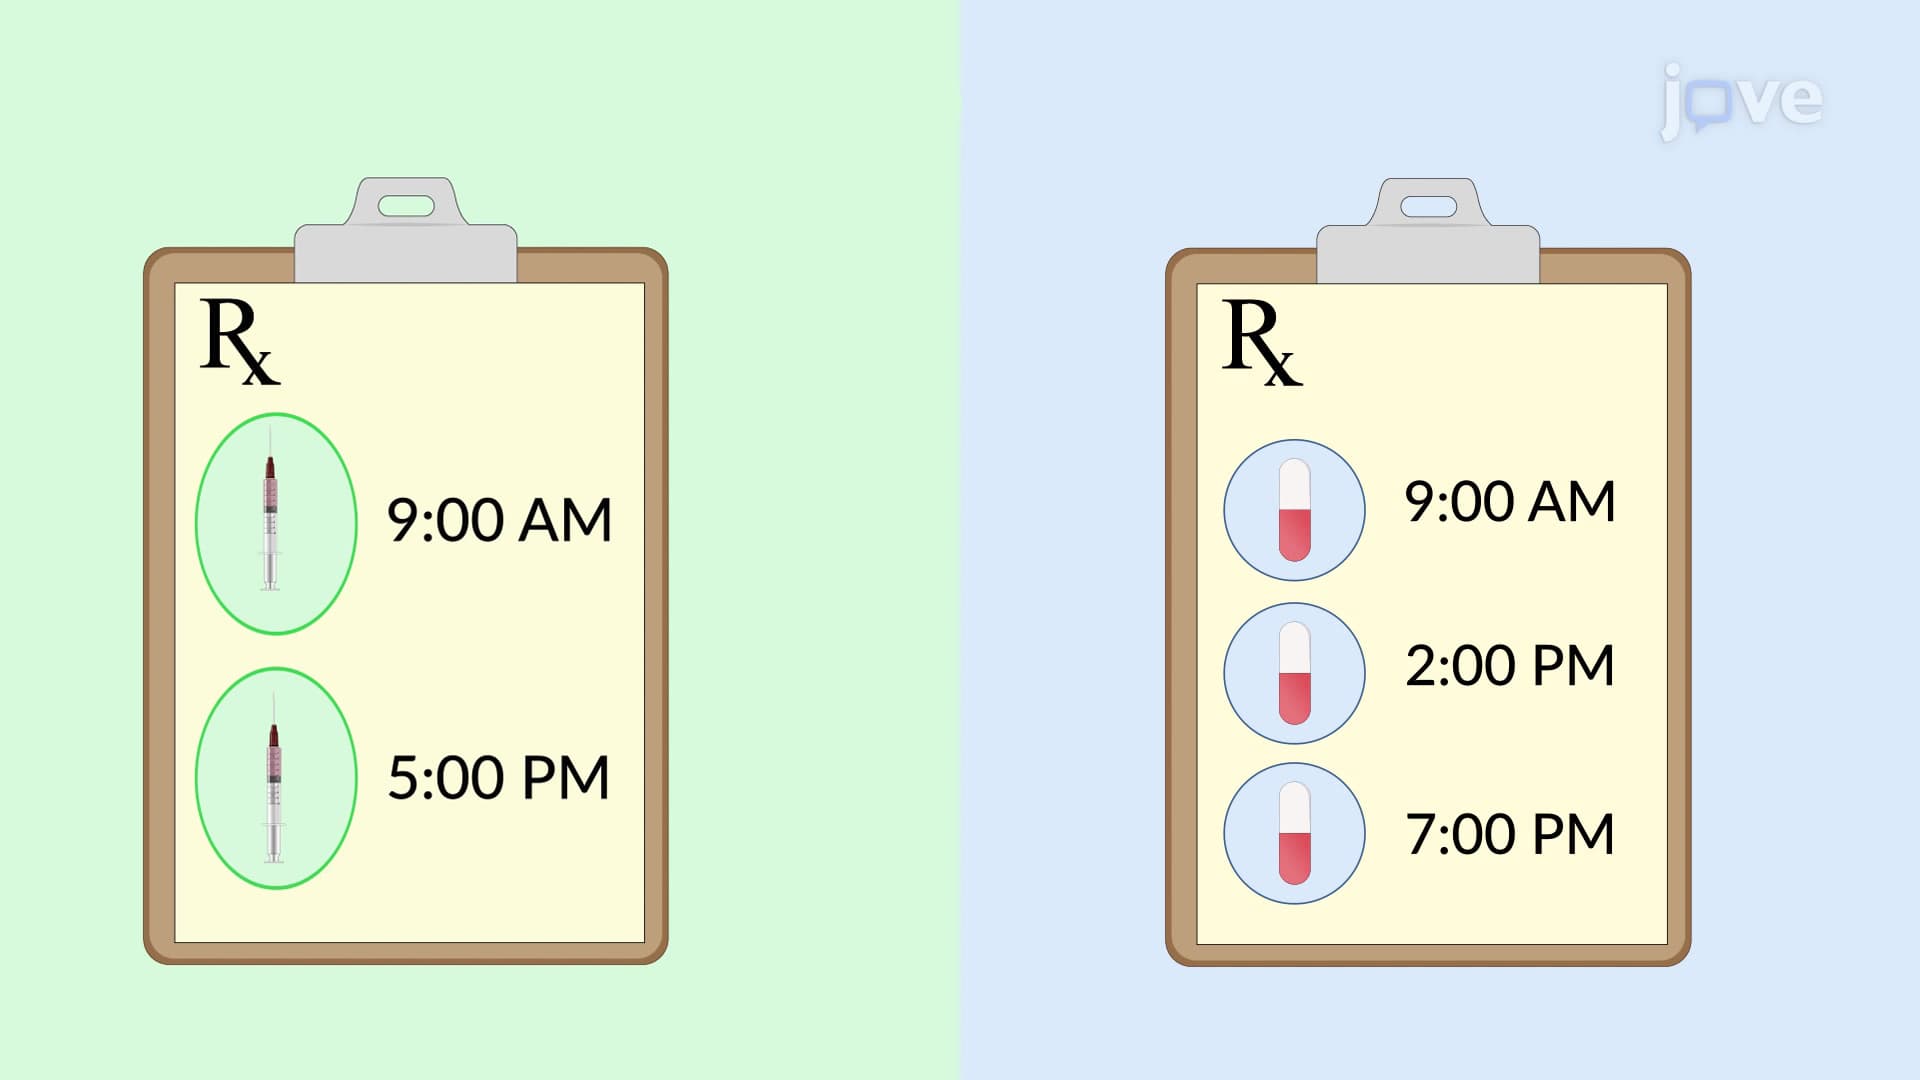
Fixed-dose regimens can be used for various routes of administration, including intravenous (IV) injections and oral medications. For IV administration, a predetermined amount of the drug is...
 01:28
Dosage Regimens: Designs and Approaches
 01:24
Dosage Regimen: Individualization
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses