Related Experiment Video
Updated: Apr 13, 2026
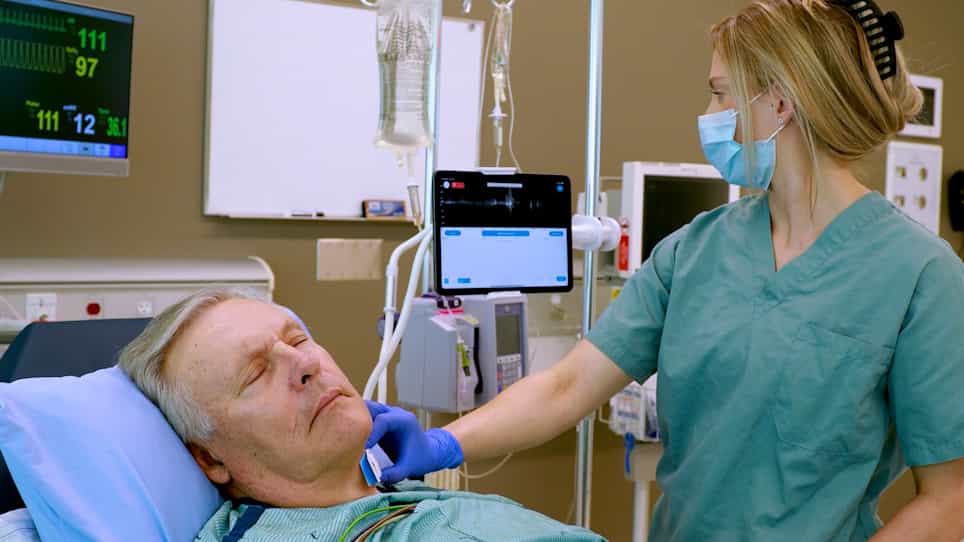

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Effects of stroke volume variation, pulse pressure variation, and pleth variability index in predicting fluid
Yu Chen1, Qiang Fu1, Wei-dong Mi1
1Anesthesia and Operation Center, Chinese PLA General Hospital, Beijing 100853, China.

Objective:
To investigate the effects of different positive end expiratory pressures (PEEP) on functional hemodynamic parameters in patients lying in prone position during operation under general anesthesia.
Methods:
Totally 60 patients undergoing cervical vertebra operation or lumbar vertebra operation were studied. All patients were also monitored with Vigileo/FloTrac system. The functional hemodynamic parameters including stroke volume variation (SVV), pulse pressure variation (PPV), and pleth variability index (PVI) under PEEP levels of 0 mmHg, 5 mmHg, 10 mmHg, and 15 mmHg were recorded before and after volume expansion (hydroxyethyl starch 6%,7 ml/kg). Fluid responsiveness was defined as an increase in stroke volume index (SVI) ≥ 15%(△SVI ≥ 15%). Responders were defined as patients demonstrating an increase in SVI ≥ 15% after intravascular volume expansion and non-responders as patients whose SVI changed <15%. Receiver operating characteristic (ROC) curves were generated for SVV, PPV, and PVI under different PEEP levels to determine their diagnosis accuracies and thresholds and their potential correlations.
Results:
In the prone position, SVV, PPV, and PVI were significantly higher compared to those in the supine position (P<0.05) and the mean arterial pressure significantly decreased (P<0.05); however, the changes of heart rate, stroke volume, SVI, cardiac output, and cardiac index showed no significant difference (P>0.05). In the prone position, along with the elevation of PEEP (0 mmHg, 5 mmHg, 10 mmHg, and 15 mmHg), the areas under the ROC curves of SVV were 0.864, 0.759, 0.718, and 0.521, the area under the ROC of PPV were 0.873, 0.792,0.705, and 0.505, and the area under the ROC of PVI were 0.851, 0.765 ,0.709, and 0.512. Under PEEP=0 mmHg, the diagnostic thresholds of SVV, PPV, and PVI were 10.5, 11.5, and 13.5. Under PEEP=5 mmHg, the diagnostic thresholds of SVV,PPV, and PVI were 11.5,13.5, and 14.5.Under PEEP=10 mmHg,the diagnostic thresholds of SVV, PPV, and PVI were 13.5,14.5, and 16.5.In the prone position,there was a significant correlation between SVV,PPV,PVI,and PEEP.
Conclusions:
SVV,PPV and PVI can predict fluid responsiveness similarly under the PEEP levels of 0,5, and 10 mmHg. Their diagnostic thresholds increases with the PEEP and the diagnostic accuracies decrease with the PEEP. However, under the PEEP level of 15 mmHg, SVV, PPV, and PVI can not predict fluid responsiveness accurately.

Related Concept Videos
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:17
Measurement of Blood Pressure
 01:14
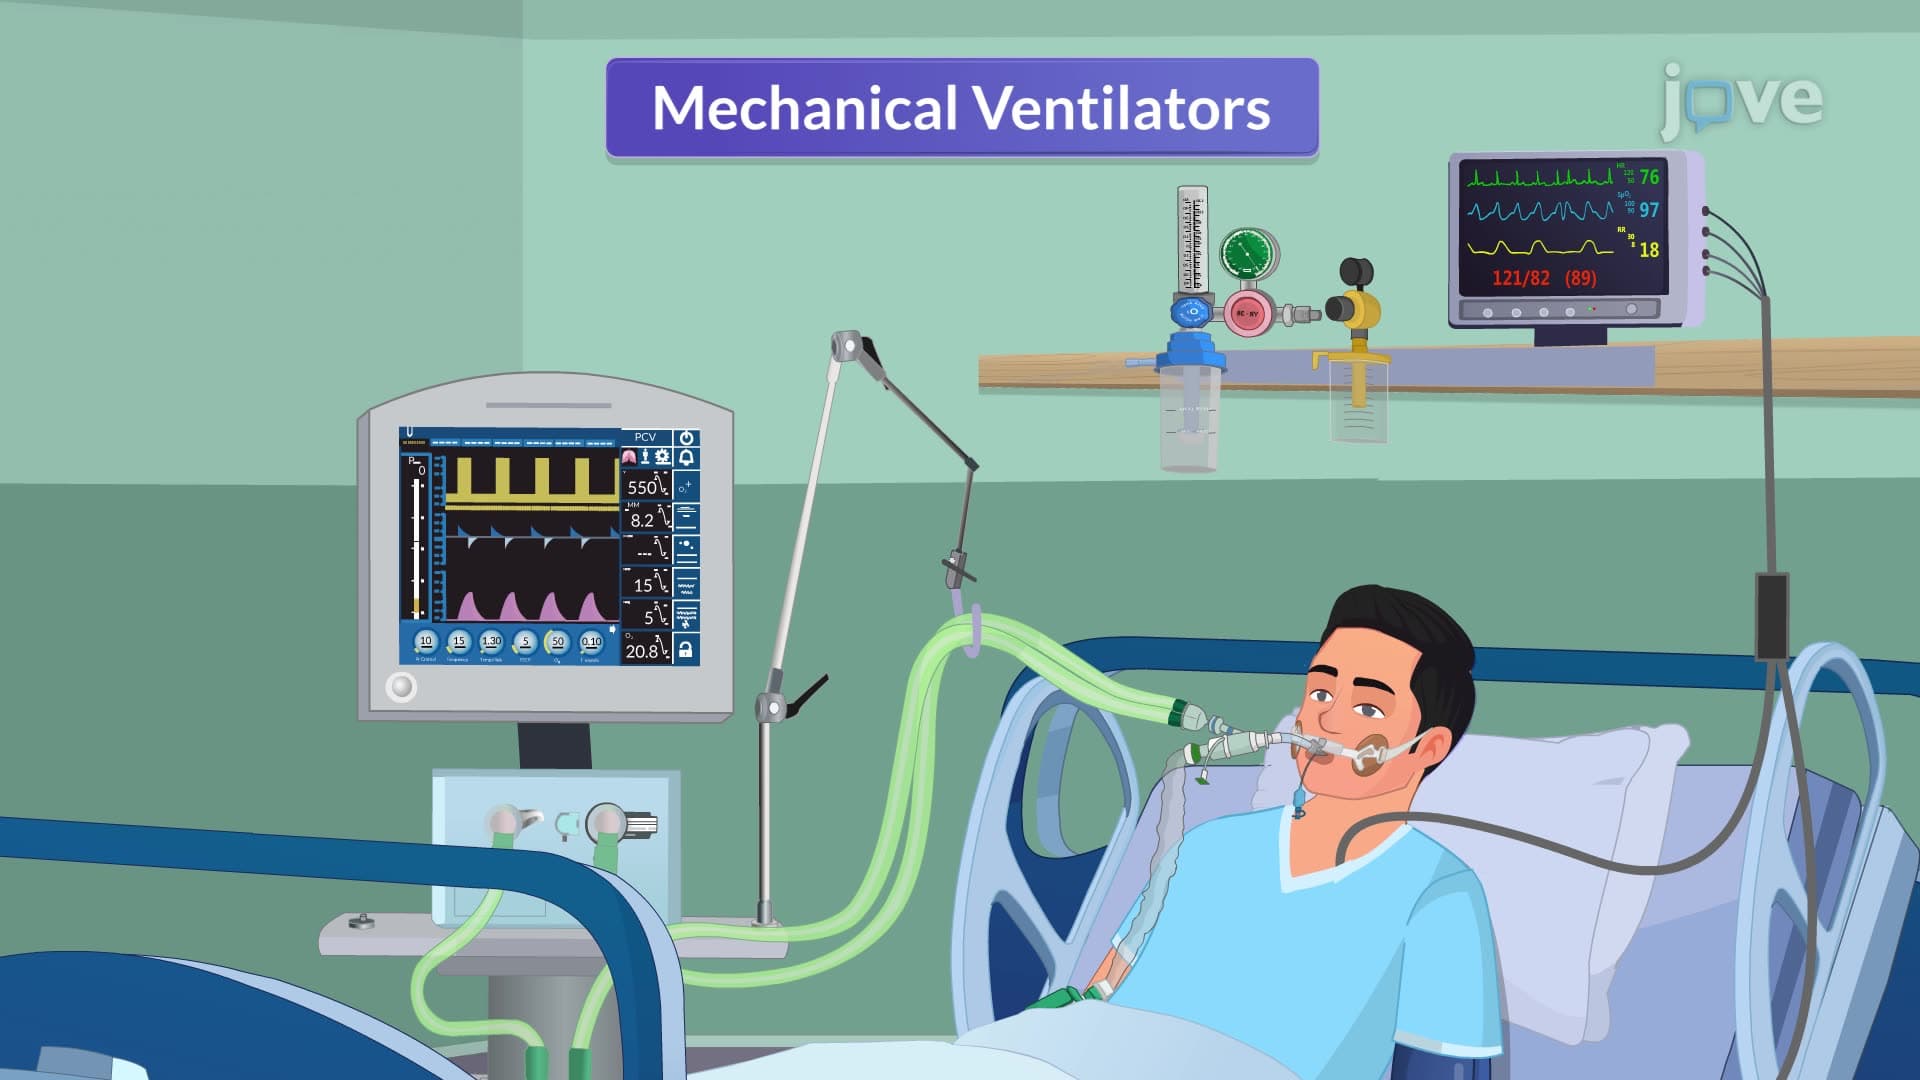
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:24
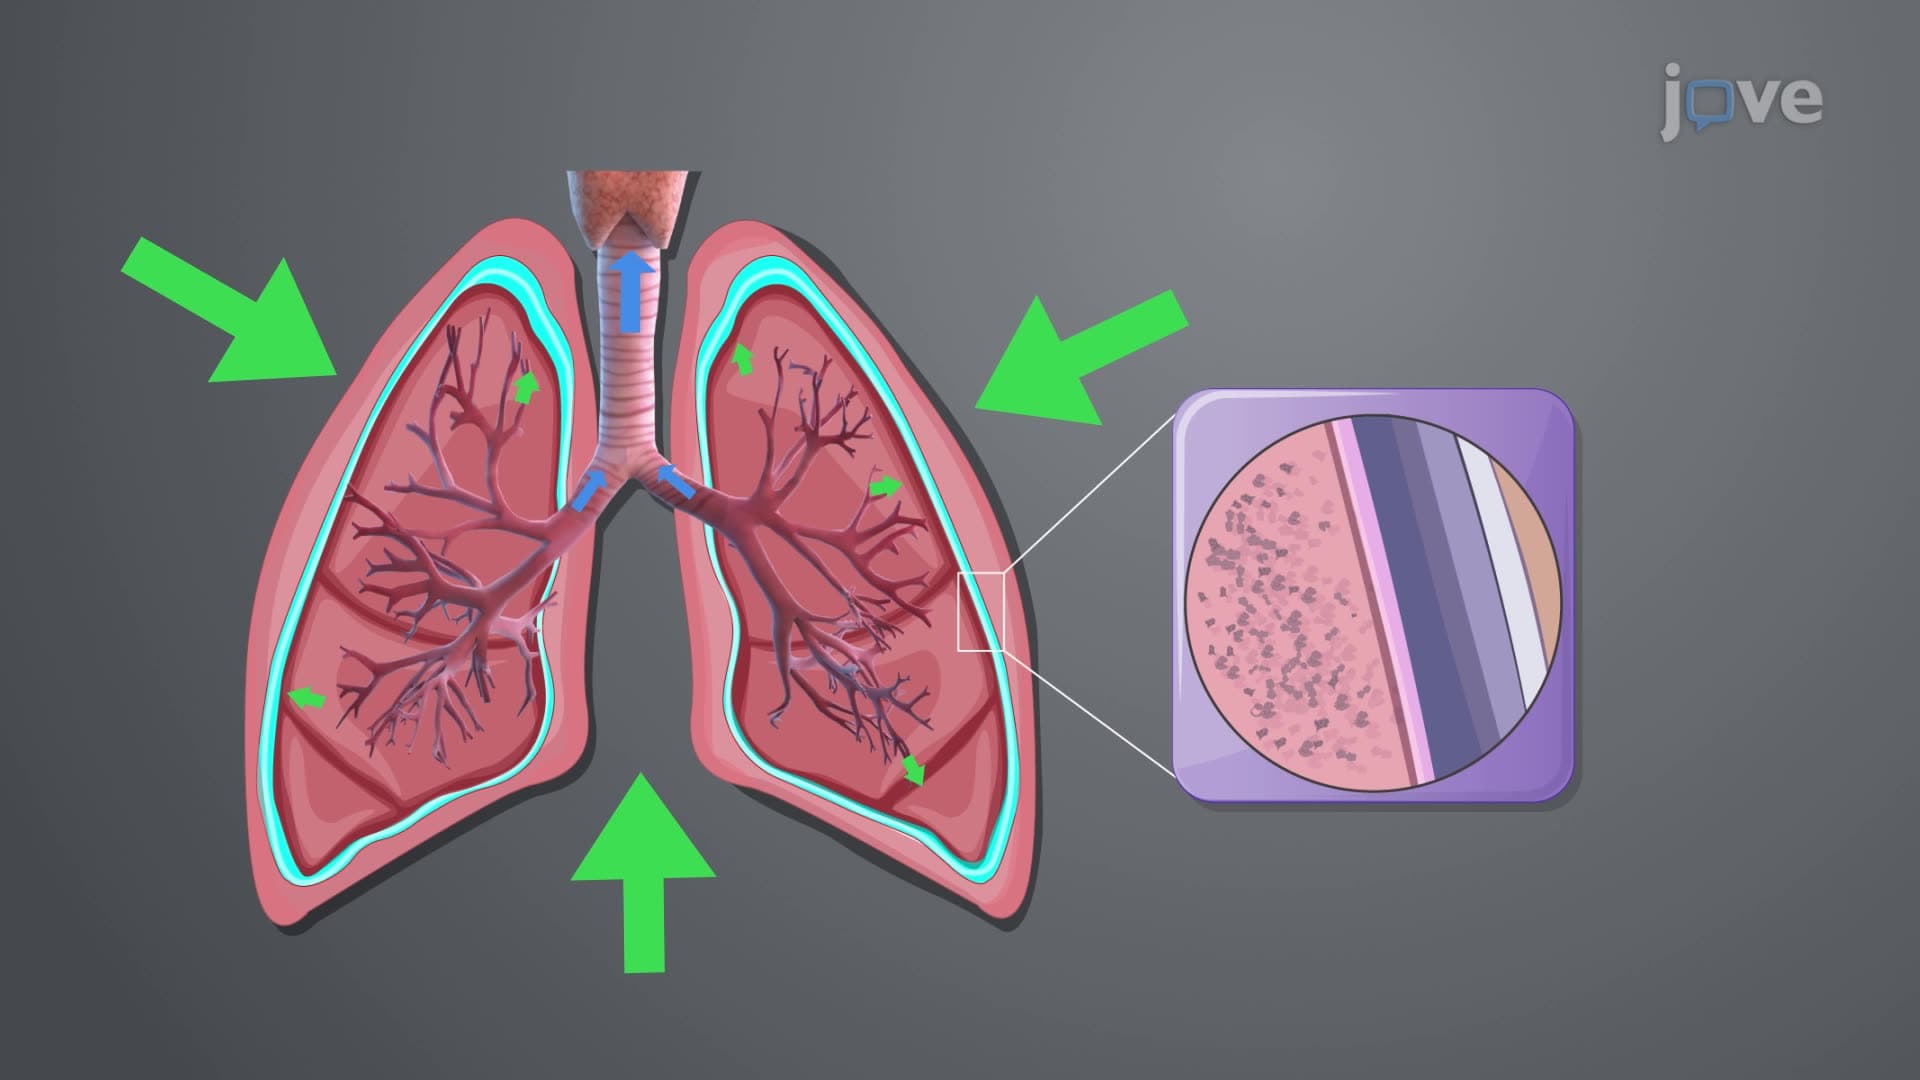
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...