Related Experiment Video
Updated: Apr 13, 2026
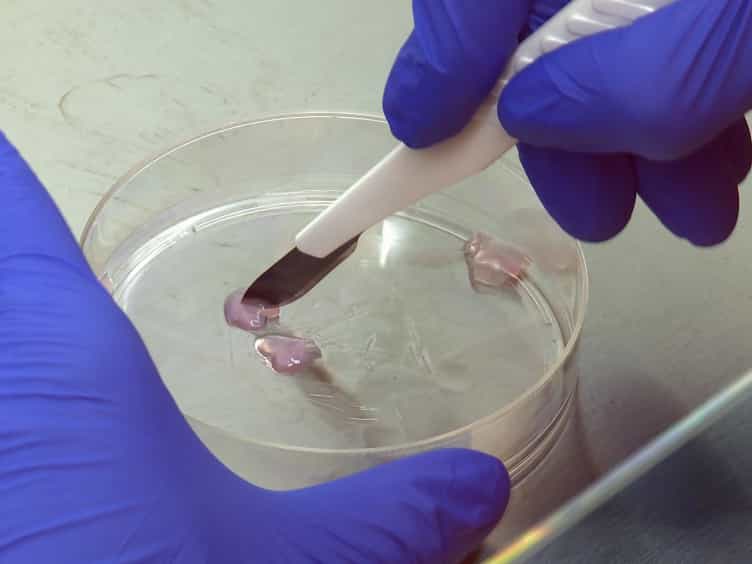

A 3D Human Lung Tissue Model for Functional Studies on Mycobacterium tuberculosis Infection
Published on: October 5, 2015
A systematic review of hepatic tuberculosis with considerations in human immunodeficiency virus co-infection
Andrew J Hickey1, Lilishia Gounder2,3, Mahomed-Yunus S Moosa4
1University of Maryland School of Medicine, 655 W. Baltimore Street, Baltimore, MD, 21201, USA. andrew.hickey@som.umaryland.edu.

Background:
Mycobacterium tuberculosis (TB) infection of the liver, known as hepatic TB, is an extrapulmonary manifestation of TB. Hepatic TB has become more prevalent, likely as a result of the human immunodeficiency virus/acquired immunodeficiency syndrome (HIV/AIDS) epidemic. We sought to review case series to characterize the epidemiology, pathophysiology, clinical features, diagnosis, and treatment of hepatic TB and to comment on the impact of HIV co-infection on these characteristics.
Methods:
We conducted a systematic literature search in PubMed and ScienceDirect for articles pertaining to hepatic TB with human subjects from 1960 to July 2013.
Results:
We obtained data on 618 hepatic TB patients from 14 case series. The most common reported signs and symptoms were hepatomegaly (median: 80%, range: 10-100%), fever (median: 67%, range: 30-100), respiratory symptoms (median: 66%, range: 32-78%), abdominal pain (median: 59.5%, range: 40-83%), and weight loss (median: 57.5%, range: 20-100%). Common laboratory abnormalities were elevated alkaline phosphatase and gamma-glutamyl transferase. Ultrasound and computerized tomography (CT) were sensitive but non-specific. On liver biopsy, smear microscopy for acid-fast bacilli had a median sensitivity of 25% (range: 0-59%), histology of caseating granulomas had a median sensitivity of 68% (range: 14-100%), and polymerase chain reaction for TB had a median sensitivity of 86% (range: 30-100%). Standard anti-tuberculous chemotherapy for 6 to 12 months achieved positive outcomes for nearly all patients with drug-susceptible TB.
Conclusions:
Clinicians in TB-endemic regions should maintain a high index of suspicion for hepatic TB in patients presenting with hepatomegaly, fever, respiratory symptoms, and elevated liver enzymes. The most sensitive imaging modality is a CT scan, while the most specific diagnostic modality is a liver biopsy with nucleic acid testing of liver tissue samples. Upon diagnosis, 4-drug anti-TB therapy should promptly be initiated. HIV co-infected patients may have more complex cases and should be closely monitored for complications.


Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories: