Related Experiment Video
Updated: Apr 12, 2026
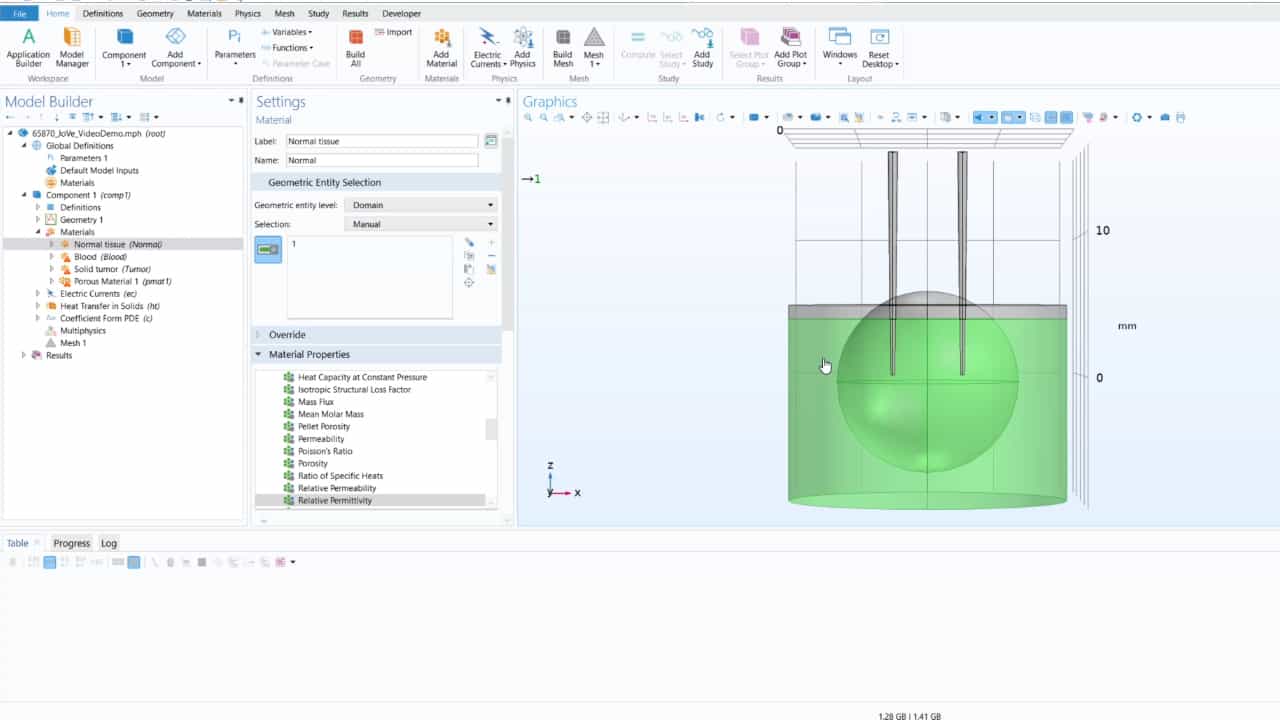

Author Spotlight: Computing the Effects of a Local Radiofrequency Hyperthermia Intervention on Tumor Biomechanics
Published on: December 1, 2023
Intra-abdominal pressure, Cardiac Index and vascular resistance during hyperthermic intraperitoneal chemotherapy: a
Christoph N Schluermann1, Jens Hoeppner, Christoph Benk
1Department of Anaesthesiology and Critical Care Medicine, Freiburg University Medical Center, Freiburg, Germany - Johannes.Kalbhenn@uniklinik-freiburg.de.

Background:
Increased intra-abdominal pressure and hemodynamic variations during hyperthermic intraperitoneal chemotherapy (HIPEC) are expected to be comparable to pneumoperitoneum with decreased Cardiac Index (CI) and increased Systemic Vascular Resistance Index (SVRI). We hypothesized that despite comparable increased intra-abdominal pressure, hemodynamic changes during HIPEC would substantially differ from those described in laparoscopic surgery.
Methods:
In this prospective observational clinical study, after obtaining written informed consent, we assessed intra-abdominal pressure and hemodynamic and respiratory changes during HIPEC in 10 consecutive patients. Intra-abdominal pressure as the primary endpoint was continuously measured with a catheter placed in the abdominal cavity. Secondary endpoints were hemodynamic changes measured by pulse contour analysis and respiratory alterations. Fluid management was based on stroke volume variation.
Results:
The mean intra-abdominal pressure was constantly elevated during HIPEC at a level of 14.2 mmHg (P=0.002 compared to baseline). The mean SVRI dropped from 1716 dyn*sec/cm³/m² to 1490 dyn*sec/cm⁵/m² at the end of HIPEC (P<0.05). Mean CI increased from 3.2 to 3.45 L/m² (P<0.001) and Horovitz index decreased from 548 to 380 (P=0.001). Median fluid intake was 7000 mL. No patient developed acute kidney injury.
Conclusions:
Increased intra-abdominal pressure during HIPEC was comparable to pneumoperitoneum. Hemodynamic changes however were opposed with a decrease in SVRI and a compensative increase in CI. Current guidelines for anesthetic management in patients undergoing HIPEC are mainly based on findings from laparoscopic surgery and should therefore be reconsidered critically.

