Related Experiment Video
Updated: Apr 12, 2026
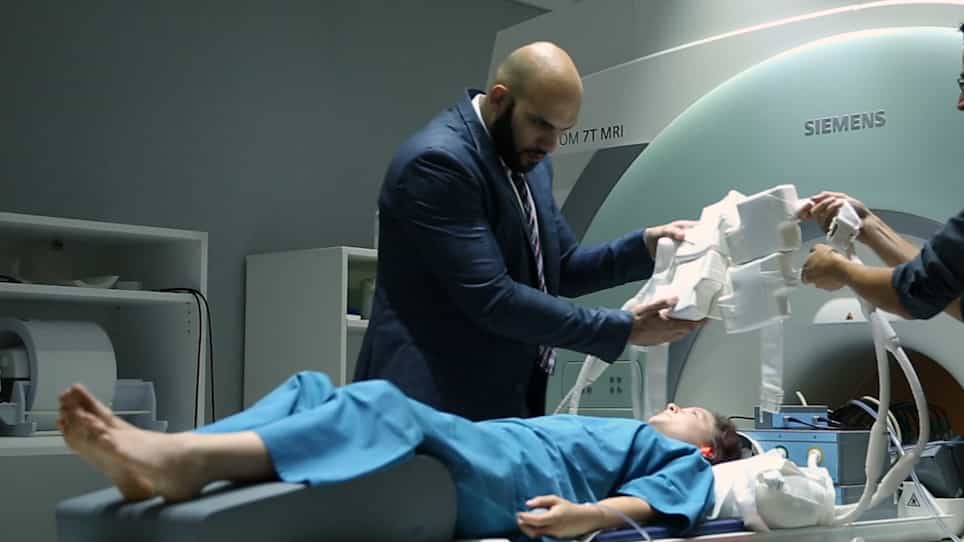

Cardiac Magnetic Resonance Imaging at 7 Tesla
Published on: January 6, 2019
Downstream clinical consequences of stress cardiovascular magnetic resonance based on appropriate use criteria
Sloane McGraw1, Omer Mirza1, Michael A Bauml1
1Section of Cardiology, Department of Medicine, University of Illinois at Chicago, 840 South Wood St. M/C 715, Suite 920 S, Chicago, IL, 60612, USA.

Background:
Appropriate use criteria (AUC) have been developed by professional organizations as a response to the rising costs of imaging, with the goal of optimizing test-patient selection. Consequently, the AUC are now increasingly used by third-party-payers to assess reimbursement. However, these criteria were created by expert consensus and have not been systematically assessed for CMR. The aim of this study was to determine the rates of abnormal stress-CMR and subsequent downstream utilization of angiography and revascularization procedures based on the most recent AUC.
Methods:
300 consecutive patients referred for CMR-stress testing were prospectively enrolled. Two cardiologists reviewed all clinical information before the CMR-stress test and classified the test as "appropriate', "maybe appropriate" or "rarely appropriate" according to the 2013 AUC. Patients were followed for 2 months for the primary outcomes of coronary angiography and/or revascularization.
Results:
49.7% of stress CMRs were appropriate, 36.7% maybe appropriate, and 13.6% rarely appropriate. Ischemia was significantly more likely to be seen in the appropriate (18.8%) or maybe appropriate groups (21.8%) than the rarely appropriate group (4.8%) (p = 0.030 and p = 0.014 respectively). Referral for cardiac catheterization was not significantly different in the appropriate (10.1%) and maybe appropriate groups (10.0%) compared to the rarely appropriate group (2.4%) (p = 0.119 and p = 0.127 respectively). No patients undergoing catheterization in the rarely appropriate group went on to require revascularization, in contrast to 53.3% of the appropriate vs 36.4% of the maybe appropriate patients (p = 0.391). Presence of ischemia led to referral for cardiac catheterization in 50.0% of the appropriate group vs 33.3% of the maybe appropriate group (p = 0.225); in contrast to none of the rarely appropriate group.
Conclusions:
The great majority of tests were classified as appropriate or maybe appropriate. Downstream cardiac catheterization rates were similar in all 3 groups. However, rarely appropriate studies never required revascularization, suggesting suboptimal resource utilization. Studies classified as maybe appropriate had similar rates of abnormal findings and led to similar rates of downstream catheterization and revascularization as those that were deemed appropriate. This suggests that consideration could be given to upgrading some of the common maybe appropriate indications to the appropriate category.
More Related Videos
 06:29
Cardiac Magnetic Resonance for the Evaluation of Suspected Cardiac Thrombus: Conventional and Emerging Techniques
Published on: June 11, 2019
 12:12
Echocardiographic Approaches and Protocols for Comprehensive Phenotypic Characterization of Valvular Heart Disease in Mice
Published on: February 14, 2017
Related Concept Videos
 01:21
Imaging Studies for Cardiovascular System IV: CMRI
 01:26
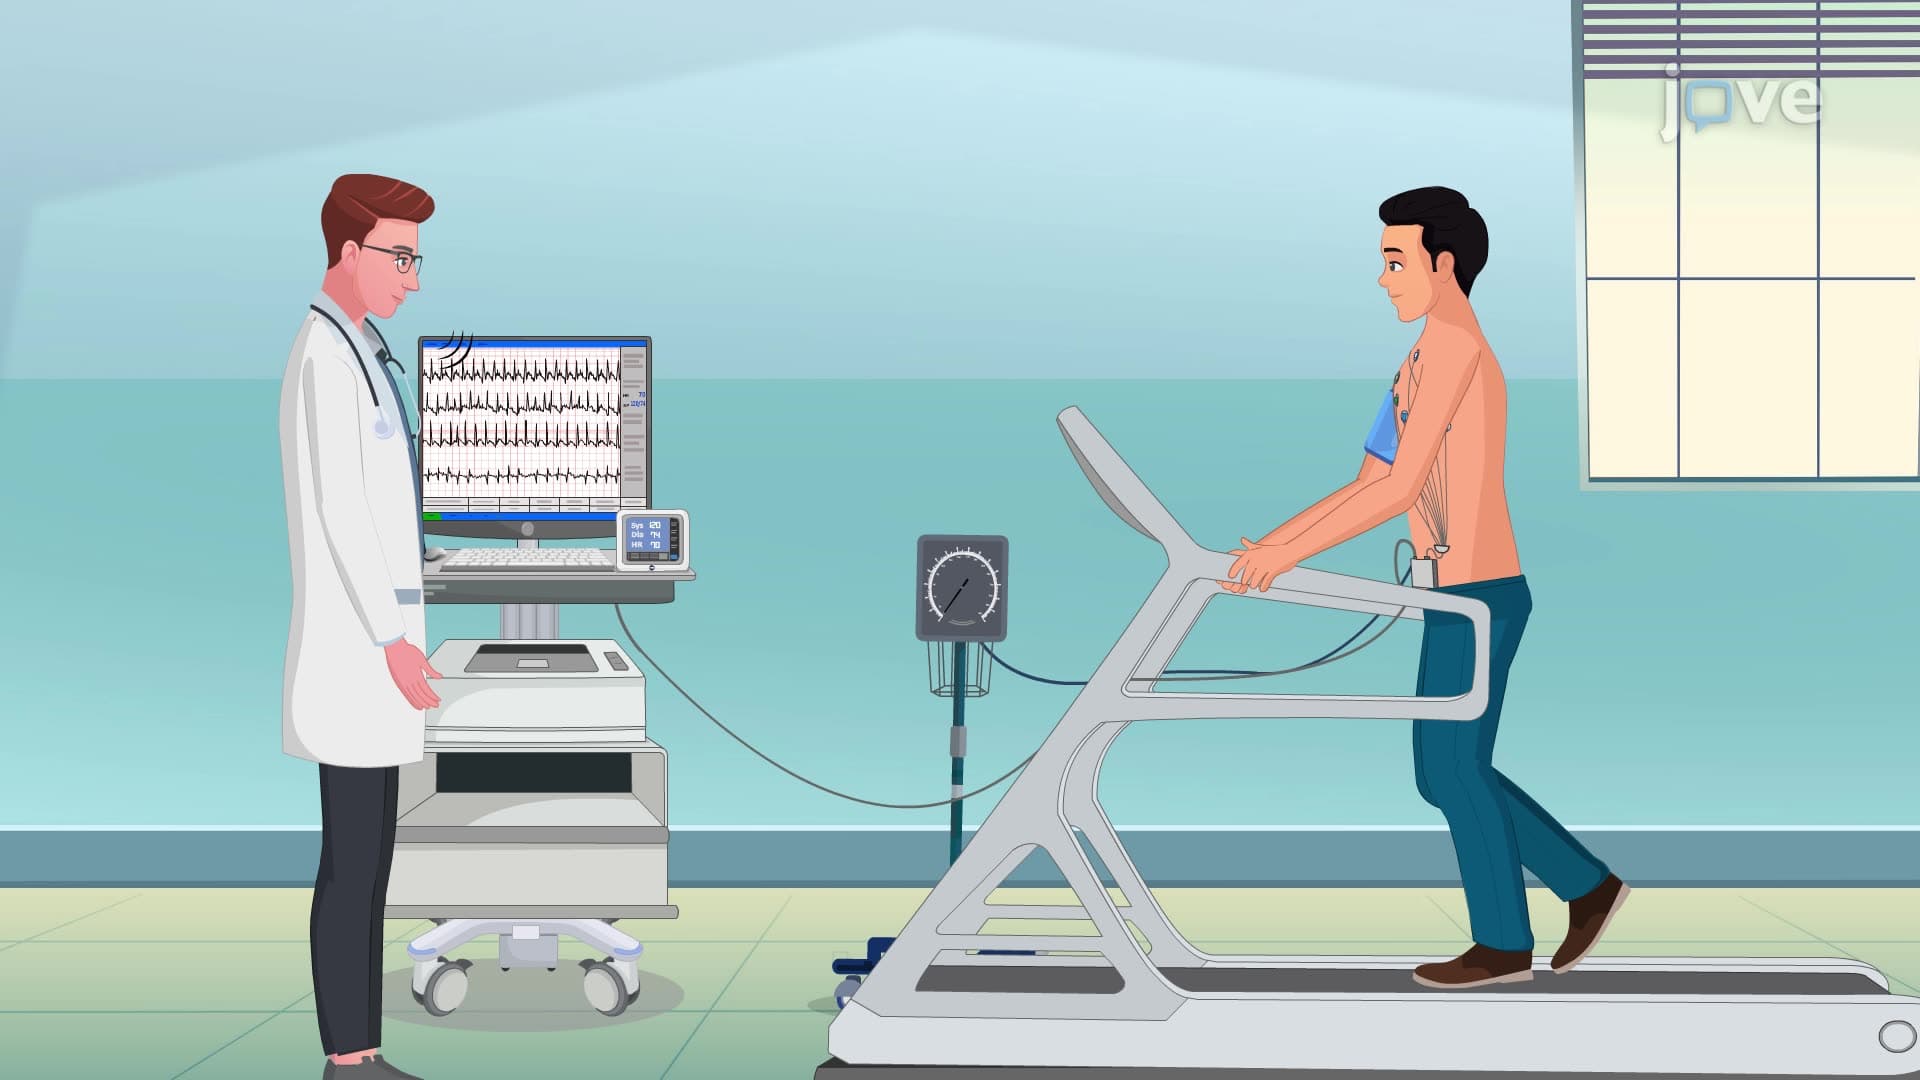
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations