Leaflet area as a determinant of tricuspid regurgitation severity in patients with pulmonary hypertension
Related Experiment Video
Updated: Apr 12, 2026
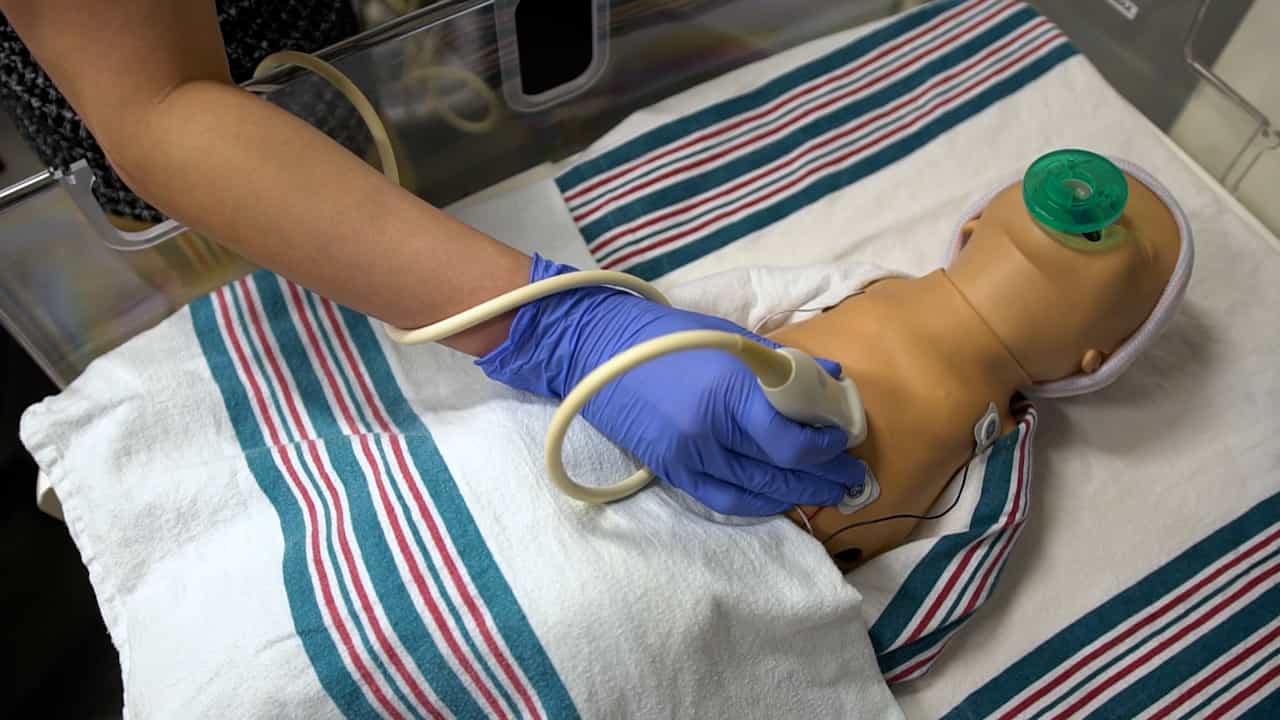
Hemodynamic Precision in the Neonatal Intensive Care Unit using Targeted Neonatal Echocardiography
Published on: January 27, 2023
Jonathan Afilalo1, Julia Grapsa2, Petros Nihoyannopoulos2
1From the Division of Cardiology, Jewish General Hospital, McGill University, Montreal, Canada (J.A., D.L., L.G.R.); Cardiac Ultrasound Laboratory, Division of Cardiology (J.G., P.N.) and National Pulmonary Hypertension Service, Division of Cardiology (J.S.R.G.), Hammersmith Hospital, Imperial College Healthcare NHS Trust, London, United Kingdom; Pulmonary Hypertension and Thromboendarterectomy Program, Division of Pulmonary and Critical Care Medicine (R.N.C.) and Cardiac Ultrasound Laboratory, Division of Cardiology (J.A., J.B., L.H., M.D.H., M.H.P., R.A.L.), Massachusetts General Hospital, Harvard University, Boston. jonathan.afilalo@mcgill.ca.

Background:
Tricuspid regurgitation (TR) is a risk factor for mortality in pulmonary hypertension (PH). TR severity varies among patients with comparable degrees of PH and right ventricular remodeling. The contribution of leaflet adaptation to the pathophysiology of TR has yet to be examined. We hypothesized that tricuspid leaflet area (TLA) is increased in PH, and that the adequacy of this increase relative to right ventricular remodeling determines TR severity.
Methods And Results:
A prospective cohort of 255 patients with PH from pre and postcapillary pathogeneses was assembled from 2 centers. Patients underwent a 3-dimensional echocardiogram focused on the tricuspid apparatus. TLA was measured with the Omni 4D software package. Compared with normal controls, patients with PH had a 2-fold increase in right ventricular volumes, 62% increase in annular area, and 49% increase in TLA. Those with severe TR demonstrated inadequate increase in TLA relative to the closure area, such that the ratio of TLA:closure area <1.78 was highly predictive of severe TR (odds ratio, 68.7; 95% confidence interval, 16.2-292.7). The median vena contracta width was 8.5 mm in the group with small TLA and large closure area as opposed to 4.8 mm in the group with large TLA and large closure area.
Conclusions:
TLA plays a significant role in determining which patients with PH develop severe functional TR. The ratio of TLA:closure area, reflecting the balance between leaflet adaptation versus annular dilation and tethering forces, is an indicator of TR severity that may identify which patients stand to benefit from leaflet augmentation during tricuspid valve repair.

Related Concept Videos
 01:20
Mitral Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:15
Aortic Regurgitation I: Introduction
 01:22
Mitral Stenosis I: Introduction
 01:28
Mitral Regurgitation IV: Nursing Management
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...