Related Experiment Video
Updated: Apr 12, 2026
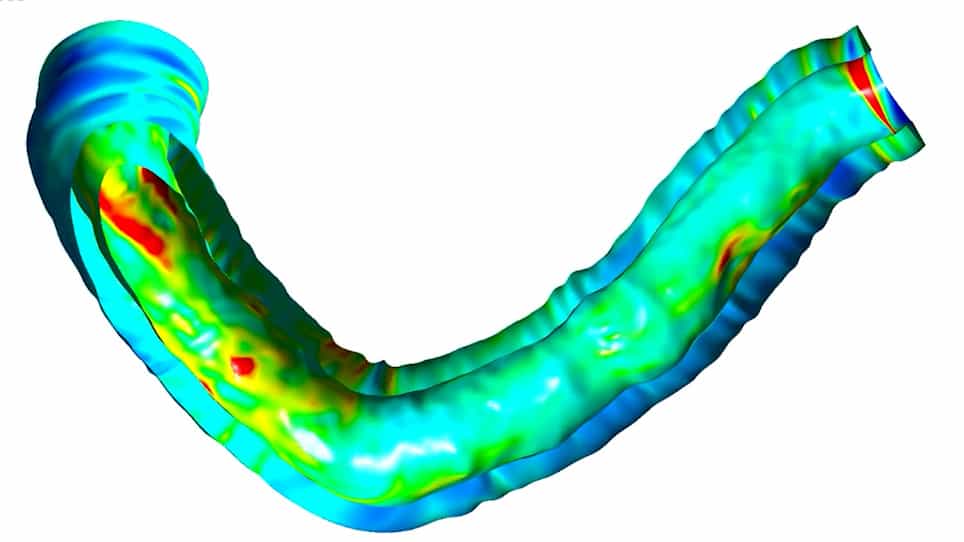
Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
The Functional Effects of Intramural Course of Coronary Arteries and its Relation to Coronary Atherosclerosis
Valtteri Uusitalo1, Antti Saraste2, Mikko Pietilä3
1Turku PET Centre, Turku University Hospital, University of Turku, Turku, Finland.

Insights
Myocardial bridging, a common finding on computed tomography angiography (CTA), does not reduce myocardial perfusion. Atherosclerosis is typically found proximal to myocardial bridges, but the overall burden is comparable.
Area of Science:
- Cardiology
- Radiology
- Medical Imaging
Background:
- Myocardial bridging involves an intramural course of coronary arteries, identified by computed tomography angiography (CTA) or systolic compression via invasive coronary angiography.
- Previous research suggests a link between myocardial bridging and proximal atherosclerotic plaques.
Purpose of the Study:
- To investigate the hemodynamic effects of myocardial bridging.
- To examine the relationship between myocardial bridging and coronary atherosclerosis.
Main Methods:
- Prospective study of 100 patients with intermediate likelihood of coronary artery disease.
- Identification of myocardial bridging segments using CTA.
- Assessment of myocardial perfusion with 15-Oxygen water positron emission tomography.
- Evaluation of systolic compression through invasive coronary angiography.
Main Results:
- Myocardial bridging was detected in 34% of patients, with deep bridging in 50% of these cases.
- No significant difference in myocardial stress perfusion was observed distal to myocardial bridging compared to remote regions.
- Atherosclerotic plaques were more frequent proximally to myocardial bridging, but overall atherosclerosis burden and vulnerable plaque presence were comparable between bridged and non-bridged arteries.
Conclusions:
- Myocardial bridging is frequently identified on CTA, though systolic compression is less common.
- Myocardial bridging is not associated with impaired myocardial perfusion during vasodilator stress.
- Atherosclerosis predominantly occurs proximal to myocardial bridges, with similar burden and plaque characteristics observed in bridged and non-bridged coronary arteries.
Objectives:
This study observed hemodynamic consequences of myocardial bridging and its relation to coronary atherosclerosis.
Background:
Myocardial bridging is seen as intramural course by computed tomography angiography (CTA) or systolic compression by invasive coronary angiography. Segments with myocardial bridging are in previous studies closely associated with proximal atherosclerotic plaques.
Methods:
We prospectively studied 100 patients 63 ± 7 years of age with intermediate likelihood of coronary artery disease. Segments with superficial (>1 mm) or deep (>2 mm) intramural course were identified using CTA. Myocardial perfusion was studied by 15-Oxygen water positron emission tomography and systolic compression by invasive coronary angiography.
Results:
Myocardial bridging was detected in 34 (34%) patients in 48 different vascular segments. Of these, 24 (50%) were deep and systolic compression was present in 14 (29%). In patients without obstructive coronary artery disease, myocardial stress perfusion distal to myocardial bridging was comparable with remote control regions (3.3 ± 0.9 ml/g/min vs. 3.3 ± 0.7 ml/g/min, n = 24, p = 0.88). Stress perfusion was comparable in segments with and without systolic compression (3.0 ± 0.9 vs. 2.7 ± 1.0 ml/g/min, p = 0.43). Atherosclerotic plaques were more frequent in proximal (71%) than myocardial bridging (7%) or distal (21%) segments. The presence of atherosclerosis and the average number of plaques were comparable in coronary arteries with and without myocardial bridging (73% vs. 60%, p = 0.14 and 2.0 ± 1.7 vs. 1.5 ± 1.6, p = 0.06). Median Agatston coronary calcium score was not elevated in vessels with myocardial bridge (15 [interquartile range: 0, 129] vs. 50 [interquartile range: 0, 241], p = 0.21).
Conclusions:
Myocardial bridging of coronary arteries is common on CTA, but only approximately one-third of these show systolic compression. Myocardial bridging is not associated with reduced myocardial perfusion during vasodilator stress. Atherosclerosis is located predominantly proximal to myocardial bridging but atherosclerotic burden and presence of vulnerable plaques were comparable.


Related Concept Videos
 01:26
Coronary Artery Disease II: Pathophysiology
 01:30
Coronary Artery Disease I: Introduction
 01:30
Atherosclerosis I: Introduction
 01:26
Coronary Artery Disease IV: Preventive Measures
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests