Related Experiment Video
Updated: Apr 12, 2026


Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Management of distal humeral coronal shear fractures
Shahram S Yari1, Nathan L Bowers1, Miguel A Craig1
1Shahram S Yari, Nathan L Bowers, Miguel A Craig, Baylor College of Medicine, Medical School, One Baylor Plaza, Houston, TX 77030, United States.

Abstract:
Coronal shear fractures of the distal humerus are rare, complex fractures that can be technically challenging to manage. They usually result from a low-energy fall and direct compression of the distal humerus by the radial head in a hyper-extended or semi-flexed elbow or from spontaneous reduction of a posterolateral subluxation or dislocation. Due to the small number of soft tissue attachments at this site, almost all of these fractures are displaced. The incidence of distal humeral coronal shear fractures is higher among women because of the higher rate of osteoporosis in women and the difference in carrying angle between men and women. Distal humeral coronal shear fractures may occur in isolation, may be part of a complex elbow injury, or may be associated with injuries proximal or distal to the elbow. An associated lateral collateral ligament injury is seen in up to 40% and an associated radial head fracture is seen in up to 30% of these fractures. Given the complex nature of distal humeral coronal shear fractures, there is preference for operative management. Operative fixation leads to stable anatomic reduction, restores articular congruity, and allows initiation of early range-of-motion movements in the majority of cases. Several surgical exposure and fixation techniques are available to reconstruct the articular surface following distal humeral coronal shear fractures. The lateral extensile approach and fixation with countersunk headless compression screws placed in an anterior-to-posterior fashion are commonly used. We have found a two-incision approach (direct anterior and lateral) that results in less soft tissue dissection and better outcomes than the lateral extensile approach in our experience. Stiffness, pain, articular incongruity, arthritis, and ulnohumeral instability may result if reduction is non-anatomic or if fixation fails.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 11:21
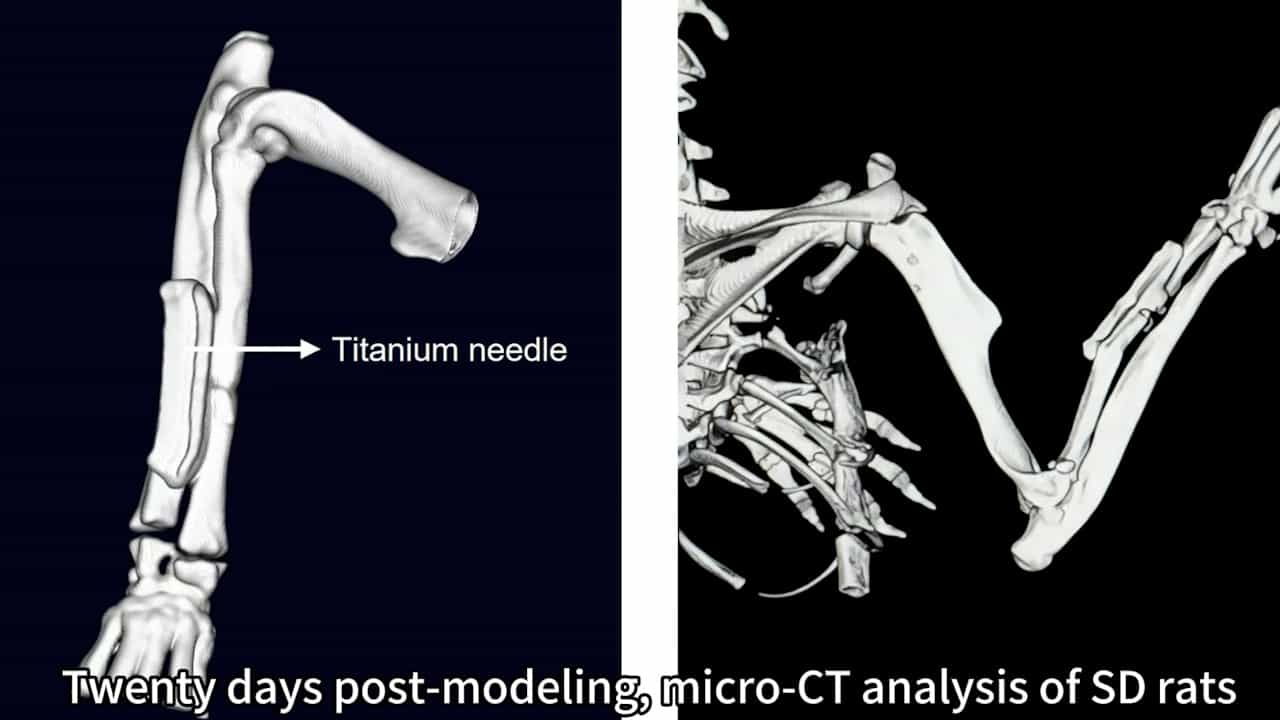
Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:19
Bones of the Upper Limb: Humerus