Related Experiment Video
Updated: Apr 12, 2026


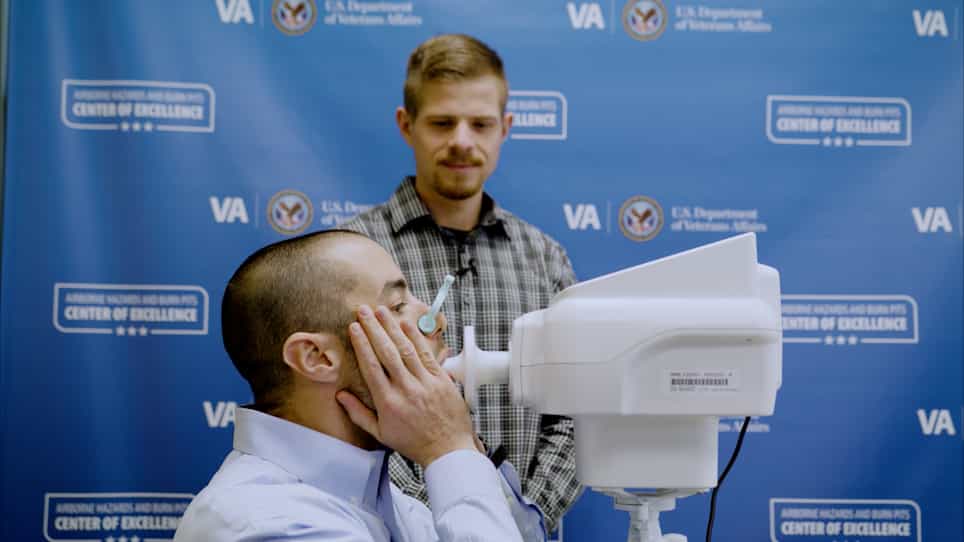
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Validity of bronchiolitis outcome measures
Ricardo M Fernandes1, Amy C Plint2, Caroline B Terwee3
1Department of Pediatrics, Santa Maria Hospital, Lisbon Academic Medical Centre, Lisbon, Portugal; Clinical Pharmacology Unit, Instituto de Medicina Molecular, University of Lisbon, Lisbon, Portugal; rmfernandes@campus.ul.pt.

Insights
The Respiratory Distress Assessment Instrument (RDAI) and Respiratory Assessment Change Score (RACS) show moderate responsiveness in bronchiolitis trials. However, the RDAI has limited construct validity and test-retest reliability, indicating potential measurement error.
Area of Science:
- Pediatric Respiratory Medicine
- Clinical Trial Methodology
- Measurement Properties of Clinical Instruments
Background:
- The Respiratory Distress Assessment Instrument (RDAI) and Respiratory Assessment Change Score (RACS) are commonly used in bronchiolitis clinical trials.
- Limited evidence exists regarding the measurement properties of RDAI and RACS.
Purpose of the Study:
- To investigate the validity, reliability, and responsiveness of the RDAI and RACS in infants with bronchiolitis.
- To assess the construct validity, test-retest agreement, interrater reliability, and responsiveness of these instruments.
Main Methods:
- Analysis of data from 1765 infants with bronchiolitis across two pediatric emergency department studies.
- Assessed construct validity through correlations with physiologic measures and hospitalization predictors.
- Evaluated responsiveness using change anchors and area under the curve; assessed reliability using limits of agreement and intraclass correlation coefficients.
Main Results:
- RDAI showed weak correlation with respiratory rate (r=0.38) but was associated with hospitalization (OR=1.36) and differed across admission statuses.
- Test-retest agreement for RDAI had limits of agreement of -3.80 to 3.64 (20% of range); interrater reliability was good (ICC=0.93).
- Both RDAI and RACS demonstrated moderate responsiveness (AUC: RDAI, 0.64-0.70; RACS, 0.72).
Conclusions:
- The RDAI exhibits poor to moderate construct validity and significant test-retest measurement error, despite good discriminative properties.
- RDAI and RACS are responsive to changes in respiratory distress in bronchiolitis but may not capture all severity determinants.
Background:
The Respiratory Distress Assessment Instrument (RDAI) and Respiratory Assessment Change Score (RACS) are frequently used in bronchiolitis clinical trials, but evidence is limited on their measurement properties. We investigated their validity, reliability, and responsiveness.
Methods:
We included data from up to 1765 infants with bronchiolitis enrolled in 2 studies conducted in pediatric emergency departments. We assessed RDAI construct validity by testing hypotheses of associations with physiologic measures (respiratory rate, oxygen saturation) and with constructs related to hospitalization, using correlation coefficients, and multivariable analysis. RDAI/RACS responsiveness was evaluated by using anchors of change based on these constructs; measures of responsiveness included the area under the curve. RDAI test-retest agreement and interrater reliability were evaluated by using limits of agreement and intraclass correlation coefficients.
Results:
Baseline RDAI scores were weakly correlated with respiratory rate (r = 0.38, P < .001), and scores increased in lower oxygen saturation categories (P < .001). Higher RDAI scores were associated with hospitalization (odds ratio: 1.36; 95% confidence interval: 1.26-1.47); scores differed between participants who were discharged, admitted, or stayed in the emergency department (P < .001). Our hypotheses were met, but the magnitude of associations was below our predefined thresholds. RDAI test-retest limits of agreement were -3.80 to 3.64 (20% of the range), whereas interrater reliability was good (intraclass correlation coefficient = 0.93). Formulated hypotheses for responsiveness were confirmed, with moderate responsiveness (area under the curve: RDAI, 0.64-0.70; RACS, 0.72).
Conclusions:
RDAI has poor to moderate construct validity, with good discriminative properties but considerable test-retest measurement error. The RDAI and RACS are responsive measures of respiratory distress in bronchiolitis but do not encompass all determinants of disease severity.

Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:30
Pneumonia III: Complications and Assessment
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...