Related Experiment Video
Updated: Jan 14, 2026
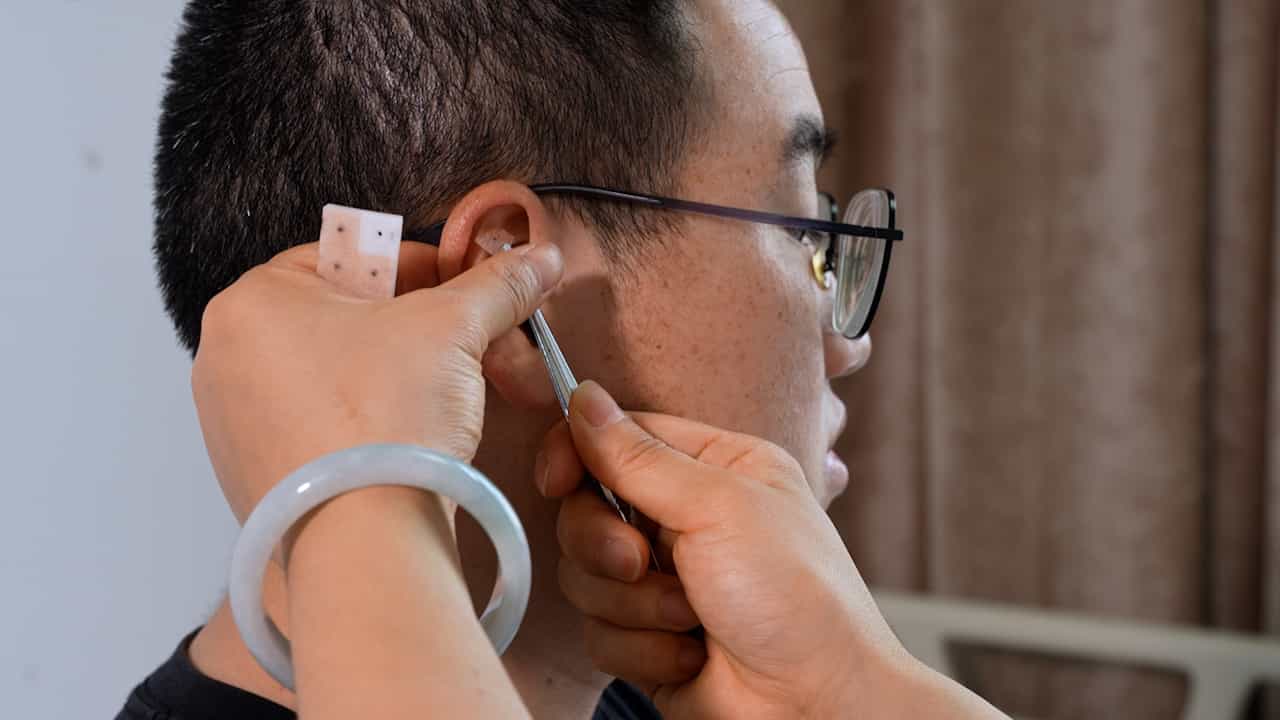
Author Spotlight: Efficacy of Auricular Pressure Bean Therapy in Reducing Wheezing Symptoms
Published on: May 10, 2024
Stopping long-acting beta2-agonists (LABA) for children with asthma well controlled on LABA and inhaled
Kayleigh M Kew1, Sean Beggs, Shaleen Ahmad
1Population Health Research Institute, St George's, University of London, Cranmer Terrace, London, UK, SW17 0RE.

Insights
No trials exist to guide stopping long-acting beta2-agonists (LABA) in children with asthma. Further research is needed to determine if inhaled corticosteroids (ICS) alone are sufficient once asthma is controlled.
Area of Science:
- Pediatric Pulmonology
- Clinical Therapeutics
- Evidence-Based Medicine
Background:
- Childhood asthma is a prevalent chronic condition, frequently leading to hospitalizations and emergency visits.
- Poorly controlled asthma necessitates increased medication, hospital stays, and emergency care.
- Long-acting beta2-agonists (LABA) are recommended as add-on therapy for children with asthma uncontrolled by inhaled corticosteroids (ICS), despite FDA 'black box' warnings advising short-term use.
Purpose of the Study:
- To compare the efficacy and safety of stepping down to inhaled corticosteroids (ICS)-only therapy versus continuing ICS plus long-acting beta2-agonists (LABA) in children with well-controlled asthma.
- To evaluate asthma control and adverse effects in pediatric asthma patients after adjusting maintenance therapy.
Main Methods:
- Searched multiple databases including Cochrane Airways Group, ClinicalTrials.gov, and WHO ICTRP, alongside reference lists and manufacturer registries up to April 2015.
- Included parallel randomized controlled trials (RCTs) of at least eight weeks duration in children (≤18 years) controlled on ICS and LABA, comparing ICS-only step-down to continued ICS plus LABA.
- Primary outcomes included exacerbations requiring oral steroids, asthma control levels, and serious adverse events; data extraction and analysis were performed by two independent reviewers.
Main Results:
- Extensive searches identified no randomized controlled trials meeting the inclusion criteria for this review.
- 1031 abstracts were screened, and 43 full-text articles assessed, with 'wrong comparison' and 'adult population' being primary reasons for exclusion.
- Adult studies were identified but did not report data separately for participants under 18 years.
Conclusions:
- There is a significant lack of randomized trial evidence to guide the discontinuation of long-acting beta2-agonists (LABA) in children whose asthma is controlled with combined inhaled corticosteroid (ICS) and LABA therapy.
- A well-designed, large, randomized, double-blind trial is warranted to investigate the safety and efficacy of stepping down LABA therapy in pediatric asthma patients.
- Such a trial should assess outcomes over at least six months and include children of various ages to provide crucial evidence for clinical practice.
Background:
Asthma is the most common chronic medical condition among children and is one of the most common causes of hospitalisation and medical visits. Poorly controlled asthma often leads to preventable exacerbations that require additional medications, hospital stays, or treatment in the emergency department.Long-acting beta2-agonists (LABA) are the preferred add-on treatment for children with asthma whose symptoms are not well controlled on inhaled corticosteroids (ICS). The US Food and Drug Administration has issued a 'black box' warning for LABA in asthma, and now recommends that they be used "for the shortest duration of time required to achieve control of asthma symptoms and discontinued, if possible, once asthma control is achieved".
Objectives:
To compare the effect on asthma control and adverse effects of stepping down to inhaled corticosteroids (ICS)-only therapy versus continuing ICS plus LABA in children whose asthma is well controlled on combined ICS and LABA therapy.
Search Methods:
We searched the Cochrane Airways Group Specialised Register, and also searched www.ClinicalTrials.gov, www.who.int/ictrp/en/, reference lists of primary studies and existing reviews, and manufacturers' trial registries (GlaxoSmithKline and AstraZeneca). We searched all databases from their inception to the present, and imposed no restriction on language of publication. The most recent search was done in April 2015.
Selection Criteria:
We looked for parallel randomised controlled trials of at least eight weeks' duration, available as published full text, abstract only, or unpublished data. We excluded studies including participants with other chronic respiratory comorbidities (for example bronchiectasis).We looked for studies in which children (18 years or younger) whose asthma was well controlled on any dose of ICS and LABA combination therapy were randomised to: a) step-down therapy to ICS alone or b) continued use of ICS and LABA.We included any dose of LABA (formoterol, salmeterol, vilanterol) and any dose of ICS (beclomethasone, budesonide, ciclesonide, mometasone, flunisolide, fluticasone propionate, fluticasone furoate, triamcinolone) delivered in a combination inhaler or in separate inhalers.
Data Collection And Analysis:
Two review authors independently screened all records identified in the searches. We used a data extraction tool in Microsoft Excel to manage searches and document reasons for inclusion and exclusion, and to extract descriptive and numerical data from trials meeting the inclusion criteria.The prespecified primary outcomes were exacerbations requiring oral steroids, asthma control, and all-cause serious adverse events.
Main Results:
Despite conducting extensive searches of electronic databases, trial registries and manufacturers' websites we identified no trials matching the inclusion criteria.After removing duplicates, we screened 1031 abstracts, and assessed 43 full-text articles for inclusion. We identified several adult studies, which will be summarised in a separate review (Ahmad 2014). The most common reasons for exclusion after viewing full texts were 'wrong comparison' (n = 22) and 'adult population' (n = 18).Some adult studies recruited adolescents from age 15, but none reported data separately for those under 18.
Authors' Conclusions:
There is currently no evidence from randomised trials to inform the discontinuation of LABAs in children once asthma control is achieved with ICS plus LABA. It is disappointing that such an important issue has not been studied, and a randomised double-blind trial recruiting children who are controlled on ICS plus LABA is warranted. The study should be large enough to assess children of different ages, and to measure the important safety and efficacy outcomes suggested in this review over at least six months.The only randomised evidence for stopping LABA has been conducted in adults; it will be summarised in a separate review.

