Related Experiment Video
Updated: Apr 12, 2026
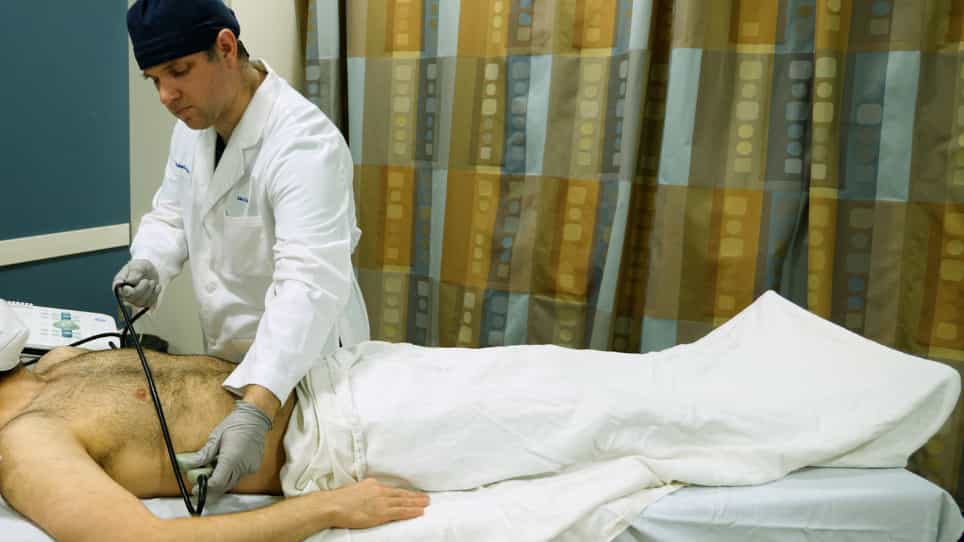

Focused Assessment with Sonography for Trauma FAST Exam: Image Acquisition
Published on: September 22, 2023
When is it safe to forgo abdominal CT in blunt-injured children?
Shannon N Acker1, Camille L Stewart1, Genie E Roosevelt2
1Department of Pediatric Surgery, Children's Hospital Colorado, University of Colorado School of Medicine, Aurora, CO.

Insights
Children with normal Glasgow Coma Scale (GCS) and shock index (SIPA) after blunt abdominal trauma may not need CT scans. This approach can reduce radiation exposure in pediatric patients with minor injuries.
Area of Science:
- Pediatric Traumatology
- Diagnostic Imaging
- Radiation Oncology
Background:
- Computed tomography (CT) is standard for diagnosing solid organ injury post-blunt trauma.
- Radiation exposure from CT scans carries a risk of secondary cancers in children.
Purpose of the Study:
- To identify patient-specific factors in children that predict the need for abdominal CT after blunt trauma.
- To reduce unnecessary radiation exposure in pediatric blunt abdominal trauma cases.
Main Methods:
- Retrospective review of pediatric patients (2009-2013) with blunt liver or spleen injury.
- Defined a low-risk group: Glasgow Coma Scale (GCS) of 15, normal pediatric age-adjusted shock index (SIPA), and injury from a single, nonmotorized blunt force.
- Compared outcomes between low-risk and at-risk groups.
Main Results:
- 101 of 206 children met low-risk criteria.
- No deaths, laparotomies, or rehabilitation discharges occurred in the low-risk group.
- Only 1 child in the low-risk group required a packed red cell transfusion.
Conclusions:
- Children with normal GCS and SIPA after nonmotorized blunt abdominal trauma are unlikely to have injuries requiring intervention.
- Clinical criteria can help select pediatric patients who can safely avoid abdominal CT, reducing radiation risks.
Introduction:
CT is the standard modality to diagnose solid organ injury after blunt trauma; however, the associated radiation carries a risk of cancer. We hypothesized that there are patient-specific factors that can identify those children who require abdominal CT.
Methods:
We reviewed all children admitted to 2 pediatric trauma centers after blunt trauma with liver or spleen injury from January 2009 to December 2013. The low-risk group was defined as a Glasgow Coma Scale (GCS) of 15 with normal pediatric age-adjusted shock index (heart rate/systolic blood pressure; SIPA) on presentation, and injury attributable to a single, nonmotorized, blunt force to the abdomen. The at-risk group did not meet these criteria.
Results:
We identified 206 children with blunt liver or spleen injury, 101 of whom met the low-risk criteria. Among these 101 children who met the low-risk criteria, there were no deaths, no children required laparotomy, only 1 child required a packed red cell transfusion, and no children required discharge to a rehabilitation facility.
Conclusion:
Children who present to the emergency department after blunt abdominal trauma by a nonmotorized force with a normal GCS and SIPA are unlikely to have a solid organ injury that will require intervention.
Related Concept Videos
 01:27
Imaging Studies III: Computed Tomography
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:10
Computed Tomography
The technique was invented in the 1970s and is based on the principle that as X-rays pass through the body, they are absorbed or reflected at different levels. In the technique, a patient lies on a motorized platform while a computerized axial tomography (CAT) scanner rotates...
 01:30
Radiological Investigation I: X-ray and CT
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...