Related Experiment Video
Updated: Apr 12, 2026


Cortical Bone Assessment Using Ultrasonic Guided Waves: A Reproducibility Study in a Healthy Population
Published on: January 31, 2025
Bone strength and muscle properties in postmenopausal women with and without a recent distal radius fracture
K Crockett1, C M Arnold2, J P Farthing3
1School of Physical Therapy, College of Medicine, University of Saskatchewan, Saskatoon, SK, Canada. katie.crockett@usask.ca.

Unlabelled:
Distal radius (wrist) fracture (DRF) in women over age 50 years is an early sign of bone fragility. Women with a recent DRF compared to women without DRF demonstrated lower bone strength, muscle density, and strength, but no difference in dual-energy x-ray absorptiometry (DXA) measures, suggesting DXA alone may not be a sufficient predictor for DRF risk.
Introduction:
The objective of this study was to investigate differences in bone and muscle properties between women with and without a recent DRF.
Methods:
One hundred sixty-six postmenopausal women (50-78 years) were recruited. Participants were excluded if they had taken bone-altering medications in the past 6 months or had medical conditions that severely affected daily living or the upper extremity. Seventy-seven age-matched women with a fracture in the past 6-24 months (Fx, n = 32) and without fracture (NFx, n = 45) were measured for bone and muscle properties using the nondominant (NFx) or non-fractured limb (Fx). Peripheral quantitative computed tomography (pQCT) was used to estimate bone strength in compression (BSIc) at the distal radius and tibia, bone strength in torsion (SSIp) at the shaft sites, muscle density, and area at the forearm and lower leg. Areal bone mineral density at the ultradistal forearm, spine, and femoral neck was measured by DXA. Grip strength and the 30-s chair stand test were used as estimates of upper and lower extremity muscle strength. Limb-specific between-group differences were compared using multivariate analysis of variance (MANOVA).
Results:
There was a significant group difference (p < 0.05) for the forearm and lower leg, with the Fx group demonstrating 16 and 19% lower BSIc, 3 and 6% lower muscle density, and 20 and 21% lower muscle strength at the upper and lower extremities, respectively. There were no differences between groups for DXA measures.
Conclusions:
Women with recent DRF had lower pQCT-derived estimated bone strength at the distal radius and tibia and lower muscle density and strength at both extremities.


Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:09
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:27
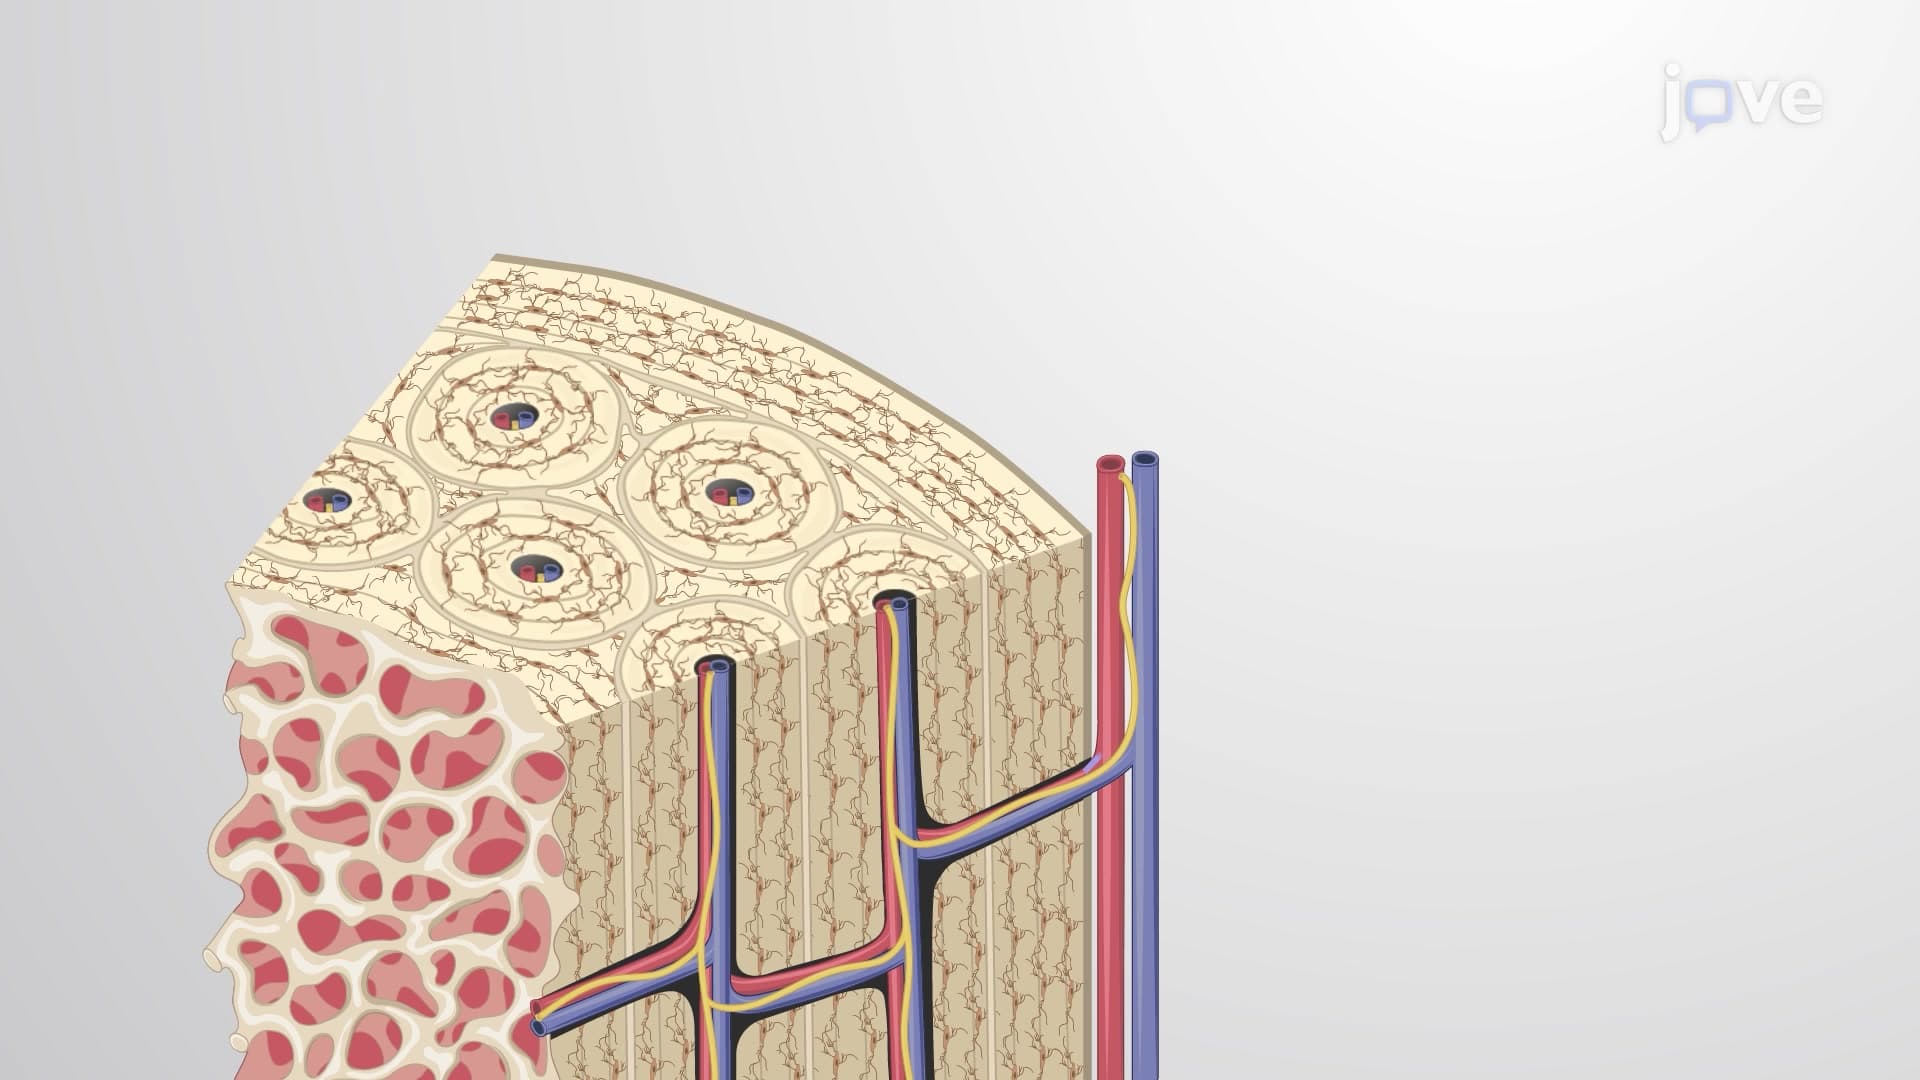
Compact Bone
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...
 01:40
Bone Remodeling