Fresh frozen plasma and spray-dried plasma mitigate pulmonary vascular permeability and inflammation in hemorrhagic shock
Related Experiment Video
Updated: Apr 12, 2026
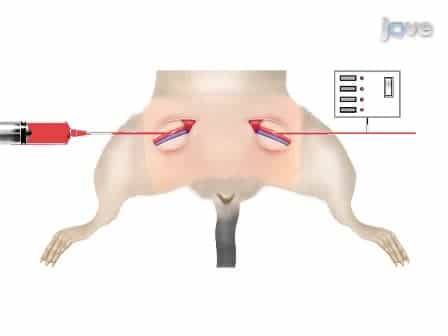
Fixed Volume or Fixed Pressure: A Murine Model of Hemorrhagic Shock
Published on: June 6, 2011
Daniel R Potter1, Gail Baimukanova, Sheila M Keating
1From the Blood Systems Research Institute (D.R.P., G.B., S.M.K., X.D., J.A.C., S.L.G., M.O.M., M.E.F., S.P.); and Department of Laboratory Medicine (M.O.M., S.P.), University of California San Francisco, San Francisco, California; Department of Surgery (Z.P.), University of Texas-Houston Medical School, Houston, Texas; Division of Critical Care Medicine (P.C.S.), Department of Pediatrics, Washington School of Medicine, St. Louis, Missouri; and Shock Trauma Center (R.K.), University of Maryland, Baltimore, Maryland.

Background:
In retrospective and prospective observational studies, fresh frozen plasma (FFP) has been associated with a survival benefit in massively transfused trauma patients. A dry plasma product, such as spray-dried plasma (SDP), offers logistical advantages over FFP. Recent studies on FFP have demonstrated that FFP modulates systemic vascular stability and inflammation. The effect of SDP on these measures has not been previously examined. This study compares SDP with FFP using in vitro assays of endothelial function and in vivo assays of lung injury using a mouse model of hemorrhagic shock (HS) and trauma.
Methods:
FFP, SDP, and lactated Ringer's (LR) solution were compared in vitro using assays of endothelial cell (EC) permeability, cytokine production and content, gene expression, as well as tight and adherens junction stability. All resuscitation products were also compared in a murine model of HS. Mean arterial pressures and physiologic measures were assessed. Pulmonary vascular permeability was measured using tagged dextran. Lung tissues were stained for CD68, VE-cadherin, and occludin.
Results:
Treatment of ECs with FFP and SDP, but not LR, preserved the integrity of EC monolayers in vitro and resulted in similar EC gene expression patterns and cytokine/growth factor production. FFP and SDP also reduced HS-induced pulmonary vascular permeability in vivo to the same extent. In mice with HS, mean arterial pressures and base excess were corrected by both FFP and SDP to levels observed in sham-treated mice. Treatment after HS with FFP and SDP but not LR solution reduce alveolar wall thickening, leukocyte infiltration, and the breakdown of EC junctions, as measured by staining for VE-cadherin, and occludin.
Conclusion:
Both FFP and SDP similarly modulate pulmonary vascular integrity, permeability, and inflammation in vitro and in vivo in a murine model of HS and trauma.
Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized,...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...