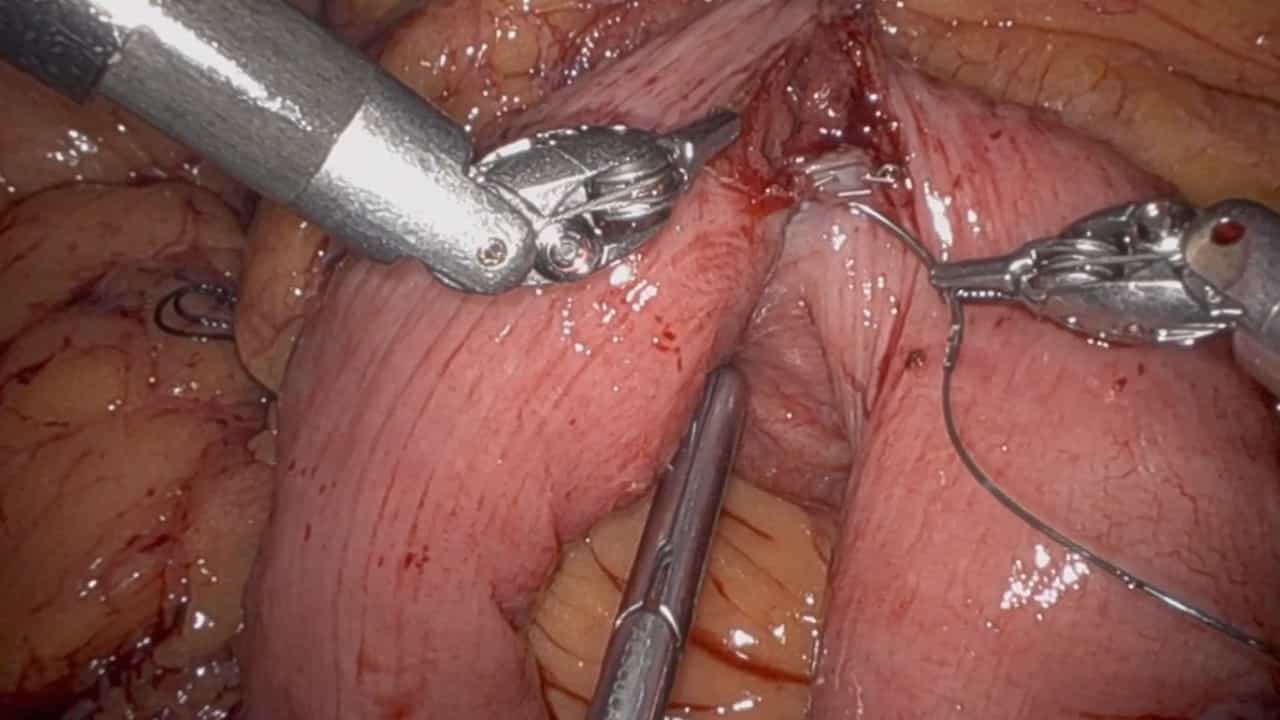
[A new β-shaped intracorporeal Billroth II anastomosis technique after totally laparoscopic distal gastrectomy]
Chaojun Zhang1, Weidong Xiao, Kang Chen
1Department of General Surgery, Xinqiao Hospital, Third Military Medical University, Chongqing 400037, China. huayang@tmmu.edu.cn.

Objective:
To investigate the feasibility and safety of the new β-shaped intracorporeal Billroth II( gastrojejunostomy using laparoscopic linear stapler after totally laparoscopic distal gastrectomy.
Methods:
Clinical data of 17 patients with distal gastric cancer who underwent β-shape intracorporeal Billroth II( reconstruction after totally laparoscopic distal gastrectomy in our department from January 2012 to September 2014 were analyzed retrospectively. Laparoscopic linear stapler was used in intracorporeal β-shaped Billroth II( side-to-side gastrojejunostomy for reconstruction.
Results:
All the 17 patients underwent β-shape intracorporeal Billroth II( reconstruction after totally laparoscopic distal gastrectomy successfully. There were no conversions and perioperative deaths. The average operative time was (207.3±11.3) min and the average anastomosis time was (41.2±2.5) min. The average number of harvested lymph node was 25.5±2.0 and estimated blood loss was (160.0±10.0) ml. The mean number of stapler was 6.5±0.2. The mean time to first flatus was (2.6±0.2) d and the mean hospital stay was (10.0±0.4) d. No anastomotic stenosis, leakage or other complications were found during 6 to 14 month follow-up.
Conclusions:
The β-shaped intracorporeal Billroth II( anastomosis technique after totally laparoscopic distal gastrectomy is safe and feasible. Anastomotic stenosis can be avoided using this new anastomosis method.

Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease