Related Experiment Video
Updated: Apr 11, 2026

Inverse Probability of Treatment Weighting Propensity Score using the Military Health System Data Repository and National Death Index
Published on: January 8, 2020
Comorbidity ascertainment from the ESRD Medical Evidence Report and Medicare claims around dialysis initiation: a
Mahesh Krishnan1, Eric D Weinhandl2, Scott Jackson2
1DaVita Clinical Research, DaVita HealthCare Partners Inc, Denver, CO.

Background:
The end-stage renal disease Medical Evidence Report serves as a source of comorbid condition data for risk adjustment of quality metrics. We sought to compare comorbid condition data in the Medical Evidence Report around dialysis therapy initiation with diagnosis codes in Medicare claims.
Study Design:
Observational cohort study using US Renal Data System data.
Setting & Participants:
Medicare-enrolled elderly (≥66 years) patients who initiated maintenance dialysis therapy July 1 to December 31, 2007, 2008, or 2009.
Index Tests:
12 comorbid conditions ascertained from claims during the 6 months before dialysis therapy initiation, the Medical Evidence Report, and claims during the 3 months after dialysis therapy initiation.
Reference Test:
None.
Results:
Comorbid condition prevalence according to claims before dialysis therapy initiation generally exceeded prevalence according to the Medical Evidence Report. The κ statistics for comorbid condition designations other than diabetes ranged from 0.06 to 0.43. Discordance of designations was associated with age, race, sex, and end-stage renal disease Network. During 23,930 patient-years of follow-up from 4 to 12 months after dialysis therapy initiation (8,930 deaths), designations from claims during the 3 months after initiation better discriminated risk of death than designations from the Medical Evidence Report (C statistics of 0.674 vs 0.616). Between the Medical Evidence Report and claims, standardized mortality ratios changed by >10% for more than half the dialysis facilities.
Limitations:
Neither the Medical Evidence Report nor diagnosis codes in claims constitute a gold standard of comorbid condition data; results may not apply to nonelderly patients or patients without Medicare coverage.
Conclusions:
Discordance of comorbid condition designations from the Medical Evidence Report and claims around dialysis therapy initiation was substantial and significantly associated with patient characteristics, including location. These patterns may engender bias in risk-adjusted quality metrics. In lieu of the Medical Evidence Report, claims during the 3 months after dialysis therapy initiation may constitute a useful source of comorbid condition data.


Related Concept Videos
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:25
Chronic Kidney Disease I: Introduction
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:30
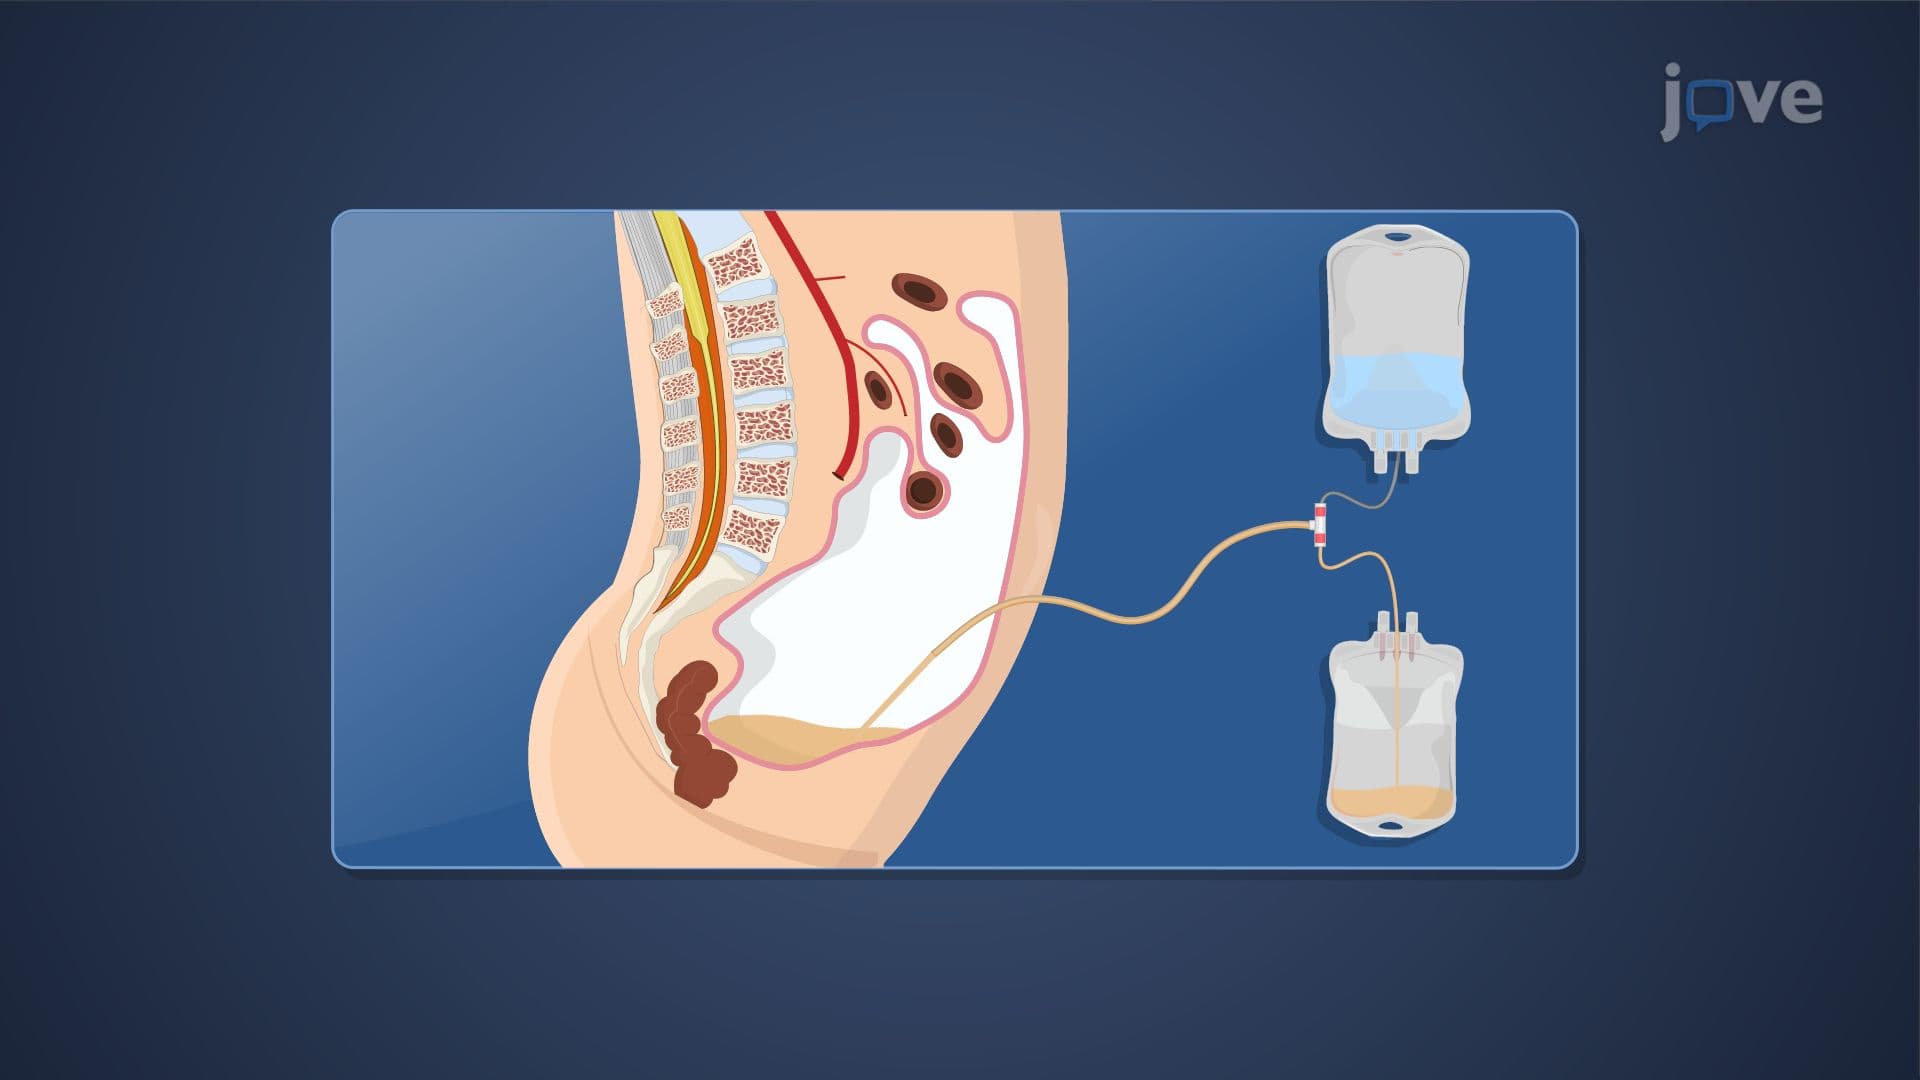
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis