Related Experiment Video
Updated: Mar 29, 2026


Personalized Peptide Arrays for Detection of HLA Alloantibodies in Organ Transplantation
Published on: September 6, 2017
Donor-specific HLA Antibodies Are Associated With Late Allograft Dysfunction After Pediatric Liver Transplantation
Laura J Wozniak1, Michelle J Hickey, Robert S Venick
11 Pediatric Gastroenterology, Hepatology, and Nutrition, David Geffen School of Medicine at University of California, Los Angeles, Los Angeles, CA. 2 Department of Pathology and Laboratory Medicine, David Geffen School of Medicine at University of California, Los Angeles, Los Angeles, CA. 3 Immunogenetics Center, University of California, Los Angeles, Los Angeles, CA. 4 Division of Liver and Pancreas Transplantation, David Geffen School of Medicine at University of California, Los Angeles, Los Angeles, CA.

Background:
The role of donor-specific HLA antibodies (DSA) after pediatric liver transplantation (LTx) is not clearly established. We completed a cross-sectional study to characterize DSA in long-term survivors of pediatric LTx and assess the impact of C1q-binding DSA on allograft outcomes.
Methods:
Serum samples were collected at routine clinic visits from 50 pediatric LTx recipients classified into 3 clinical phenotypes: nontolerant (n = 18) with de novo autoimmune hepatitis (DAIH) and/or late acute cellular rejection (ACR); stable (n = 25) on maintenance tacrolimus; operationally tolerant (n = 7). Samples were blinded, and antibody detection was performed using Luminex single antigen class I and II beads. Patients with positive DSA were tested for C1q-binding DSA.
Results:
DSA were detected in 54% (n = 27) of the patients, with the majority directed at HLA class II antigens (DR, 41%; DQ, 53%). Patients with DSA were younger at the time of LTx (P = 0.016) and time of study (P = 0.024). Mean aspartate aminotransferase, alanine aminotransferase, total bilirubin, and gamma glutamyl transferase were higher in DSA-positive patients, though did not reach statistical significance. Nontolerant patients were significantly more likely to have DQ DSA (61%) compared to stable (20%) and tolerant (29%) patients (P = 0.021). The nontolerant phenotype was associated with DSA and C1q-binding DSA, with odds ratios of 13 (P = 0.015) and 8.6 (P = 0.006), respectively. The presence of DQ DSA was associated with DAIH and late ACR, with odds ratios of 12.5 (P = 0.004) and 10.8 (P = 0.006), respectively.
Conclusions:
Allograft dysfunction is not always evident in patients with DSA, but DQ DSA are strongly associated with DAIH, late ACR, and chronic rejection.
More Related Videos

Related Concept Videos
 01:40
Cell-mediated Immune Responses
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:24
Tissue Transplantation
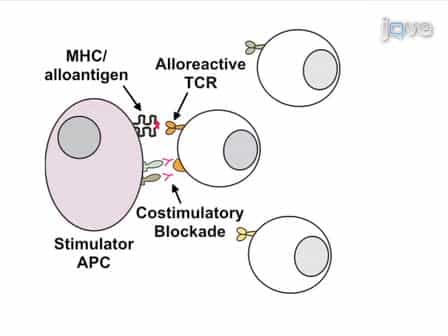
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...