Related Experiment Video
Updated: Apr 11, 2026

Author Spotlight: Traditional Chinese Medicine for Sleep Disorders in Acute COPD — A Safe, Cost-Effective Approach
Published on: October 18, 2024
The effect of increased lung volume in chronic obstructive pulmonary disease on upper airway obstruction during sleep
Paolo Biselli1, Peter R Grossman2, Jason P Kirkness2
1Johns Hopkins Sleep Disorders Center, Division of Pulmonary and Critical Care Medicine, Johns Hopkins Asthma and Allergy Center, Baltimore, Maryland; and Hospital Universitário, University of Sao Paulo, São Paulo, Brazil.

Abstract:
Patients with chronic obstructive pulmonary disease (COPD) exhibit increases in lung volume due to expiratory airflow limitation. Increases in lung volumes may affect upper airway patency and compensatory responses to inspiratory flow limitation (IFL) during sleep. We hypothesized that COPD patients have less collapsible airways inversely proportional to their lung volumes, and that the presence of expiratory airflow limitation limits duty cycle responses to defend ventilation in the presence of IFL. We enrolled 18 COPD patients and 18 controls, matched by age, body mass index, sex, and obstructive sleep apnea disease severity. Sleep studies, including quantitative assessment of airflow at various nasal pressure levels, were conducted to determine upper airway mechanical properties [passive critical closing pressure (Pcrit)] and for quantifying respiratory timing responses to experimentally induced IFL. COPD patients had lower passive Pcrit than their matched controls (COPD: -2.8 ± 0.9 cmH2O; controls: -0.5 ± 0.5 cmH2O, P = 0.03), and there was an inverse relationship of subject's functional residual capacity and passive Pcrit (-1.7 cmH2O/l increase in functional residual capacity, r(2) = 0.27, P = 0.002). In response to IFL, inspiratory duty cycle increased more (P = 0.03) in COPD patients (0.40 to 0.54) than in controls (0.41 to 0.51) and led to a marked reduction in expiratory time from 2.5 to 1.5 s (P < 0.01). COPD patients have a less collapsible airway and a greater, not reduced, compensatory timing response during upper airway obstruction. While these timing responses may reduce hypoventilation, it may also increase the risk for developing dynamic hyperinflation due to a marked reduction in expiratory time.
More Related Videos


Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:15
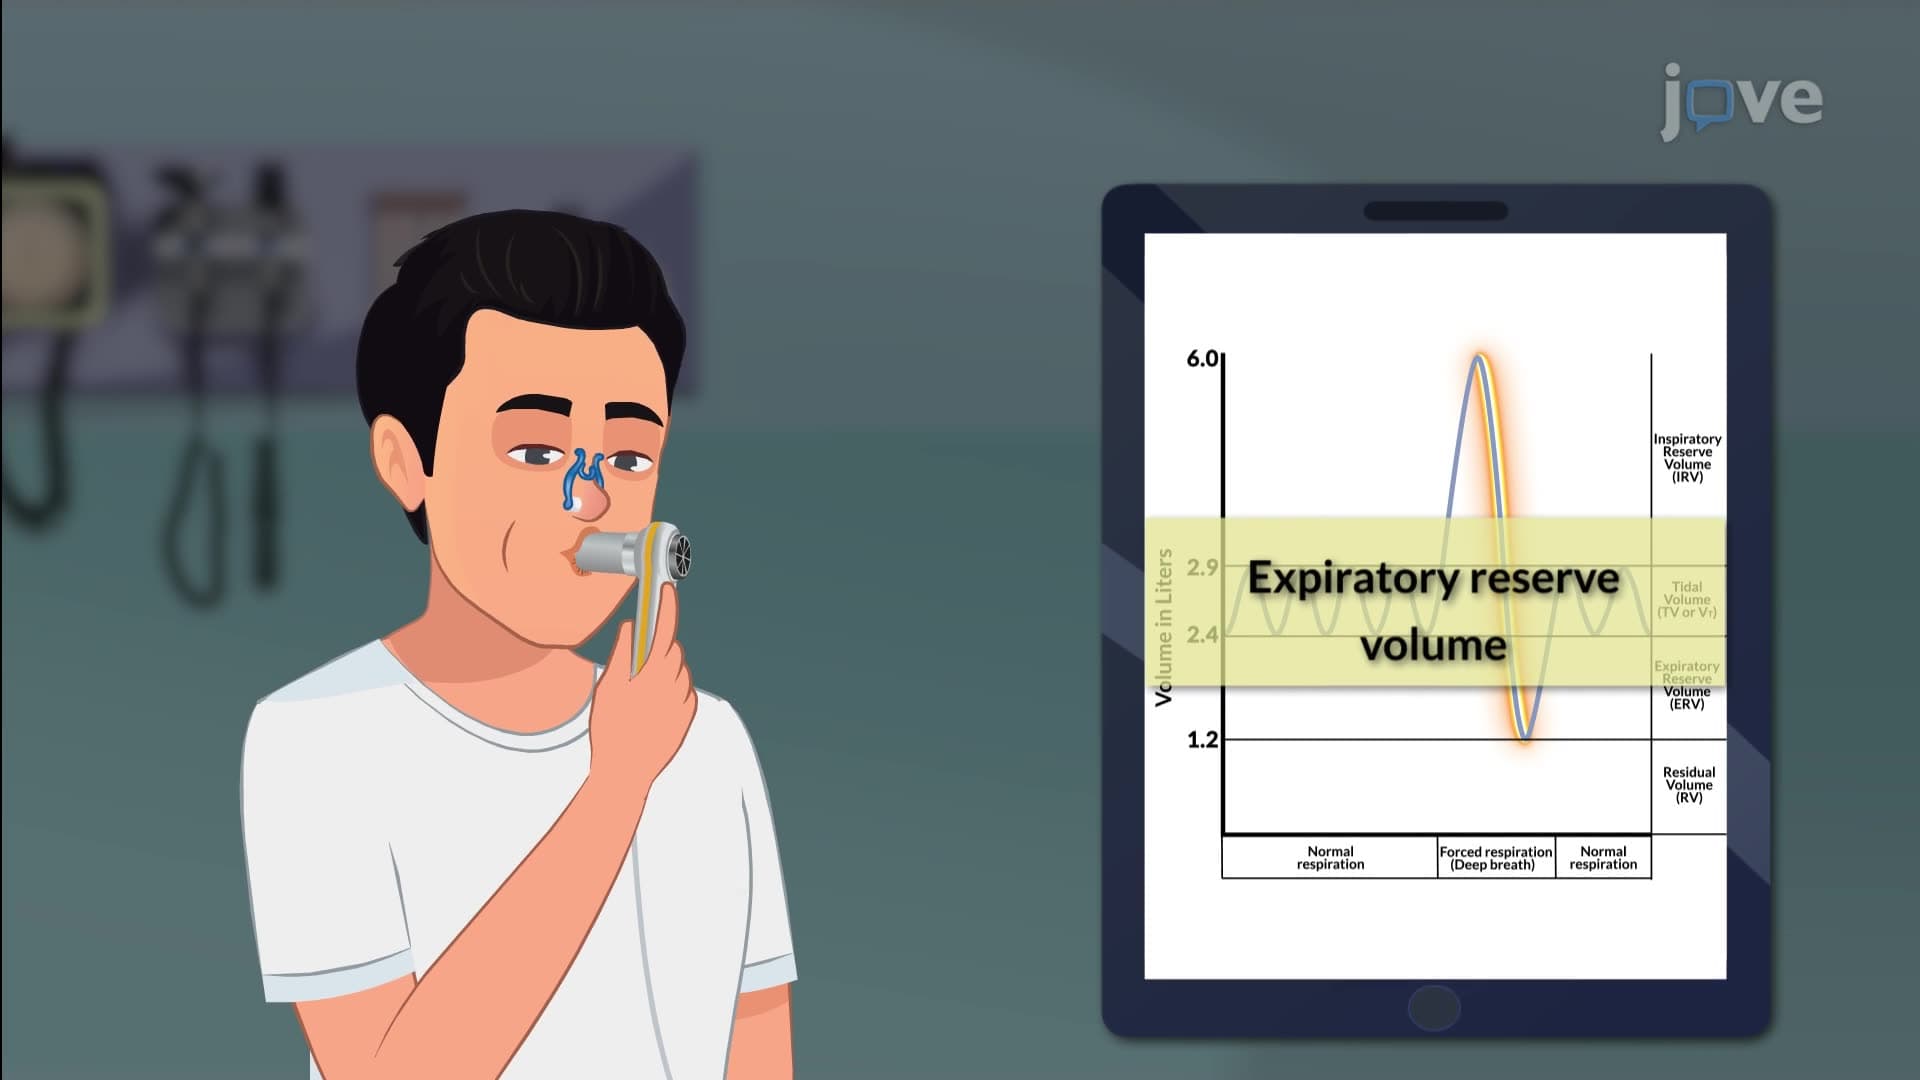
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:21
Sleep Apnea
The condition is more prevalent among...
 01:17
Other Pulmonary Disorders