Related Experiment Video
Updated: Apr 11, 2026
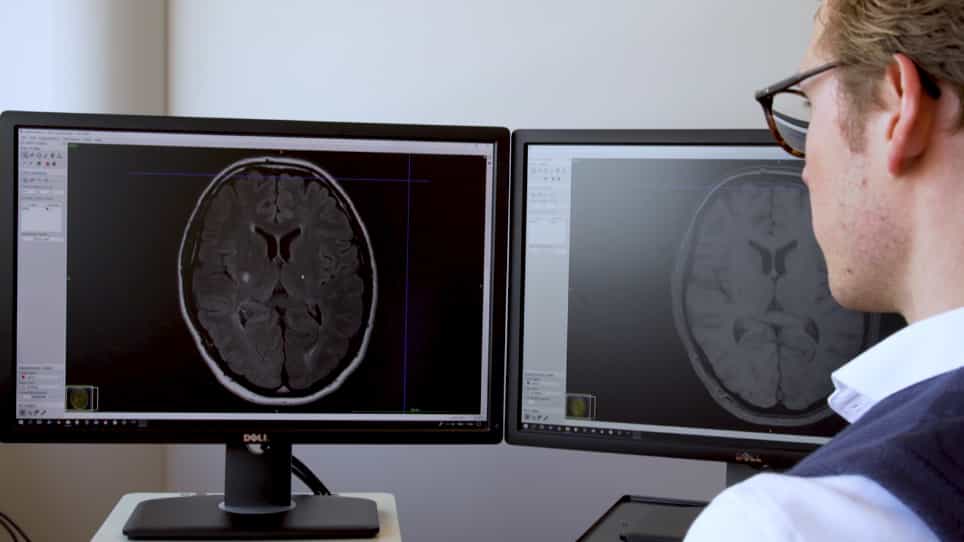

Brain Infarct Segmentation and Registration on MRI or CT for Lesion-symptom Mapping
Published on: September 25, 2019
Relationship Between Lesion Topology and Clinical Outcome in Anterior Circulation Large Vessel Occlusions
Srikant Rangaraju1, Christopher Streib1, Amin Aghaebrahim1
1From the Emory University, Atlanta, GA (S.R., M.F.); and University of Pittsburgh Medical Center, PA (C.S., A.A., A.J., T.G.J.).

Background And Purpose:
Diffusion-weighted imaging (DWI) Alberta Stroke Program Early CT Score (ASPECTS), a surrogate of infarct volume, predicts outcome in anterior large vessel occlusion strokes. We aim to determine whether topological information captured by DWI ASPECTS contributes additional prognostic value.
Methods:
Adults with intracranial internal carotid artery, M1 or M2 middle carotid artery occlusions who underwent endovascular therapy were included. The primary outcome measure was poor clinical outcome (3-month modified Rankin Scale score, 3-6). Prognostic value of the 10 DWI ASPECTS regions in predicting poor outcome was determined by multivariable logistic regression, controlling for final infarct volume, age, and laterality.
Results:
Two hundred and thirteen patients (mean age, 66.1±14.5 years; median National Institutes of Health Stroke Scale, 15) were included. Inter-rater reliability was good for DWI ASPECTS (deep regions, κ=0.72; cortical regions, κ=0.63). All DWI ASPECTS regions with the exception of the putamen were significant predictors (P<0.05) of poor outcome in univariate analyses. Statistical collinearity among ASPECTS regions was not observed. Using penalized multivariable logistic regression, only M4 (odds ratio, 2.82; 95% confidence interval, 1.39-5.76) and M6 (odds ratio, 2.45; 95% confidence interval, 1.15-5.3) involvement were associated with poor outcome. M6 involvement independently predicted poor outcome in right hemispheric strokes (odds ratio, 5.8; 95% confidence interval, 1.9-20.3), whereas M4 (odds ratio, 4.3; 95% confidence interval, 1.3-15.0) involvement predicted poor outcome in left hemispheric strokes adjusting for infarct volume. Topologic information modestly improved the predictive ability of a prognostic score that incorporates age, infarct volume, and hemorrhagic transformation.
Conclusions:
Involvement of the right parieto-occipital (M6) and left superior frontal (M4) regions affect clinical outcome in anterior large vessel occlusions over and above the effect of infarct volume and should be considered during prognostication.