Related Experiment Video
Updated: Apr 10, 2026


External Cephalic Version: Is it an Effective and Safe Procedure?
Published on: June 6, 2020
Cost-effectiveness of transvaginal ultrasound cervical length screening in singletons without a prior preterm birth:
Erika F Werner1, Maureen S Hamel1, Kelly Orzechowski2
1Department of Obstetrics and Gynecology, Warren Alpert Medical School of Brown University, Women & Infants Hospital, Providence, RI.

Objective:
We sought to reevaluate the cost-effectiveness of universal transvaginal ultrasound (TVU) cervical length (CL) screening in singleton pregnancies without prior spontaneous preterm birth.
Study Design:
We developed a decision model to assess costs and effects of universal TVU CL screening at 18-23 weeks' gestation compared to routine care for singleton pregnancies without prior preterm birth. Based on recent data, the model contains the following updates: (1) reduced incidence of CL ≤20 mm at initial screening ultrasound (0.83%), (2) vaginal progesterone supplementation for women with CL ≤20 mm, (3) additional ultrasound(s) for women with CL 21-24.9 mm, and (4) the assumption that vaginal progesterone reduces the rate of preterm birth <34 weeks' gestation by 39% if a short CL is diagnosed. The primary outcome was incremental cost-effectiveness ratio. We assumed a willingness to pay of $100,000 per quality-adjusted life year (QALY) gained. Additional outcomes included incidence of offspring with long-term neurological deficits and neonatal death. Sensitivity analyses were performed to assess the robustness of the results.
Results:
For every 100,000 women screened, universal TVU CL screening costs $9132 compared to routine care. Screening results in 215 QALYs gained and 10 fewer neonatal deaths or neonates with long-term neurologic deficits per 100,000 women screened. Based on the updated data, universal CL screening in low-risk women remains a cost-effective strategy (incremental cost-effectiveness ratio = $43/QALY), but is not cost saving as previously estimated. Sensitivity analyses reveal that when incidence of TVU CL ≤20 mm is <0.31%, universal TVU CL screening is no longer cost-effective. Additionally, when TVU CL costs >$314, progesterone reduces preterm delivery risk before 34 weeks <19%, or the incidence of a TVU CL 21-24.9 mm is >6.5%, CL screening is also no longer cost-effective.
Conclusion:
Despite the reduced incidence and efficacy used in this model, universal TVU CL continues to be cost-effective when compared to routine care in singletons without prior preterm birth.
More Related Videos
 09:51
Model Surgical Training: Skills Acquisition in Fetoscopic Laser Photocoagulation of Monochorionic Diamniotic Twin Placenta Using Realistic Simulators
Published on: March 21, 2018
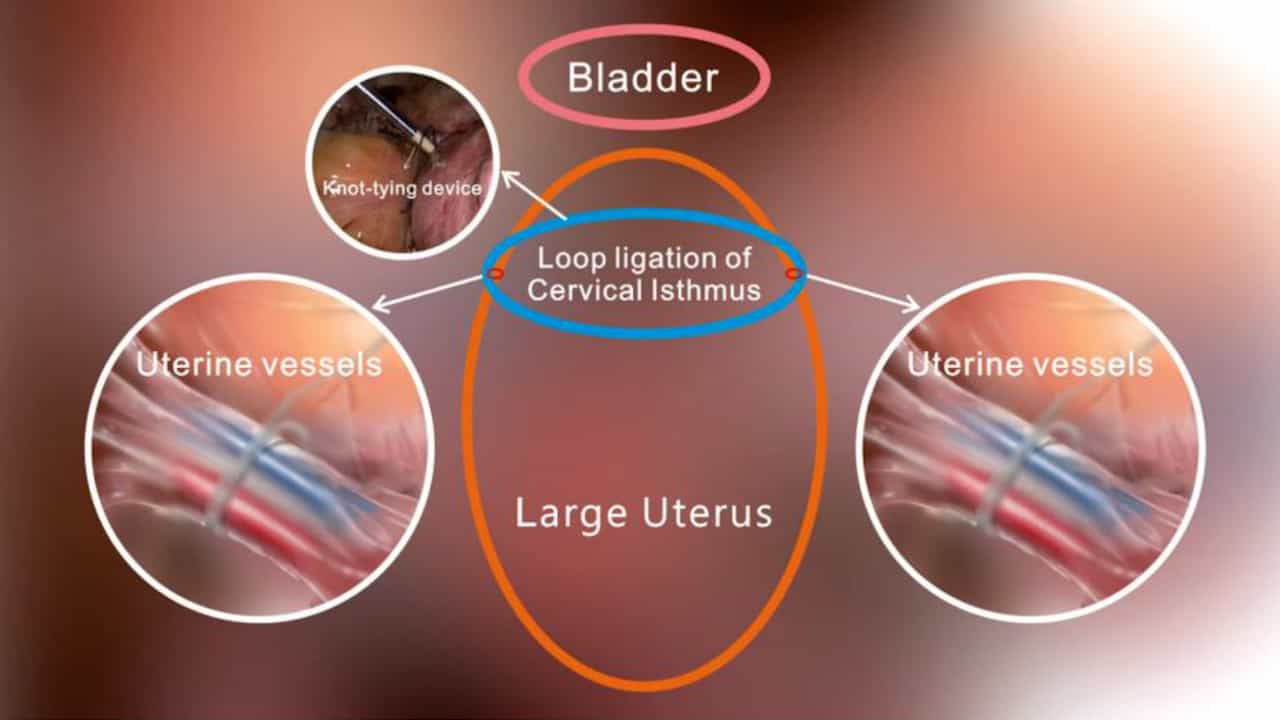 05:21
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025