Related Experiment Video
Updated: Apr 10, 2026

Targeted Next-generation Sequencing and Bioinformatics Pipeline to Evaluate Genetic Determinants of Constitutional Disease
Published on: April 4, 2018
Identification of SLC22A5 Gene Mutation in a Family with Carnitine Uptake Defect
Hatice Mutlu-Albayrak1, Judit Bene2, Mehmet Burhan Oflaz3
1Division of Pediatric Genetics, Department of Pediatrics, Meram Medical Faculty, University of Necmettin Erbakan, Meram, 42080 Konya, Turkey.

Insights
Primary systemic carnitine deficiency, caused by SLC22A5 gene mutations, can lead to hypertrophic cardiomyopathy and metabolic issues. A novel mutation was identified in a family with affected children and dysmorphic features.
Area of Science:
- Genetics
- Metabolic Disorders
- Cardiology
Background:
- Primary systemic carnitine deficiency results from mutations in the SLC22A5 gene, often presenting in early childhood with metabolic or cardiac symptoms.
- Carnitine uptake defect (CUD) affects cellular energy production, impacting organs with high energy demands like the heart and muscles.
Purpose of the Study:
- To identify the genetic cause of carnitine uptake defect in a family with hypertrophic cardiomyopathy and dysmorphic features.
- To characterize a novel mutation in the SLC22A5 gene and its association with clinical manifestations.
Main Methods:
- Tandem mass spectrometry (MS) was used to diagnose carnitine uptake defect.
- Exome sequencing of the SLC22A5 gene identified mutations.
- Array comparative genomic hybridization (array-CGH) was performed to investigate dysmorphic features.
Main Results:
- Tandem MS confirmed carnitine uptake defect in affected siblings.
- A novel homozygous mutation (c.1427T>G → p.Leu476Arg) in the SLC22A5 gene was identified in the affected siblings.
- Array-CGH revealed copy number variations but did not pinpoint the cause of dysmorphic features, suggesting the novel mutation may also contribute.
Conclusions:
- A novel SLC22A5 mutation is associated with primary systemic carnitine deficiency, hypertrophic cardiomyopathy, and potentially dysmorphic features.
- Early diagnosis and genetic identification are crucial for managing carnitine uptake defects.
- This case highlights the genetic heterogeneity and diverse clinical spectrum of SLC22A5-related disorders.
Abstract:
Primary systemic carnitine deficiency is caused by homozygous or compound heterozygous mutation in the SLC22A5 gene on chromosome 5q31. The most common presentations are in infancy and early childhood with either metabolic decompensation or cardiac and myopathic manifestations. We report a case of 9-year-old boy with dysmorphic appearance and hypertrophic cardiomyopathy. Tandem MS spectrometry analysis was compatible with carnitine uptake defect (CUD). His sister had died due to sudden infant death at 19 months. His second 4-year-old sister's echocardiographic examination revealed hypertrophic cardiomyopathy, also suffering from easy fatigability. Her tandem MS spectrometry analyses resulted in CUD. We sequenced all the exons of the SLC22A5 gene encoding the high affinity carnitine transporter OCTN2 in the DNA. And one new mutation (c.1427T>G → p.Leu476Arg) was found in the boy and his sister in homozygous form, leading to the synthesis of an altered protein which causes CUD. The parent's molecular diagnosis supported the carrier status. In order to explore the genetic background of the patient's dysmorphic appearance, an array-CGH analysis was performed that revealed nine copy number variations only. Here we report a novel SLC22A5 mutation with the novel hallmark of its association with dysmorphologic feature.
More Related Videos
 03:45
Investigating the Pathogenesis of MYH7 Mutation Gly823Glu in Familial Hypertrophic Cardiomyopathy using a Mouse Model
Published on: August 8, 2022
 06:53
Visualization of Mitochondrial Respiratory Function using Cytochrome C Oxidase / Succinate Dehydrogenase COX/SDH Double-labeling Histochemistry
Published on: November 23, 2011
Related Concept Videos
 01:27
Glucose Transporters
Facilitated diffusion-glucose transporters (GLUTs) are encoded by the solute-linked carrier (SLC) family 2, subfamily A gene family, or SLC2A. The 14 GLUT protein members are distributed into three classes:
 01:16
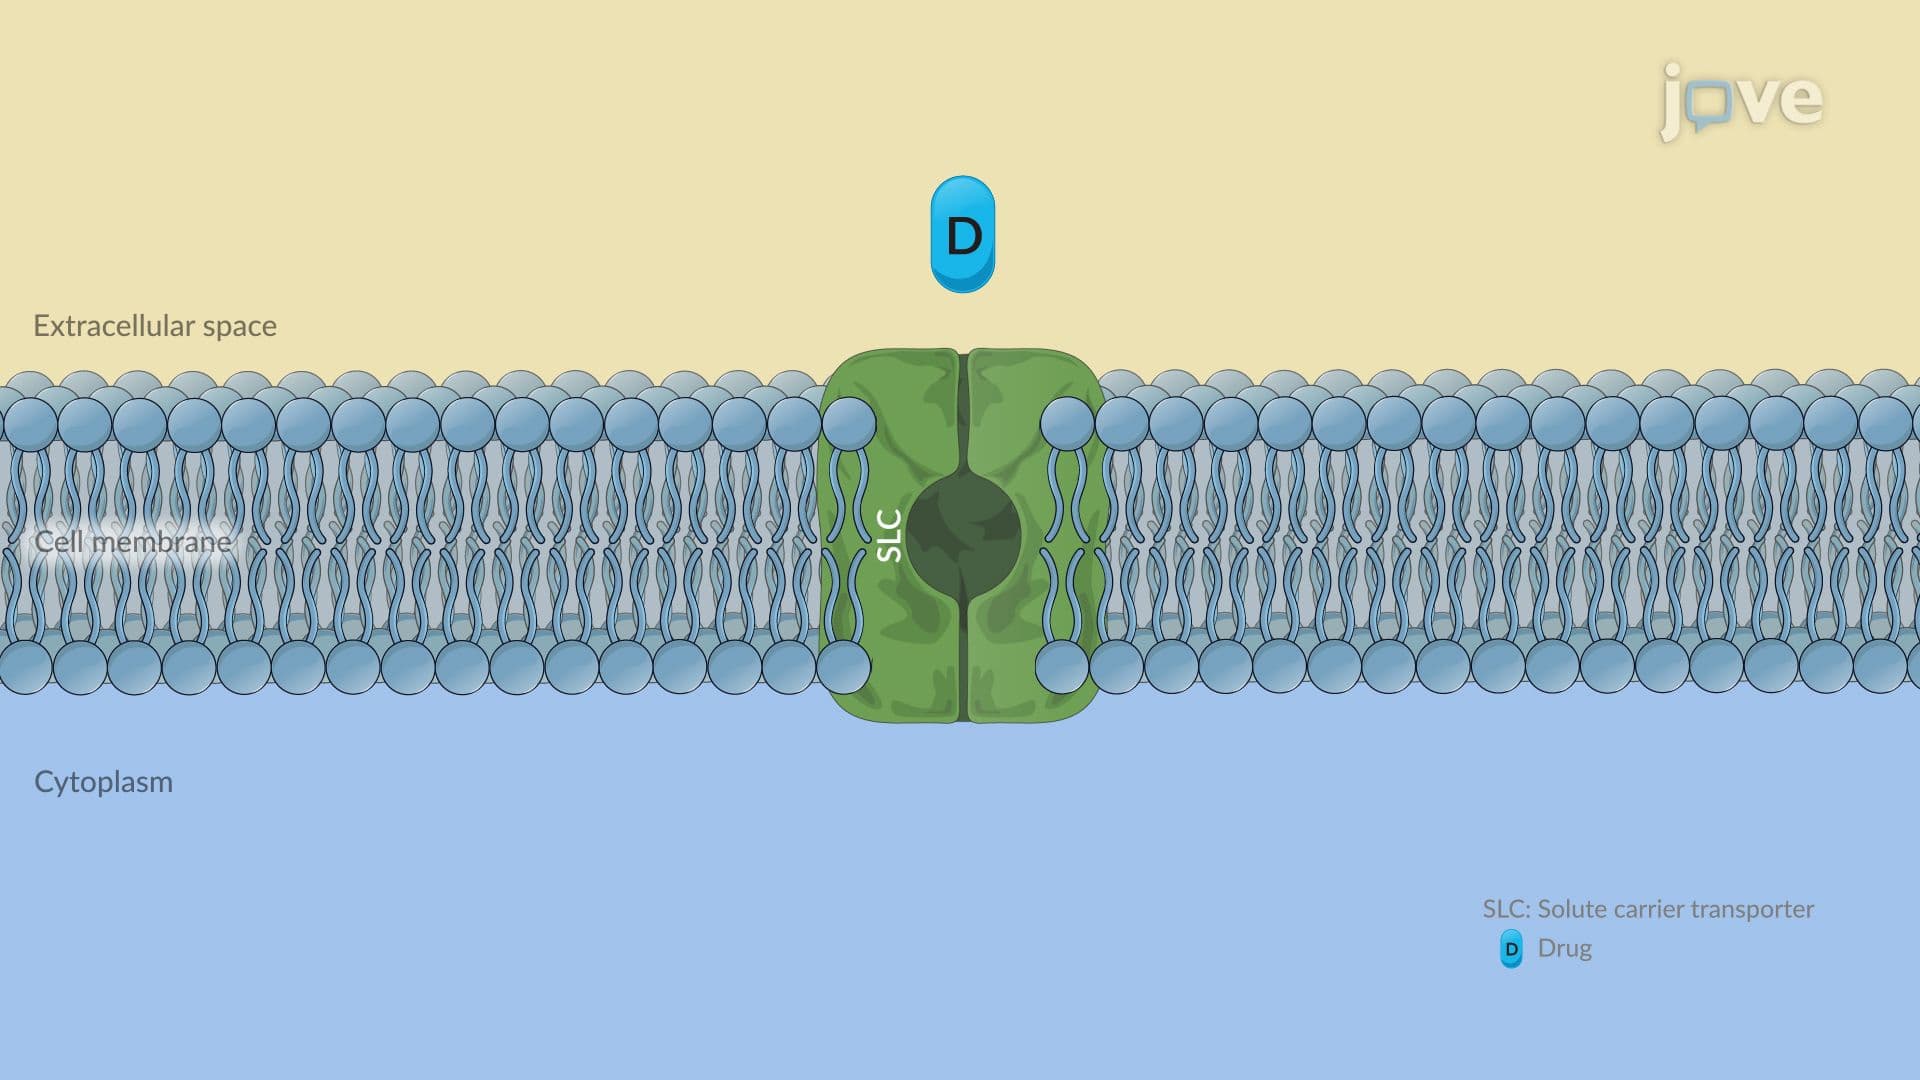
Pharmacogenetics of Drug Transporters: P-Glycoprotein and Solute Carrier Transporters
 01:22
Lysosomal Hydrolases
 01:20
Inborn Errors of Metabolism
 01:31
Translation
Translation is the process of synthesizing proteins from the genetic information carried by messenger RNA (mRNA). Following transcription, it constitutes the final step in the expression of genes. This process is carried out by ribosomes, complexes of protein and specialized RNA molecules. Ribosomes, transfer RNA (tRNA), and other proteins produce a chain of amino acids—the polypeptide—as the end product of translation.
Translation Produces the Building Blocks of...
01:31Translation
Translation Produces the Building Blocks of Life
Proteins are...