Related Experiment Video
Updated: Apr 9, 2026


Assessment of Vascular Function in Patients With Chronic Kidney Disease
Published on: June 16, 2014
The relationship between weight, height and body mass index with hemodynamic parameters is not same in patients with
Baris Afsar1, Rengin Elsurer2, Zeki Soypacaci3
1Department of Nephrology, Ferhuniye Mah. Hastane Cad. Konya Numune State Hospital, 42690, Konya, Turkey. afsarbrs@yahoo.com.

Insights
In patients with chronic kidney disease (CKD), higher weight and body mass index (BMI) are linked to decreased arterial stiffness. This contrasts with non-CKD patients, where these factors increase stiffness.
Area of Science:
- Cardiology
- Nephrology
- Clinical Physiology
Background:
- Anthropometric measurements correlate with clinical outcomes, but this relationship varies in specific conditions like chronic kidney disease (CKD).
- Understanding these variations is crucial for managing cardiovascular health in CKD patients.
Purpose of the Study:
- To investigate the relationship between height, weight, and body mass index (BMI) with hemodynamic and arterial stiffness parameters.
- To compare these relationships separately in patients with and without CKD.
Main Methods:
- A cross-sectional study involving 381 hypertensive patients (226 with CKD, 155 without).
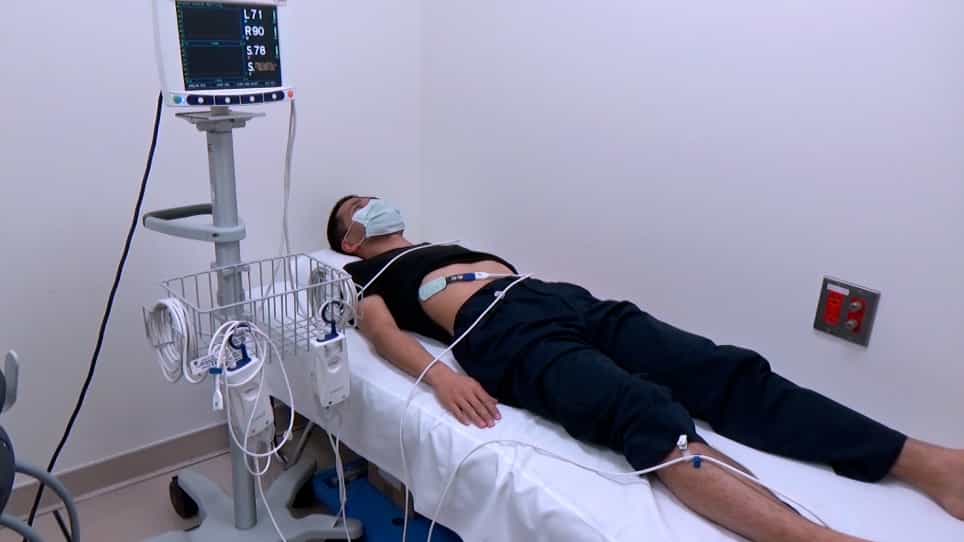
- Measurements included routine labs, 24-h urine collection, augmentation index (Aix@75), and pulse wave velocity (PWV) using the mobil-O-Graph device.
Main Results:
- In non-CKD patients, height correlated inversely with Aix@75; weight and BMI positively associated with PWV.
- In CKD patients, weight and BMI showed an inverse relationship with PWV, indicating decreased arterial stiffness with increasing weight/BMI.
- The association between BMI, weight, and arterial stiffness was positive in normal individuals but negative in CKD patients.
Conclusions:
- The relationship between anthropometric measurements (height, weight, BMI) and hemodynamic/arterial stiffness parameters is significantly different in patients with and without CKD.
- These findings highlight the complex interplay between body composition and cardiovascular health in the context of kidney disease.
Background:
Although anthropometric measurements are related with clinical outcomes; these relationships are not universal and differ in some disease states such as in chronic kidney disease (CKD). The current study was aimed to analyze the relationship between height, weight and BMI with hemodynamic and arterial stiffness parameters both in normal and CKD patients separately.
Methods:
This cross-sectional study included 381 patients with (N 226) and without CKD (N 155) with hypertension. Routine laboratory and 24-h urine collection were performed. Augmentation index (Aix) which is the ratio of augmentation pressure to pulse pressure was calculated from the blood pressure waveform after adjusted heart rate at 75 [Aix@75 (%)]. Pulse wave velocity (PWV) is a simple measure of the time taken by the pressure wave to travel over a specific distance. Both [Aix@75 (%)] and PWV which are measures of arterial stiffness were measured by validated oscillometric methods using mobil-O-Graph device.
Results:
In patients without CKD, height is inversely correlated with [Aix@75 (%)]. Additionally, weight and BMI were positively associated with PWV in multivariate analysis. However, in patients with CKD, weight and BMI were inversely and independently related with PWV. In CKD patients, as weight and BMI increased stiffness parameters such as Aix@75 (%) and PWV decreased. While BMI and weight are positively associated with arterial stiffness in normal patients, this association is negative in patients with CKD.
Conclusion:
In conclusion, height, weight and BMI relationship with hemodynamic and arterial stiffness parameters differs in patients with and without CKD.
Related Concept Videos
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:25
Chronic Kidney Disease I: Introduction
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant