Related Experiment Video For Active surveillance
Updated: Apr 9, 2026

A New Technique for Treating Low-risk Prostate Cancer—Super Active Surveillance
Published on: November 7, 2025
Image-based monitoring of targeted biopsy-proven prostate cancer on active surveillance: 11-year experience
Sunao Shoji1,2, Osamu Ukimura3, Andre Luis de Castro Abreu1
1Center for Prostate Cancer Focal Therapy, Keck School of Medicine, USC Institute of Urology, University of Southern California, 1441 Eastlake Ave, Suite 7416, Los Angeles, CA, 90089, USA.

Purpose:
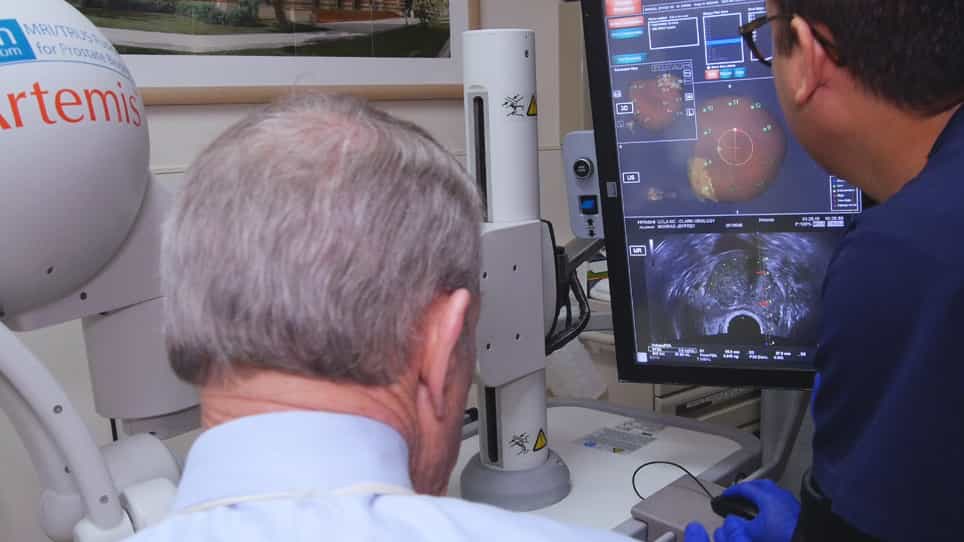
To report our 11-year experience of Active Surveillance (AS) program focusing on modern transrectal ultrasound (TRUS)-based monitoring of targeted biopsy-proven cancer lesion.
Methods:
Consecutive patients on AS, who had targeted biopsy-proven lesion followed by at least a repeat surveillance biopsy and three times TRUS monitoring of the identical visible lesion, were included. Doppler grade of blood flow signal within the lesion was classified from grade 0 to 3. Biopsy-proven progression was defined as upgrade of Gleason score or 25% or greater increase in cancer core involvement.
Results:
Fifty patients were included in this study. Clinical variables (median) included age (61 years), clinical stage (T1c, 42;T2, 8), PSA (4.6 ng/ml), and Gleason score (3 + 3, n = 41;3 + 4, n = 9). Of the 50 patients, 34 demonstrated pathological progression at a median follow-up of 4.4 years. In comparing between without (n = 16) and with (n = 34) pathological progression, there were significant differences in cancer core involvement at entry (p = 0.003), the major axis diameter (p = 0.001) and minor axis diameter (p = 0.001) of the visible lesion at entry, increase in the major axis diameter (p = 0.005) and minor axis diameter (p = 0.013), and upgrade of Doppler grade (p < 0.0001). In multivariate analysis for predicting pathological progression, the increase (≥25%) in diameter of biopsy-proven lesion (hazard ratio, 15.314; p = 0.023) and upgrade of Doppler grade (hazard ratio, 37.409; p = 0.019) were significant risk factors.
Conclusions:
Longitudinal monitoring of the TRUS-visible biopsy-proven cancer provides a new opportunity to perform per-lesion-based AS. The increase in diameter and upgrade of Doppler grade of the lesion were significant risk factors for biopsy-proven progression on AS.