Related Experiment Video
Updated: Apr 8, 2026
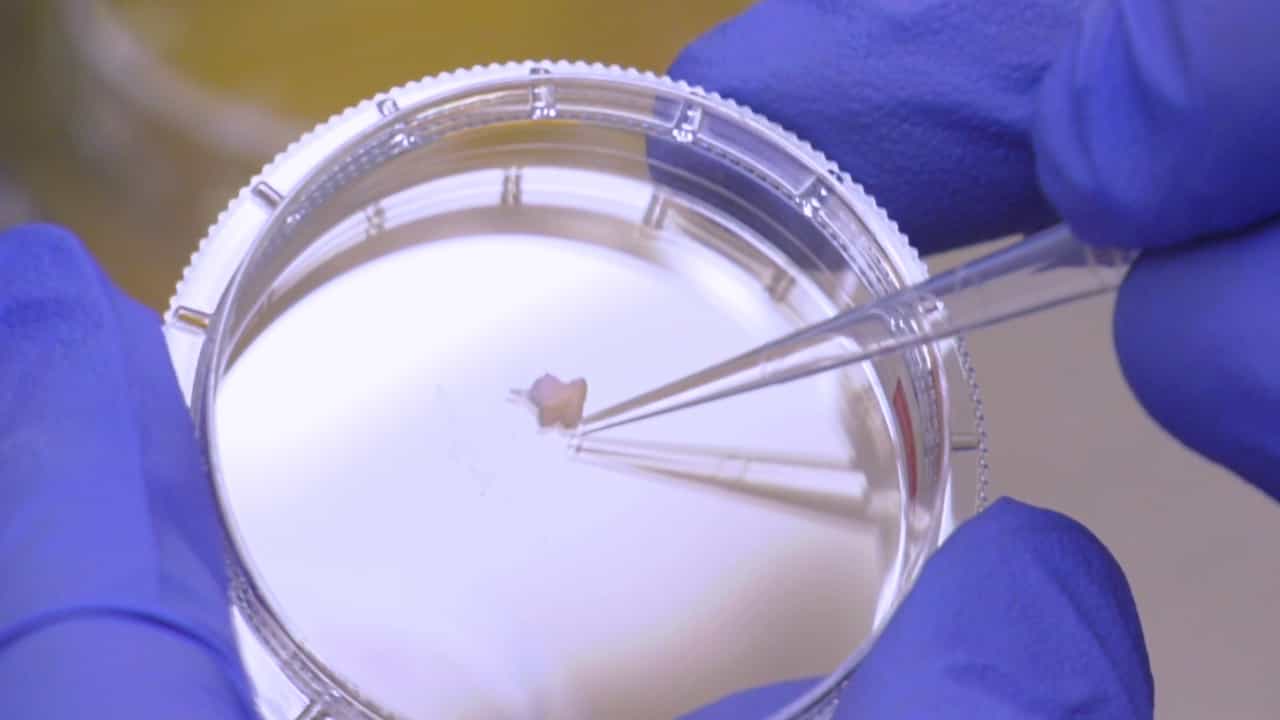

Author Spotlight: Generation of Patient-Derived Podocytes from Skin Biopsies
Published on: May 26, 2023
PP034. Renal histology in preeclampsia: A special role for the podocyte

Insights
Preeclampsia (PE) causes characteristic kidney lesions, but not chronic ones that explain long-term renal risks. Podocyte numbers remain unchanged in PE kidneys, suggesting hypertension or angiogenic imbalance doesn't alter them.
Area of Science:
- Nephrology
- Obstetrics
- Pathology
Background:
- Preeclampsia (PE) significantly impacts the kidneys, increasing risks for future microalbuminuria and end-stage renal disease (ESRD).
- While endotheliosis and podocyte changes are noted in PE, the presence of chronic renal lesions contributing to long-term risk remains unclear.
Purpose of the Study:
- To investigate similarities in renal lesions between preeclampsia (PE) and chronic hypertension in young women.
- To determine if podocyte numbers are reduced in the kidneys of women with PE and chronic hypertension.
Main Methods:
- A nationwide autopsy-tissue database (PALGA) was used to collect renal tissues from 11 PE patients.
- Control groups included pregnant women without hypertension (n=25), and non-pregnant women with (n=14) and without (n=13) chronic hypertension.
- WT-1 staining quantified glomerular podocyte numbers.
Main Results:
- Preeclampsia (PE) cases exhibited MPGN-like lesions without immune deposits, along with tram tracking and podocyte changes, not seen in controls.
- Endotheliosis was more prevalent in PE but also observed sporadically in pregnant and hypertensive controls.
- Chronic ischemic lesions were primarily found in women with chronic hypertension, not in PE or other control groups. Glomerular podocyte counts did not differ significantly across all groups.
Conclusions:
- MPGN-like lesions are characteristic of preeclampsia (PE) but chronic lesions explaining long-term renal impairment risk were not identified.
- No differences in podocyte numbers were observed between PE, chronic hypertension, and control groups.
- These findings suggest that neither persistent hypertension nor angiogenic factor imbalance in PE leads to observable changes in kidney podocyte count.
Introduction:
In preeclampsia (PE), the kidney is one of the major target organs. Growing evidence suggests PE increases the risk of subsequent microalbuminuria and end-stage renal disease (ESRD). Endotheliosis and podocyte changes due to anti-angiogenic factors seem to be salient features of PE. However, it is unknown whether chronic lesions are present in PE patients that could contribute to this increased risk.
Objectives:
We hypothesized that women with PE and young women with chronic hypertension might show similarity in renal lesions. Furthermore, we investigated if the number of podocytes within the kidney is decreased under these different circumstances. Methods We performed a search for renal autopsy-tissues using a nationwide computerized database (PALGA) to collect a unique large cohort of preeclamptic patients (n=11). Three control groups were included consisting of young women who died during pregnancy without hypertension (n=25) and non-pregnant controls with (n=14) and without (n=13) chronic hypertension. WT-1 staining was used to quantify the number of podocytes. Results Women with PE had MPGN-like lesions without immune-deposits. Tram tracking and podocyte changes were exclusively observed in these patients. Endotheliosis was significantly more present in PE, but sporadically seen in pregnant- and hypertensive controls. Chronic ischaemic lesions were predominantly found in young women with chronic hypertension, and not in PE and other controls. No differences were found in glomerular podocyte number between the study groups.
Conclusion:
All women with PE had MPGN-like lesions in their kidneys which was therefore regarded characteristic for PE. In contrast, no chronic lesions were observed in PE which could explain the increased risk of impaired renal function later in life. Interestingly, we demonstrated no difference in podocyte number between study groups. These results might suggest that neither persistent hypertension or dysbalance in angiogenic factors (i.e. preeclampsia) cause an observable change in podocyte number within the kidney.

Related Concept Videos
 01:20
Renal Corpuscle
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous...
 01:24
Nephrotic Syndrome I : Introduction
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
 01:10
Nephrons
 01:29
Acute Kidney Injury II: Pathophysiology