Related Experiment Video
Updated: Apr 8, 2026

An In Vitro Model for the Study of Cellular Pathophysiology in Globoid Cell Leukodystrophy
Published on: October 21, 2014
The changing faces of IgG4-related disease: Clinical manifestations and pathogenesis
Arshia Duza Islam1, Carlo Selmi2, Ananya Datta-Mitra3
1Department of Internal Medicine, Division of Rheumatology, Allergy and Clinical Immunology, University of California Davis, School of Medicine, Davis, CA, USA; VA Medical Center Sacramento, Mather, CA, USA.

Abstract:
Since the earliest reports in 2001, immunoglobulin G4 (IgG4)-related disease has been defined as an autoimmune systemic disease characterized by the lymphoplasmacytic infiltration of affected tissues leading to fibrosis and obliterative phlebitis along with elevated serum IgG4 levels. Prior to this unifying hypothesis, a plethora of clinical manifestations were considered as separate entities despite the similar laboratory profile. The pathology can be observed in virtually all organs and may thus be a challenging diagnosis, especially when the adequate clinical suspicion is not present or when obtaining a tissue biopsy is not feasible. Nonetheless, the most frequently involved organs are the pancreas and exocrine glands but these may be spared. Immunosuppressants lead to a prompt clinical response in virtually all cases and prevent histological sequelae and, as a consequence, an early differential diagnosis from other conditions, particularly infections and cancer, as well as an early treatment should be pursued. We describe herein two cases in which atypical disease manifestations were observed, i.e., one with recurrent neck lymph node enlargement and proptosis, and one with jaundice. Our understanding of the pathogenesis of IgG4-related disease is largely incomplete but data support a significant role for Th2 cytokines with the contribution of innate immunity factors such as Toll-like receptors, macrophages and basophils. Further, macrophages activated by IL4 overexpress B cell activating factors and contribute to chronic inflammation and the development of fibrosis. We cannot rule out the possibility that the largely variable disease phenotypes reflect different pathogenetic mechanisms and the tissue microenvironment may then contribute to the organ involvement.
More Related Videos
 06:35
An Immunohistopathologic Study to Profile the Folate Receptor Beta Macrophage and Vascular Immune Microenvironment in Giant Cell Arteritis
Published on: February 8, 2019
 06:02
Experimental Approaches for Biochemical Analysis of Glial Fibrillary Acidic Protein and Its Disease-associated Variants
Published on: November 28, 2025
Related Concept Videos
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation,...
 01:05
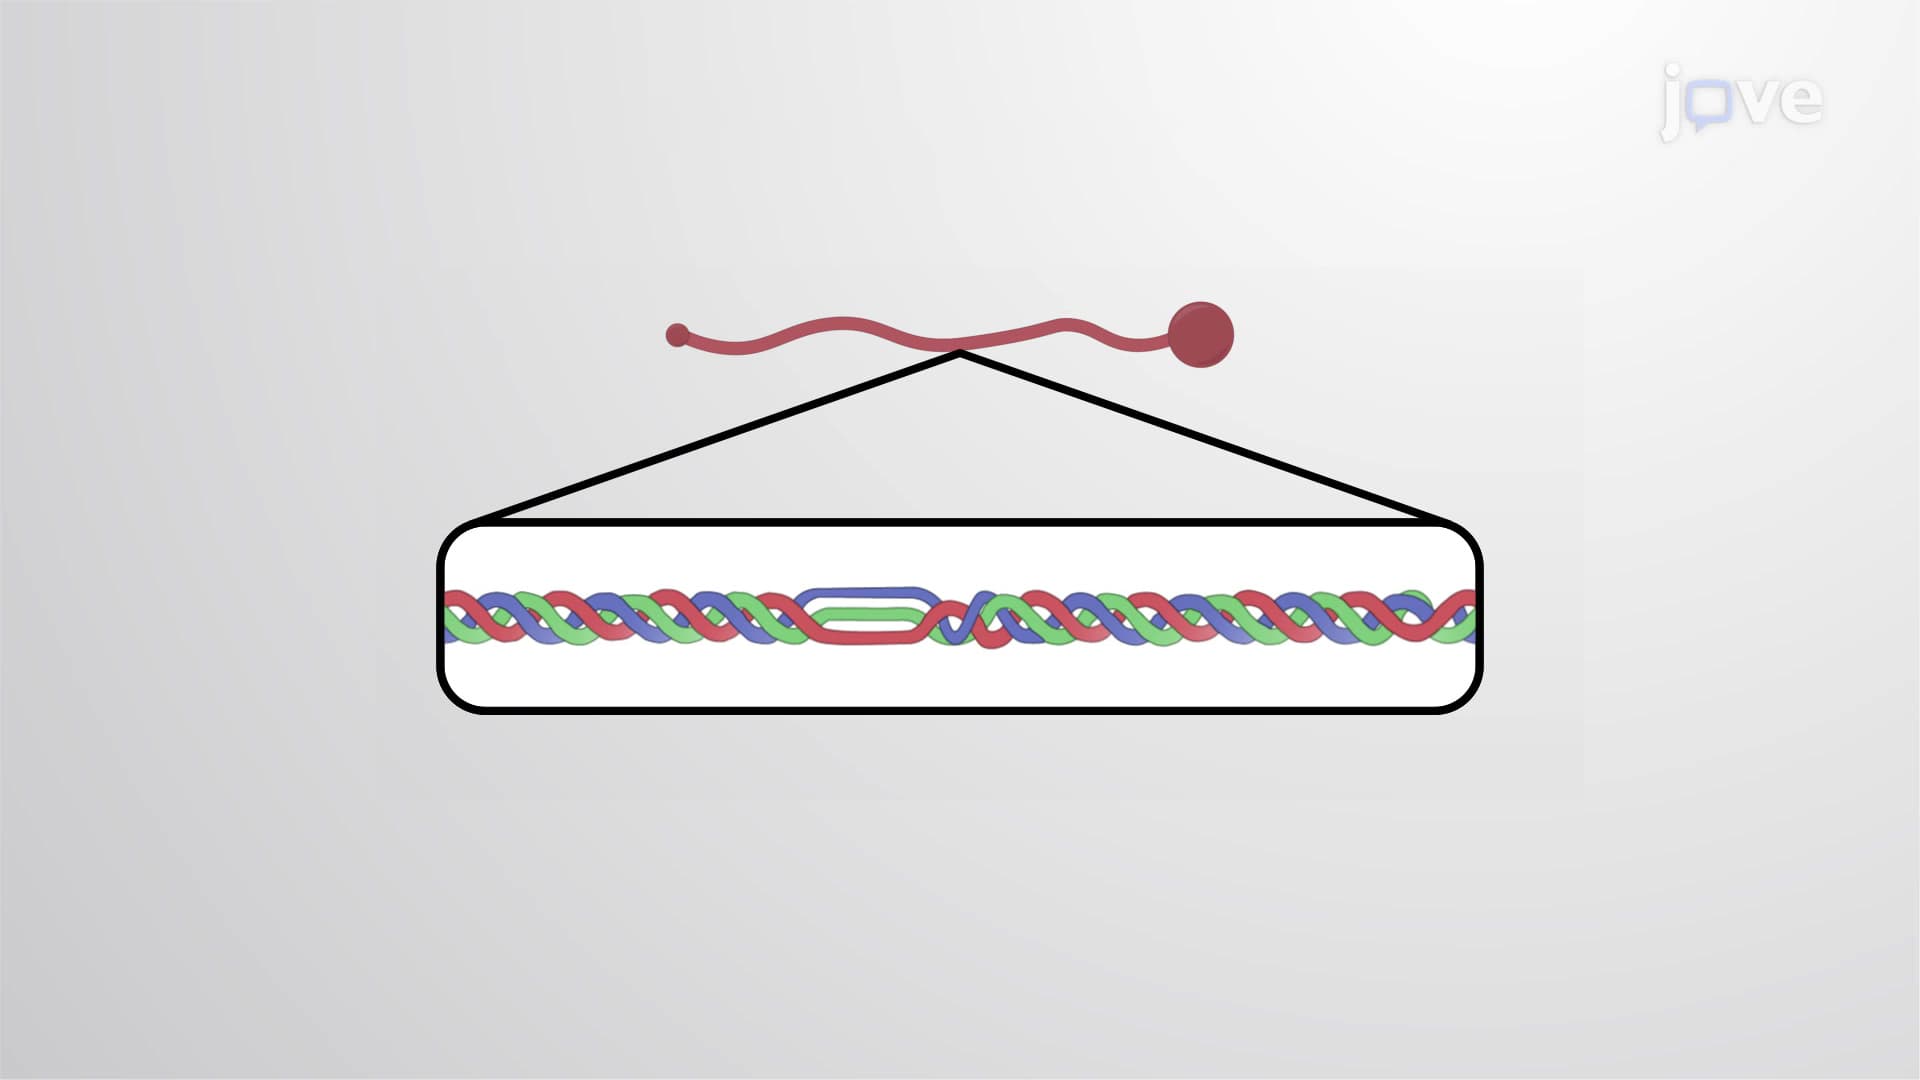
Type IV Collagen of Basal Lamina
A type IV collagen molecule has six alpha chains which can...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:22
Activation and Inactivation of G Proteins
 01:09
GPCRs Regulate Adenylyl Cylase Activity
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...