Related Experiment Video
Updated: Apr 7, 2026
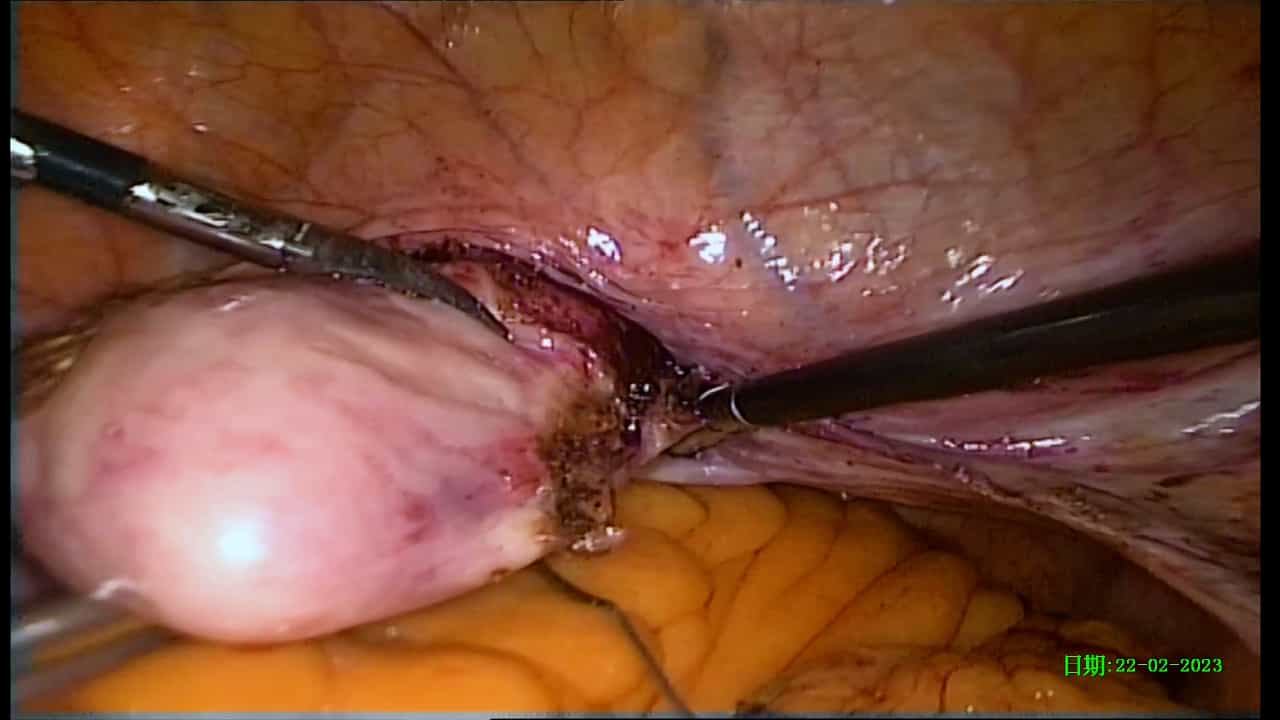

Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
Anatomical insights into sacrocolpopexy for multicompartment pelvic organ prolapse
Alfredo Ercoli1,2, Giuseppe Campagna3, Vincent Delmas2,4
1Policlinico Abano Terme-Urogynaecology Unit, Piazza Cristoforo Colombo, 1 , Abano Terme (PD), Italy.

Aims:
Pelvic organ prolapse occurs in 50% of parous women. Laparoscopic sacrocolpopexy (LSCP) is a common surgical procedure for restoring pelvic anatomy and function. The aim of this study is to evaluate surgical anatomy and anatomical modifications induced by standardized LSCP.
Methods:
Ten fresh female cadavers underwent LSCP, six subsequently underwent standard anatomical dissection, and four had sagittal anatomical dissection. Four cadavers were used as control subjects; two of them underwent standard anatomical dissection, and two had sagittal anatomical dissection.
Results:
Vesicovaginal space dissection resulted in an arrow-shaped space limited by the trigone and vesical branches of the uterine artery. Rectovaginal space dissection resulted in an inverted V-shaped space marked by the utero-sacral and rectovaginal ligaments, the cranial end of the perineal body and the levator ani muscle. Exposing the longitudinal vertebral ligament through a peritoneal and presacral fascia incision along the medial border of the right common iliac artery allowed the identification and the preservation of the right hypogastric nerve. The anterior mesh stretched across the proximal half of the anterior vaginal wall, and the cervix towards the sacral promontory provided excellent cervix suspension and anterior-vaginal wall support with a concomitant stretch of the pubocervical fascia. The median angle formed by the axis of the infra-levatorial vagina with the axis of the supra-levatorial vagina changed from 142° to 171° and determined the linearization-ventralization of the vaginal canal.
Conclusions:
LSCP can be performed in a nerve-sparing, standardized fashion, providing excellent apical suspension and anterior vaginal wall support. Neurourol. Urodynam. 35:813-818, 2016. © 2015 Wiley Periodicals, Inc.
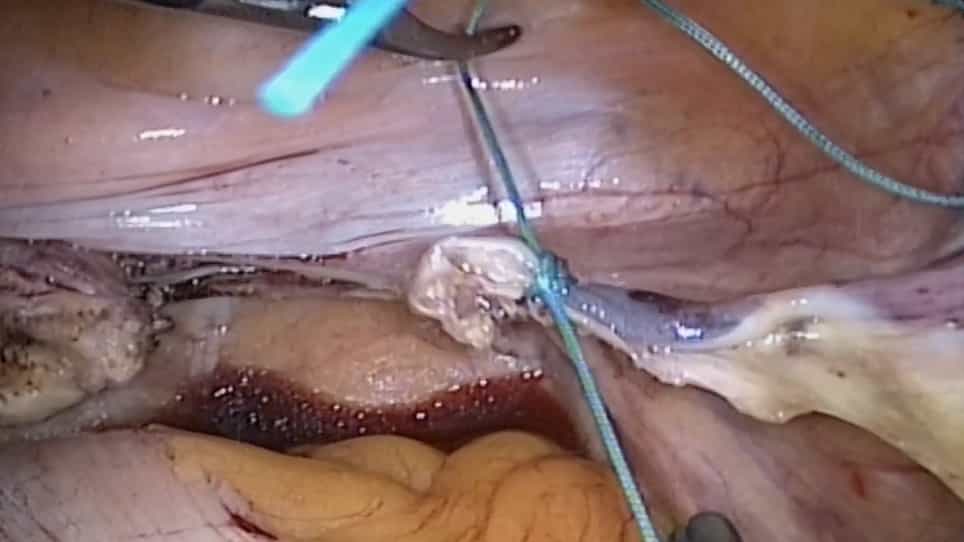

Related Concept Videos
 01:26
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:21
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...