Related Experiment Video
Updated: Apr 7, 2026
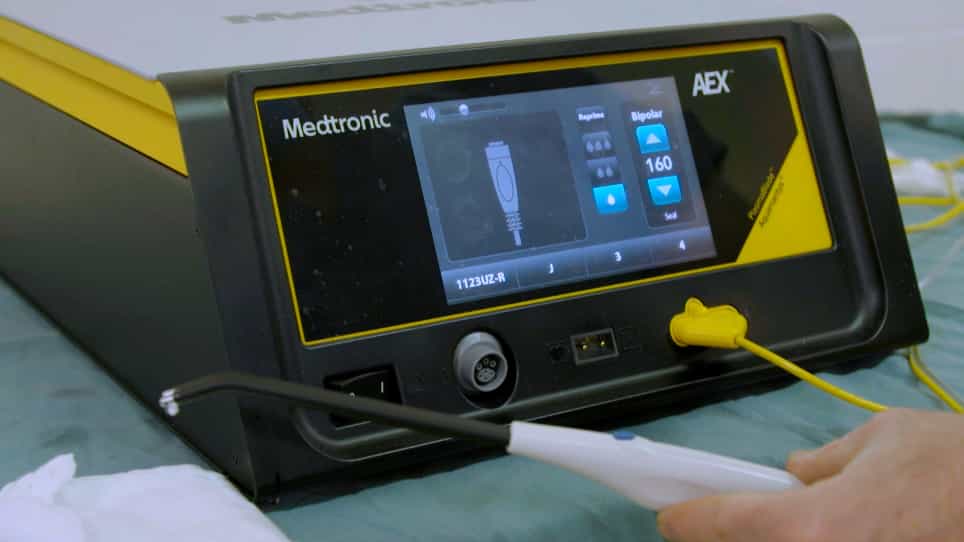
A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Indications for use of damage control surgery and damage control interventions in civilian trauma patients: A scoping
Derek J Roberts1, Niklas Bobrovitz, David A Zygun
1From the Departments of Surgery and Community Health Sciences and the Regional Trauma Program (D.J.R.), University of Calgary and the Foothills Medical Centre, Calgary, Alberta, Canada; Nuffield Department of Primary Care Health Sciences (N.B.), University of Oxford, Oxford, England, United Kingdom; Division of Critical Care Medicine (D.A.Z.), University of Alberta, Edmonton, Alberta, Canada; Departments of Surgery (C.G.B., A.W.K.) and Oncology (C.G.B.) and the Regional Trauma Program (C.G.B., A.W.K.), Alberta Health Sciences Research-Research Analytics (P.D.F.), and Departments of Critical Care Medicine, Medicine, and Community Health Sciences (H.T.S.), University of Calgary and the Foothills Medical Centre, Calgary, Alberta, Canada.

Background:
Variation in the use of damage control (DC) surgery across trauma centers may partially be driven by uncertainty as to when the procedure is indicated. We sought to scope the literature on DC surgery and DC interventions, identify their reported indications, and examine the content and evidence upon which they are based.
Methods:
We searched MEDLINE, EMBASE, PubMed, Scopus, Web of Science, and the Cochrane Library (1950-February 14, 2014) and the grey literature for original and nonoriginal citations reporting indications for DC surgery or DC interventions in civilian trauma patients.
Results:
Among 27,732 citations identified, we included 270 peer-reviewed articles in the scoping review. Of these, 156 (57.8%) represented original research, primarily (75.0%) cohort studies. The articles reported 1,099 indications for DC surgery and 418 indications for 15 different DC interventions. The majority of indications for DC interventions were for abdominal (56.5%) procedures, including therapeutic perihepatic packing (56.5%), temporary abdominal closure/open abdominal management (40.7%), and staged pancreaticoduodenectomy (2.8%). Most DC surgery indications were based on intraoperative findings (71.7%) and represented characteristics of the injured patient (94.5%), including their physiology (57.6%), injuries (38.9%), and/or the amount or type of resuscitation provided (14.3%). Others were dependent on characteristics of the treating surgeon (12.1%), the patient's physiologic response to trauma care (9.6%), and/or the trauma care environment (1.5%). Approximately half (49.5%) included a decision threshold (e.g., pH < X) and, while most (74.7%) were based on a single clinical finding/injury, 25.3% required the presence of multiple findings concurrently. Only 87 indications were evaluated in original research studies and only 9 by more than one study.
Conclusion:
The vast number, varying underlying content, and lack of original research relating to indications for DC suggests that substantial uncertainty exists around when the procedure is indicated and highlights the need to establish evidence-informed consensus indications.

Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:21
Cardiopulmonary Resuscitation I: Adult
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management