Related Experiment Video
Updated: Apr 6, 2026
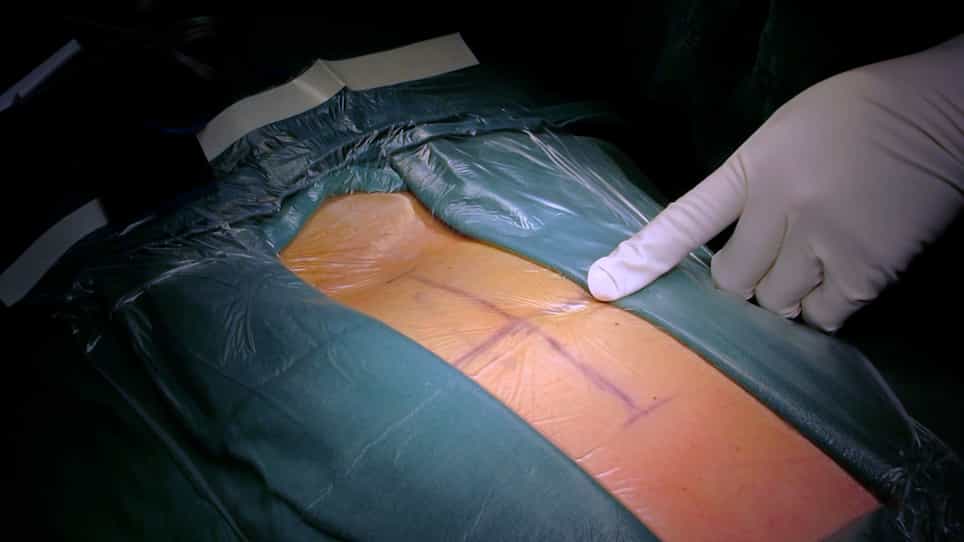

Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
What is the Risk of Developing Proximal Junctional Kyphosis During Growth Friendly Treatments for Early-onset
Ron El-Hawary1, Peter Sturm, Patrick Cahill
1*IWK Health Centre, Halifax, NS, Canada †Department of Pediatric Orthopaedics, Cincinnati Children's Hospital Medical Center, Cincinnati, OH ‡Orthopedic Surgery, Shriners Hospital Philadelphia, Philadelphia, PA §Division of Pediatric Orthopaedic Surgery, New York Presbyterian Morgan Stanley Children's Hospital, Columbia University Medical Center, New York, NY ∥Alfred I. duPont Hospital for Children, Wilmington, DE ¶Orthopedic Surgery, Orthopedic and Neurosurgical Specialists, Haddonfield **Orthopaedic Surgery, University of Medicine and Dentistry of New Jersey, Newark, NJ #Shriners Hospital Portland, Children Orthpaedics, Portland, OR ††Primary Children's Hospital, Pediatric Orthopaedics, Salt Lake City, UT.

Background:
Rib-based and spine-based systems are commonly used distraction-based growth friendly treatments for early-onset scoliosis (EOS). Our primary purpose was to determine the risk of developing postoperative proximal junctional kyphosis (PJK) during distraction-based growth friendly surgery.
Methods:
A multicenter, retrospective, radiographic comparison was performed for a group of 40 children with EOS who were treated with posterior distraction-based implants. PJK was defined as proximal junction sagittal angle (PJA)≥10 degrees and PJA at least 10 degrees greater than preoperative.
Results:
Eight subjects (20%) at immediate postoperative follow-up and 11 subjects (27.5%) at minimum 2-year follow-up had developed PJK. The risk of developing PJK between rib-based and spine-based growing systems was not significantly different at immediate postoperative (17% vs. 25%) or at final (25% vs. 31%) follow-ups.Further analysis combining both treatment groups demonstrated that PJK subjects were significantly older at time of initial surgery (7.1 y PJK vs. 5.0 y no PJK). Radiographic comparisons between PJK versus no PJK: Preoperative scoliosis (69.9 vs. 76.0 degrees), thoracic kyphosis (45.1 vs. 28.7 degrees), lumbar lordosis (53.1 vs. 44.0 degrees), PJA (2.2 vs. 2.8 degrees), sagittal vertical axis (1.5 vs. 2.6 cm), pelvic incidence (52.8 vs. 47.4 degrees), pelvic tilt (14.3 vs. 8.7 degrees), and sacral slope (37.7 vs. 35.9 degrees). At both initial postoperative and at final follow-up visits, a significant difference was found for cervical lordosis 32.2 versus 14.0 degrees and 42.0 versus 16.6 degrees, respectively. Risk ratio for developing PJK at final follow-up was 2.8 for subjects with preoperative thoracic hyperkyphosis and was 3.1 for subjects with high pelvic incidence (P<0.05).
Conclusions:
The risk of developing PJK during distraction-based growth friendly treatment for EOS was 20% immediately after implantation and 28% at minimum 2-year follow-up, with no difference observed between rib-based and spine-based treatment groups. As this study identifies a significant risk of developing PJK during the treatment of EOS, it allows clinicians to preoperatively council patients and their families about this possible complication. In addition, several potential risk factors for the development of postoperative PJK were identified, but should be investigated further in future studies.
Level Of Evidence:
Level III-therapeutic study (retrospective, comparative).
More Related Videos
 07:01
Clinical Efficacy of Ultrasound-Assisted Scoliosis-Specific Exercise in Mild-Grade Adolescent Idiopathic Scoliosis
Published on: December 2, 2025
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:16
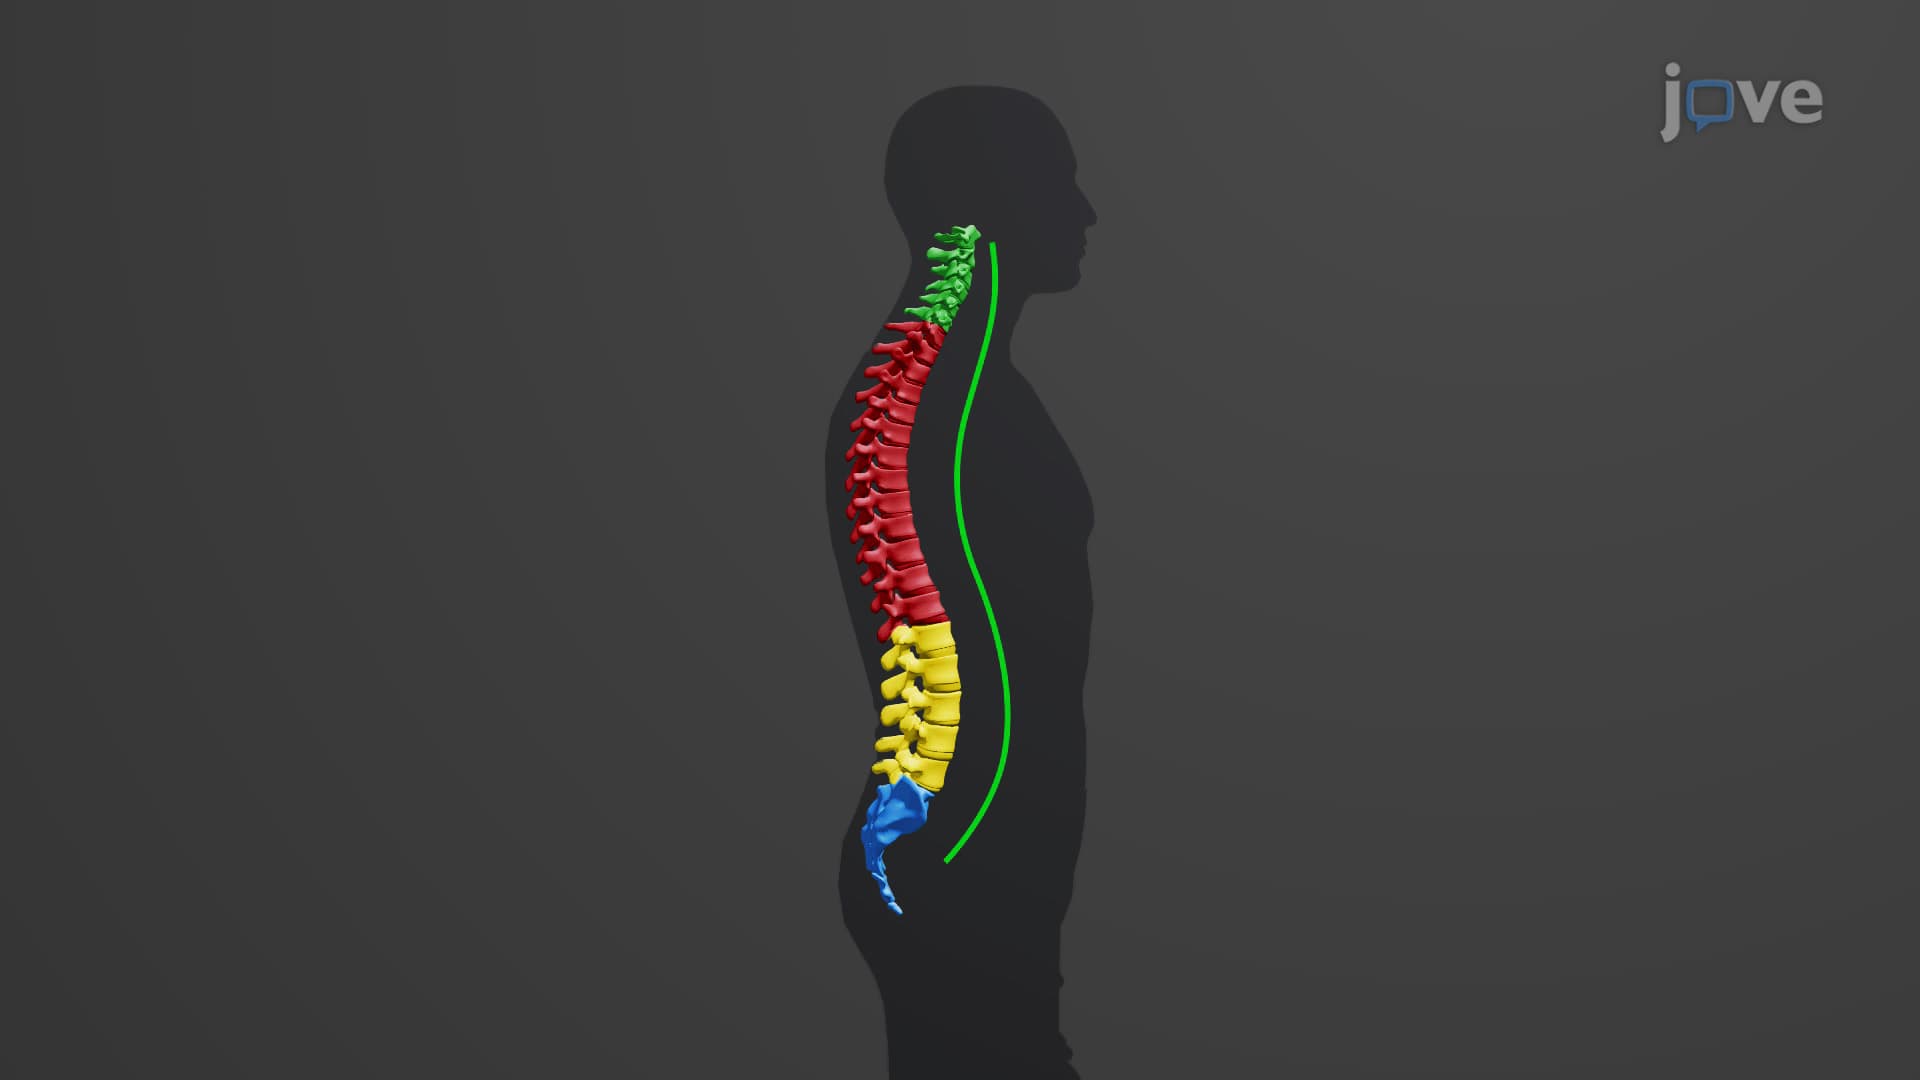
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:27
Growth of Cartilage and Bone Tissue
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:12
General Case of Eccentric Axial Loading
Consider a member subjected to equal and opposite forces that are applied along a line that does not coincide with the member's neutral axis. In unsymmetrical...