Related Experiment Video
Updated: Apr 6, 2026

Measurement of the Hepatic Venous Pressure Gradient and Transjugular Liver Biopsy
Published on: June 18, 2020
Value of the APASL severity score in patients with acute variceal bleeding: a single center experience
Go Heun Kim1, Jeong Han Kim2, Yong Jin Kim1
1Digestive Disease Center, Department of Internal Medicine, Konkuk University Hospital, Konkuk University School of Medicine, 120-1 Neungdong-ro, Hwayang-dong, Gwangjin-gu, Seoul, 143-729, Korea.

Background:
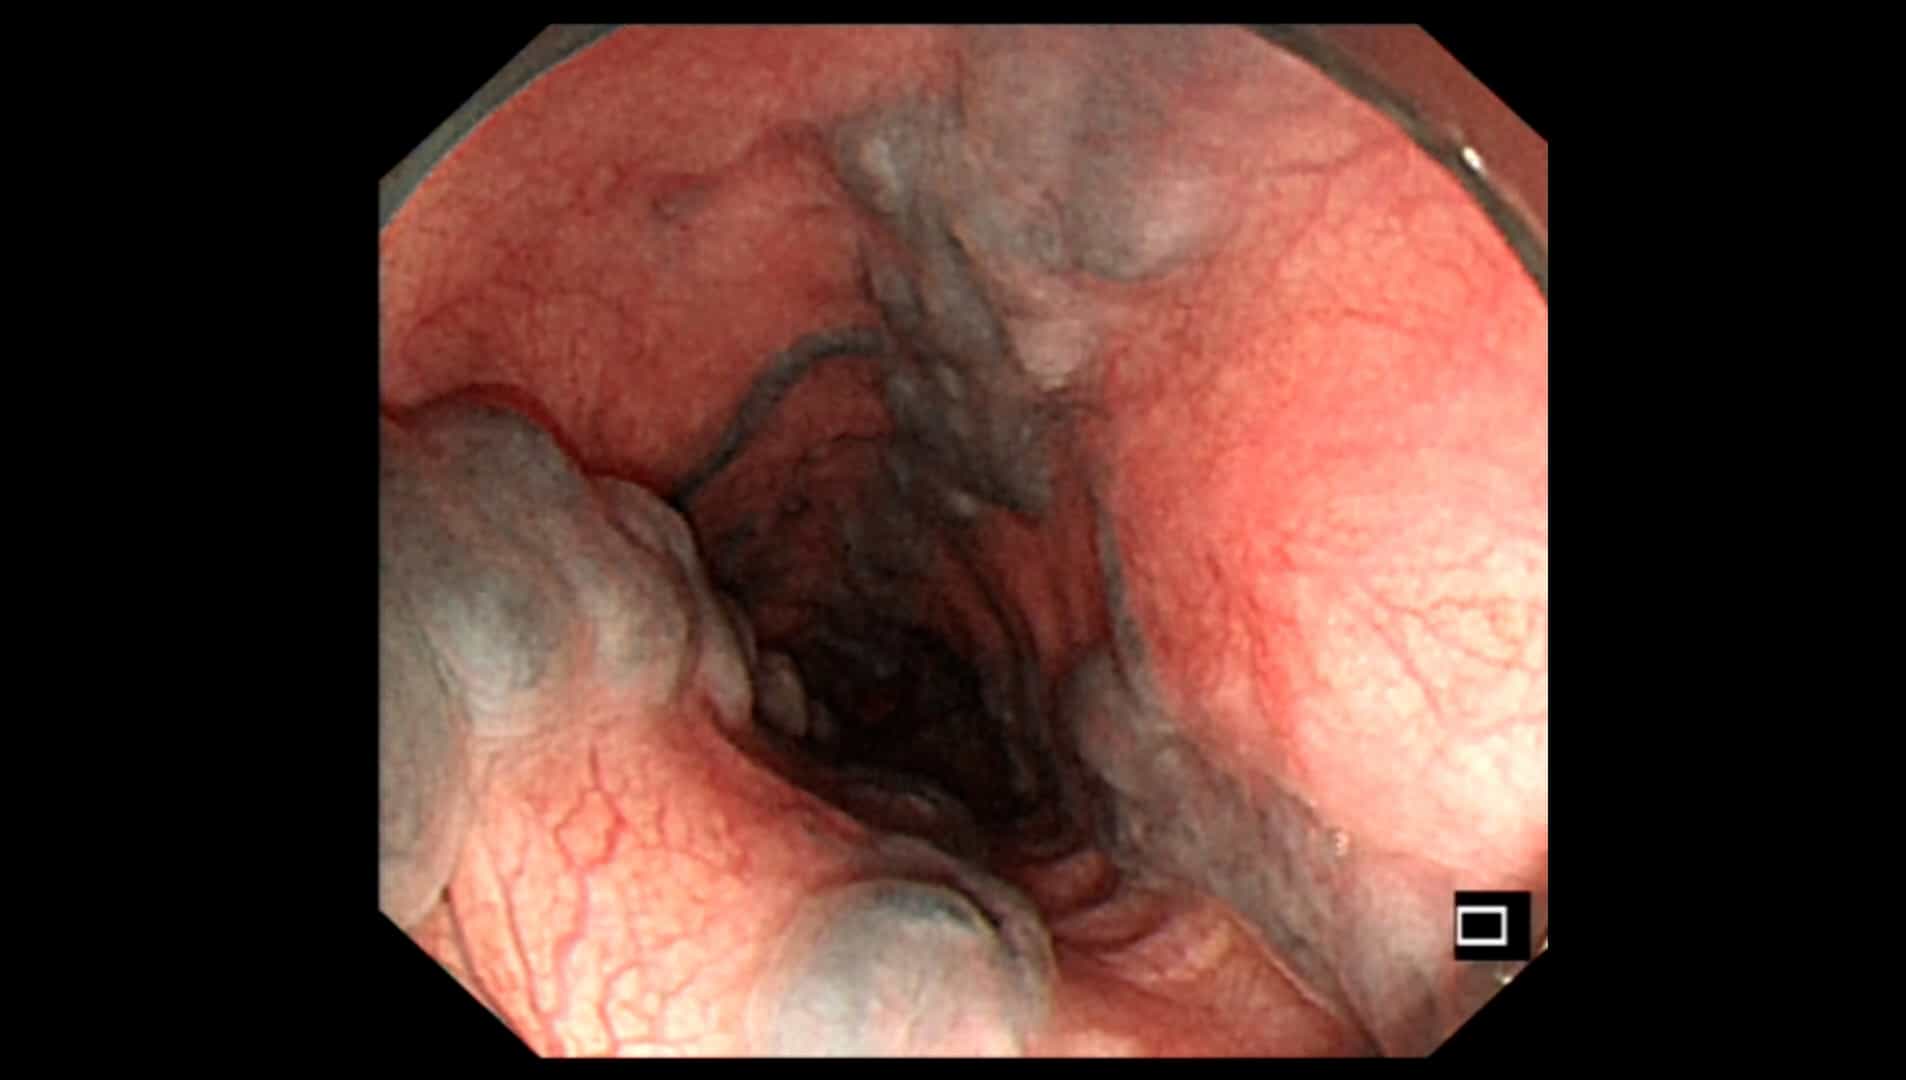
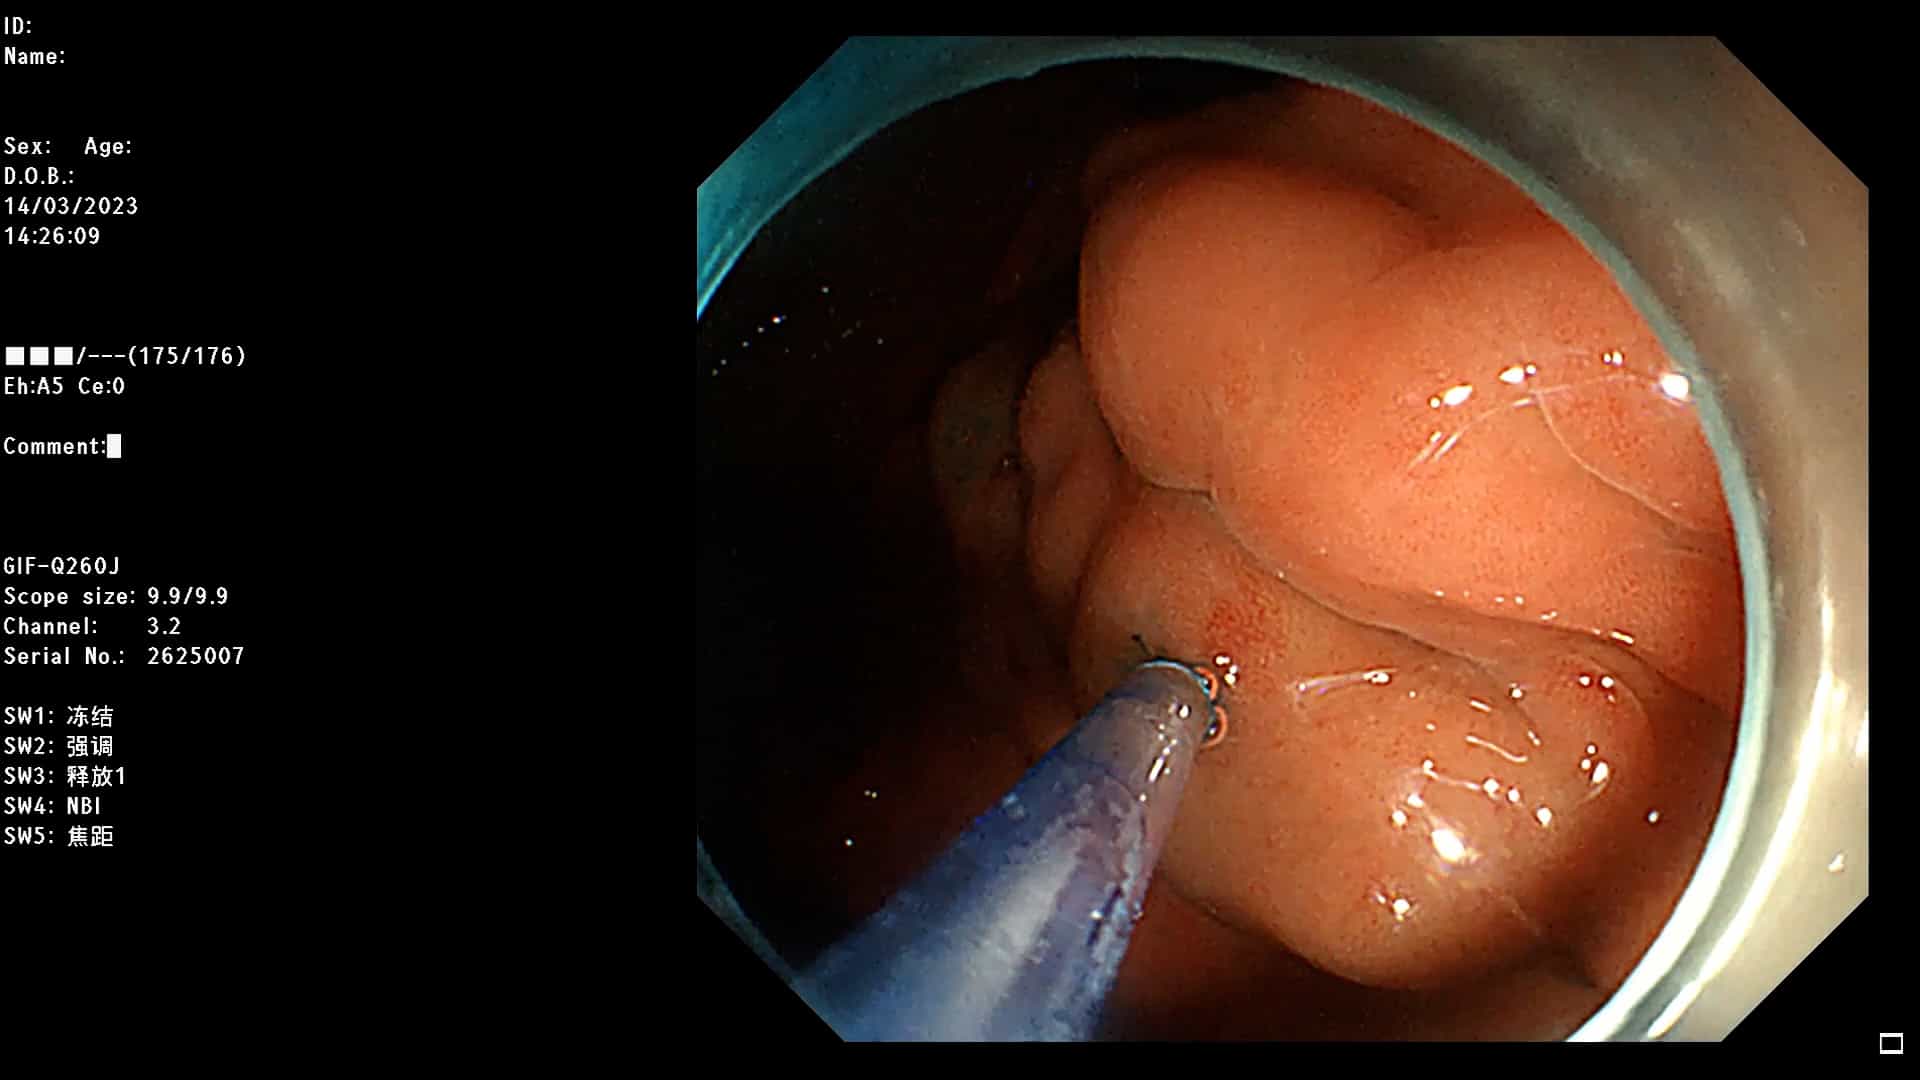
Acute variceal bleeding is a severe complication in patients with cirrhosis. The Asian Pacific Association for Study of the Liver (APASL) severity score was proposed in 2011. This score is used for evaluating the severity of acute variceal bleeding. However, as this score is largely based on expert opinion, it requires validation.
Aim:
To determine the value of the APASL severity score.
Methods:
We retrospectively reviewed the medical records of patients treated for acute variceal bleeding at Konkuk University Hospital from 2006 to 2011. The APASL severity score, Child-Pugh score, and Model for End-Stage Liver Disease (MELD) score were calculated, and predictive values for treatment failure, rebleeding, and in-hospital mortality were compared by the area under the receiver operating curve (AUROC).
Results:
A total of 136 patients were enrolled, and all patients were treated by endoscopic variceal ligation (EVL) and terlipressin combination therapy. Most patients were male (n = 123, 90.4 %), and the most common etiology was alcohol (n = 91, 66.9 %). Thirteen treatment failures, eight rebleedings, and seven in-hospital mortalities occurred. The AUROCs of the APASL severity score, Child-Pugh score, and MELD score were 0.760, 0.681, and 0.607 for treatment failure; 0.660, 0.714, and 0.677 for rebleeding; and 0.872, 0.847, and 0.735 for in-hospital mortality. A significant difference was only observed between the APASL severity score and MELD score for treatment failure (p = 0.0259).
Conclusion:
APASL severity score was a useful method for predicting treatment failure. However, the predictive value for rebleeding and in-hospital mortality were not satisfactory.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:24
Esophageal Varices-I: Introduction
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...
 01:14
SBAR II: Application of SBAR
SBAR Report from a Nurse to a Health Care Provider
S: "Hello, Dr. Smith. This is Jane, RN, from the Med Surg unit. I am calling to tell you about Ms. White in Room 210, who is experiencing increased pain and redness at her incision site. Her recent...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:27
Peptic Ulcer