Related Experiment Video
Updated: Apr 6, 2026


Testing Acetylcholine Followed by Adenosine for Invasive Diagnosis of Coronary Vasomotor Disorders
Published on: February 3, 2021
High Concordance Between Mental Stress-Induced and Adenosine-Induced Myocardial Ischemia Assessed Using SPECT in
Andrew J Wawrzyniak1, Vasken Dilsizian2, David S Krantz1
1Uniformed Services University of the Health Sciences, Bethesda, Maryland;

Insights
Mental stress causes myocardial ischemia in congestive heart failure (CHF) patients, similar to adenosine stress. This highlights the impact of daily psychosocial stressors on cardiac health in coronary artery disease patients.
Area of Science:
- Cardiology
- Psychosomatic Medicine
- Nuclear Cardiology
Background:
- Mental stress is a known trigger for myocardial ischemia.
- The prevalence and impact of mental stress-induced ischemia in congestive heart failure (CHF) patients remain largely unknown.
- Reduced left-ventricular function in CHF patients may alter their response to stress.
Purpose of the Study:
- To characterize mental stress-induced and adenosine-induced changes in myocardial perfusion and neurohormonal activation in CHF patients.
- To quantify segment-level myocardial perfusion using SPECT in response to different stressors.
- To compare the effects of mental stress versus pharmacologic stress on cardiac function in CHF.
Main Methods:
- Thirty-four coronary artery disease patients with CHF and ejection fraction <40% underwent myocardial perfusion SPECT.
- Adenosine stress and mental stress (anger recall, serial sevens) were administered on consecutive days.
- Myocardial ischemia was quantified using the 17-segment model, and cardiac dimensions and biomarkers were assessed.
Main Results:
- Sixty-eight percent of patients showed ischemia during mental stress, and 81% during adenosine stress.
- Perfusion defects induced by mental stress and adenosine were highly correlated.
- Both stressors caused significant cardiac dilatation (increased end-diastolic and end-systolic dimensions), with no significant difference in ejection fraction.
Conclusions:
- Mental stress induces myocardial perfusion defects comparable to adenosine stress in CHF patients.
- Cardiac dilatation observed suggests clinically significant changes occur with both mental and pharmacologic stress.
- Daily psychosocial stressors may contribute to the overall ischemic burden in CHF patients with coronary artery disease.
Unlabelled:
Mental stress can trigger myocardial ischemia, but the prevalence of mental stress-induced ischemia in congestive heart failure (CHF) patients is unknown. We characterized mental stress-induced and adenosine-induced changes in myocardial perfusion and neurohormonal activation in CHF patients with reduced left-ventricular function using SPECT to precisely quantify segment-level myocardial perfusion.
Methods:
Thirty-four coronary artery disease patients (mean age±SD, 62±10 y) with CHF longer than 3 mo and ejection fraction less than 40% underwent both adenosine and mental stress myocardial perfusion SPECT on consecutive days. Mental stress consisted of anger recall (anger-provoking speech) followed by subtraction of serial sevens. The presence and extent of myocardial ischemia was quantified using the conventional 17-segment model.
Results:
Sixty-eight percent of patients had 1 ischemic segment or more during mental stress and 81% during adenosine. On segment-by-segment analysis, perfusion with mental stress and adenosine were highly correlated. No significant differences were found between any 2 time points for B-type natriuretic peptide, tumor necrosis factor-α, IL-1b, troponin, vascular endothelin growth factor, IL-17a, matrix metallopeptidase-9, or C-reactive protein. However, endothelin-1 and IL-6 increased, and IL-10 decreased, between the stressor and 30 min after stress. Left-ventricular end diastolic dimension was 179±65 mL at rest and increased to 217±71 after mental stress and 229±86 after adenosine (P<0.01 for both). Resting end systolic volume was 129±60 mL at rest and increased to 158±66 after mental stress (P<0.05) and 171±87 after adenosine (P<0.07), with no significant differences between adenosine and mental stress. Ejection fraction was 30±12 at baseline, 29±11 with mental stress, and 28±10 with adenosine (P=not significant).
Conclusion:
There was high concordance between ischemic perfusion defects induced by adenosine and mental stress, suggesting that mental stress is equivalent to pharmacologic stress in eliciting clinically significant myocardial perfusion defects in CHF patients. Cardiac dilatation suggests clinically important changes with both conditions. Psychosocial stressors during daily life may contribute to the ischemic burden of CHF patients with coronary artery disease.
More Related Videos
 08:51
Intra-cardiac Side-Firing Light Catheter for Monitoring Cellular Metabolism using Transmural Absorbance Spectroscopy of Perfused Mammalian Hearts
Published on: May 12, 2019
 15:45
Cardiac Stress Test Induced by Dobutamine and Monitored by Cardiac Catheterization in Mice
Published on: February 10, 2013
Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:26
Exercise Stress Test
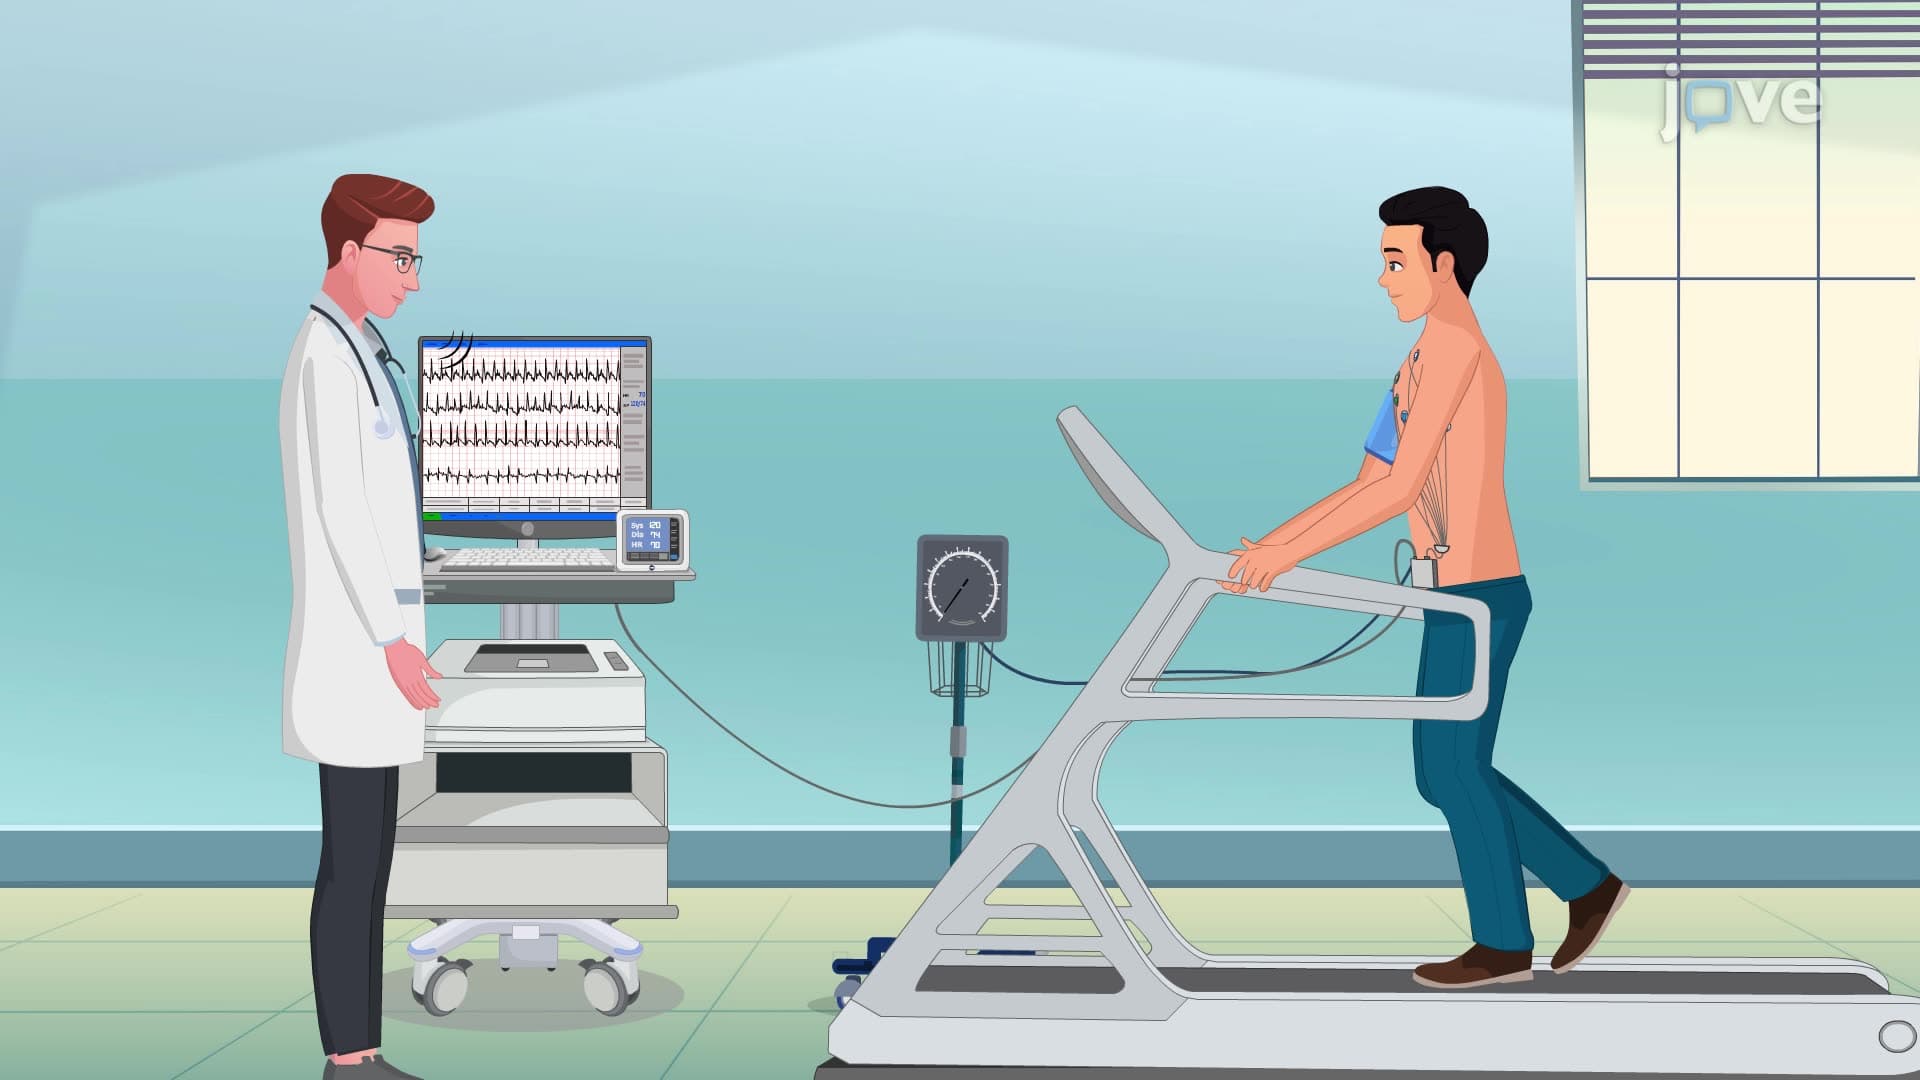
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Acute Coronary Syndrome I: Introduction
 01:29
Angina III: Clinical Manifestations and Assessment