Related Experiment Video
Updated: Apr 6, 2026
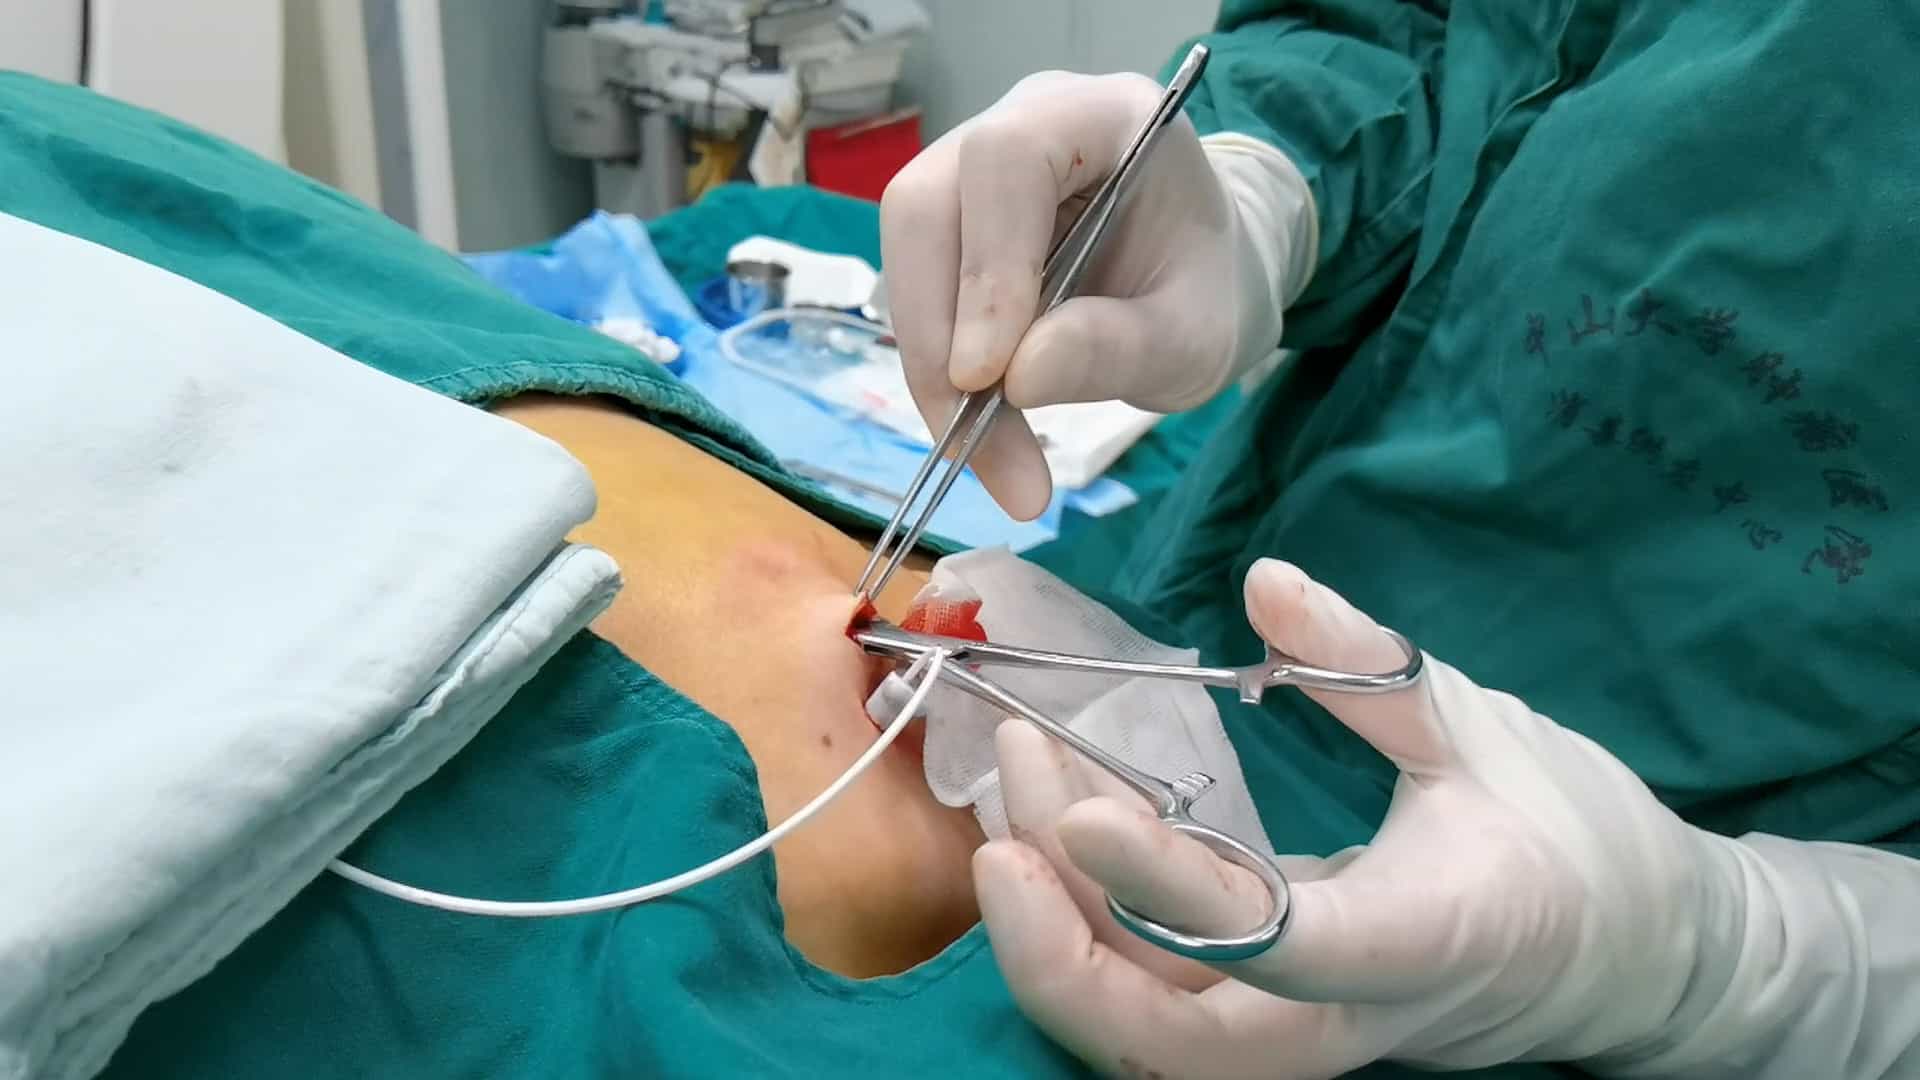

Computed Tomography (CT) Guided Implantation of a Totally Implantable Venous Access Port (TIVAP) through Subclavian Vein
Published on: January 13, 2026
Nursing and midwifery practice for maintenance of vascular access device patency. A cross-sectional survey
Samantha Keogh1, Julie Flynn1, Nicole Marsh1
1Alliance for Vascular Access Teaching and Research (AVATAR), Australia; NHMRC Centre of Research Excellence in Nursing Interventions for Hospitalised Patients (NCREN), Centre for Health Practice Innovation - Menzies Heath Institute, Griffith University, Qld, Australia; Centre of Clinical Nursing, Royal Brisbane and Women's Hospital, Qld, Australia.

Background:
Up to 85% of hospital in-patients will require some form of vascular access device to deliver essential fluids, drug therapy, nutrition and blood products, or facilitate sampling. The failure rate of these devices is unacceptably high, with 20-69% of peripheral intravenous catheters and 15-66% of central venous catheters failing due to occlusion, depending on the device, setting and population. A range of strategies have been developed to maintain device patency, including intermittent flushing. However, there is limited evidence informing flushing practice and little is known about the current flushing practices.
Objective:
The aim of the study was to improve our understanding of current flushing practices for vascular access devices through a survey of practice.
Method:
A cross-sectional survey of nurses and midwives working in the State of Queensland, Australia was conducted using a 25-item electronic survey that was distributed via the local union membership database.
Results:
A total of 1178 surveys were completed and analysed, with n=1068 reporting peripheral device flushing and n=584 reporting central device flushing. The majority of respondents were registered nurses (55%) caring for adult patients (63%). A large proportion of respondents (72% for peripheral, 742/1028; 80% for central, 451/566) were aware of their facility's policy for vascular access device flushing. Most nurses reported using sodium chloride 0.9% for flushing both peripheral (96%, 987/1028) and central devices (75%, 423/566). Some concentration of heparin saline was used by 25% of those flushing central devices. A 10-mL syringe was used by most respondents for flushing; however, 24% of respondents used smaller syringes in the peripheral device group. Use of prefilled syringes (either commercially prepared sterile or prefilled in the workplace) was limited to 10% and 11% respectively for each group. The frequency of flushing varied widely, with the most common response being pro re nata (23% peripheral and 21% central), or 6 hourly (23% peripheral and 22% central). Approximately half of respondents stated that there was no medical order or documentation for either peripheral or central device flushing.
Conclusions:
Flushing practices for vascular access device flushing appear to vary widely. Specific areas of practice that warrant further investigation include questions about the efficacy of heparin for central device flushing, increasing adherence to the recommended 10mL diameter syringe use, increased use of prefilled flush syringes, identifying and standardising optimal volumes and frequency of flushing, and improving documentation of flush orders and administration.

Related Concept Videos
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:26
Cardiac Catheterization IV: Nursing Management
 01:29
Endocarditis IV: Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...