Related Experiment Video
Updated: Apr 6, 2026

Candidate Gene Testing in Clinical Cohort Studies with Multiplexed Genotyping and Mass Spectrometry
Published on: June 21, 2018
Prospective participant selection and ranking to maximize actionable pharmacogenetic variants and discovery in the
David R Crosslin1, Peggy D Robertson2, David S Carrell3
1Department of Medicine, Division of Medical Genetics, University of Washington, 1705 NE Pacific Street, Seattle, 98195 WA USA ; Department of Genome Sciences, University of Washington, 3720 15th Avenue NE, Seattle, 98195 WA USA.

Background:
In an effort to return actionable results from variant data to electronic health records (EHRs), participants in the Electronic Medical Records and Genomics (eMERGE) Network are being sequenced with the targeted Pharmacogenomics Research Network sequence platform (PGRNseq). This cost-effective, highly-scalable, and highly-accurate platform was created to explore rare variation in 84 key pharmacogenetic genes with strong drug phenotype associations.
Methods:
To return Clinical Laboratory Improvement Amendments (CLIA) results to our participants at the Group Health Cooperative, we sequenced the DNA of 900 participants (61 % female) with non-CLIA biobanked samples. We then selected 450 of those to be re-consented, to redraw blood, and ultimately to validate CLIA variants in anticipation of returning the results to the participant and EHR. These 450 were selected using an algorithm we designed to harness data from self-reported race, diagnosis and procedure codes, medical notes, laboratory results, and variant-level bioinformatics to ensure selection of an informative sample. We annotated the multi-sample variant call format by a combination of SeattleSeq and SnpEff tools, with additional custom variables including evidence from ClinVar, OMIM, HGMD, and prior clinical associations.
Results:
We focused our analyses on 27 actionable genes, largely driven by the Clinical Pharmacogenetics Implementation Consortium. We derived a ranking system based on the total number of coding variants per participant (75.2±14.7), and the number of coding variants with high or moderate impact (11.5±3.9). Notably, we identified 11 stop-gained (1 %) and 519 missense (20 %) variants out of a total of 1785 in these 27 genes. Finally, we prioritized variants to be returned to the EHR with prior clinical evidence of pathogenicity or annotated as stop-gain for the following genes: CACNA1S and RYR1 (malignant hyperthermia); SCN5A, KCNH2, and RYR2 (arrhythmia); and LDLR (high cholesterol).
Conclusions:
The incorporation of genetics into the EHR for clinical decision support is a complex undertaking for many reasons including lack of prior consent for return of results, lack of biospecimens collected in a CLIA environment, and EHR integration. Our study design accounts for these hurdles and is an example of a pilot system that can be utilized before expanding to an entire health system.
More Related Videos
 09:34
Targeted Next-generation Sequencing and Bioinformatics Pipeline to Evaluate Genetic Determinants of Constitutional Disease
Published on: April 4, 2018
 11:35
Screening for Functional Non-coding Genetic Variants Using Electrophoretic Mobility Shift Assay EMSA and DNA-affinity Precipitation Assay DAPA
Published on: August 21, 2016
Related Concept Videos
 01:29
Pharmacogenomics: Identification of New Drug Targets
 01:29
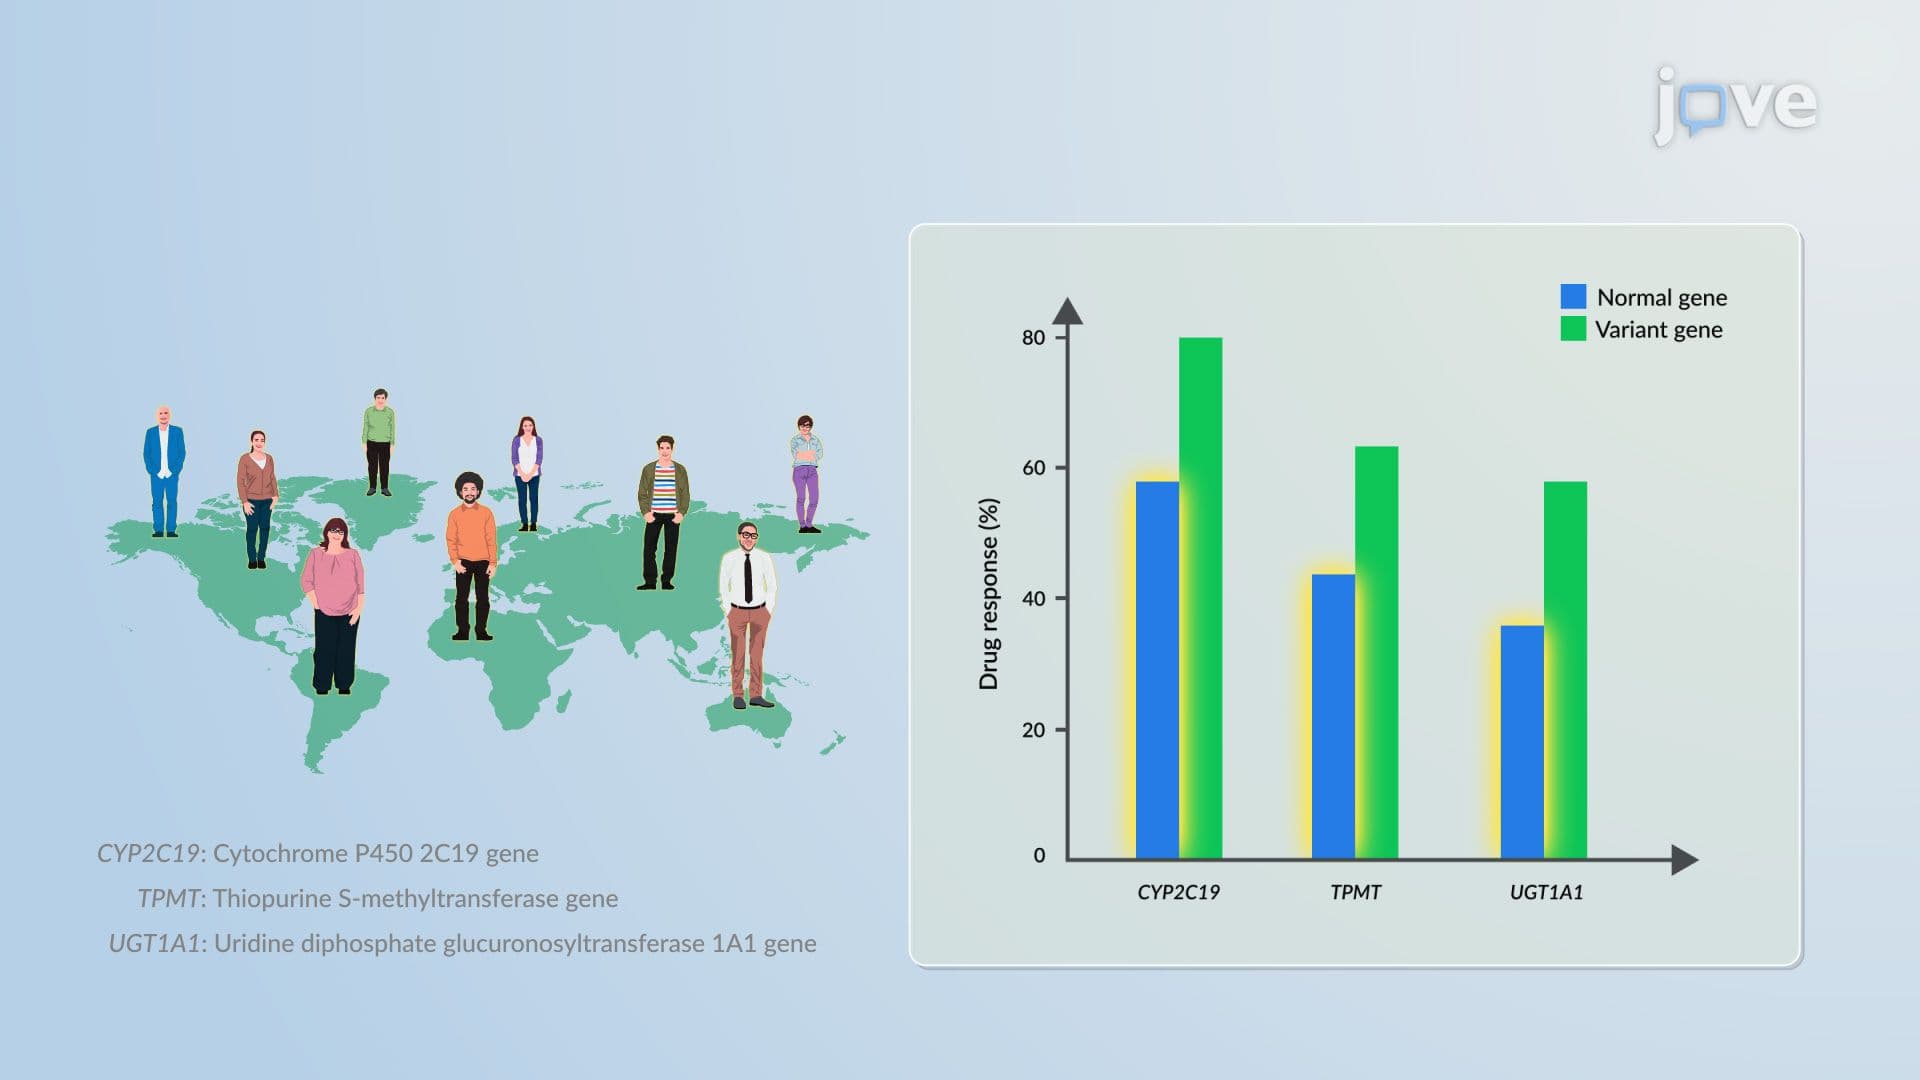
Pharmacogenetics and Pharmacogenomics: Overview
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu
 01:27
Principles of Pharmacogenetics: Types of Genetic Variants
 01:26
Drug Discovery: Overview
 01:27
Pharmacogenetics of Drug Metabolism: Overview