Related Experiment Video
Updated: Apr 6, 2026


High-Throughput Cellular Profiling of Targeted Protein Degradation Compounds Using HiBiT CRISPR Cell Lines
Published on: November 9, 2020
Clinical Pharmacokinetic and Pharmacodynamic Profile of Idelalisib
Srinivasan Ramanathan1, Feng Jin2, Shringi Sharma2
1Gilead Sciences, Inc., 333 Lakeside Drive, Foster City, CA, 94404, USA. sramanathan@gilead.com.

Idelalisib is a potent and selective phosphatidylinositol 3-kinase-δ inhibitor, which is a first-in-class agent to be approved for the treatment of relapsed chronic lymphocytic leukaemia, follicular B cell non-Hodgkin's lymphoma and small lymphocytic lymphoma. In dose-ranging studies, idelalisib exposure increased in a less than dose-proportional manner, likely because of solubility-limited absorption. The approved starting dose of 150 mg twice daily was supported by extensive exposure-response evaluations, with dose reduction to 100 mg twice daily being allowed for specific toxicities. Idelalisib may be administered without regard to food on the basis of the absence of clinically relevant food effects, and was accordingly dosed in primary efficacy/safety studies. Idelalisib is metabolized primarily via aldehyde oxidase (AO) and, to a lesser extent, via cytochrome P450 (CYP) 3A. Coadministration with the strong CYP3A inhibitor ketoconazole 400 mg once daily resulted in a ~79 % increase in the idelalisib area under the plasma concentration-time curve (AUC). Administration with the potent inducer rifampin resulted in a 75 % decrease in idelalisib exposure (AUC) and, as such, coadministration with strong inducers should be avoided. GS-563117 is an inactive primary circulating metabolite of idelalisib formed mainly via AO. Unlike idelalisib, GS-563117 is a mechanism-based inhibitor of CYP3A. Accordingly, idelalisib 150 mg twice-daily dosing increases the midazolam AUC 5.4-fold. Clinically, idelalisib is not an inhibitor of the transporters P-glycoprotein, breast cancer resistance protein, organic anion-transporting polypeptide (OATP) 1B1 or OAPT1B3. In a population pharmacokinetic model, no meaningful impact on idelalisib pharmacokinetics was noted for any of the covariates tested. Idelalisib exposure was ~60 % higher with moderate/severe hepatic impairment; no relevant changes were observed with severe renal impairment. This article reviews a comprehensive pharmacology programme, including drug-drug interaction studies and mechanistic and special population studies, which has allowed a thorough understanding of idelalisib clinical pharmacokinetics and their impact on clinical safety and efficacy.
Idelalisib is a potent and selective phosphatidylinositol 3-kinase-δ inhibitor, which is a first-in-class agent to be approved for the treatment of relapsed chronic lymphocytic leukaemia, follicular B cell non-Hodgkin's lymphoma and small lymphocytic lymphoma. In dose-ranging studies, idelalisib exposure increased in a less than dose-proportional manner, likely because of solubility-limited absorption. The approved starting dose of 150 mg twice daily was supported by extensive exposure-response evaluations, with dose reduction to 100 mg twice daily being allowed for specific toxicities. Idelalisib may be administered without regard to food on the basis of the absence of clinically relevant food effects, and was accordingly dosed in primary efficacy/safety studies. Idelalisib is metabolized primarily via aldehyde oxidase (AO) and, to a lesser extent, via cytochrome P450 (CYP) 3A. Coadministration with the strong CYP3A inhibitor ketoconazole 400 mg once daily resulted in a ~79 % increase in the idelalisib area under the plasma concentration-time curve (AUC). Administration with the potent inducer rifampin resulted in a 75 % decrease in idelalisib exposure (AUC) and, as such, coadministration with strong inducers should be avoided. GS-563117 is an inactive primary circulating metabolite of idelalisib formed mainly via AO. Unlike idelalisib, GS-563117 is a mechanism-based inhibitor of CYP3A. Accordingly, idelalisib 150 mg twice-daily dosing increases the midazolam AUC 5.4-fold. Clinically, idelalisib is not an inhibitor of the transporters P-glycoprotein, breast cancer resistance protein, organic anion-transporting polypeptide (OATP) 1B1 or OAPT1B3. In a population pharmacokinetic model, no meaningful impact on idelalisib pharmacokinetics was noted for any of the covariates tested. Idelalisib exposure was ~60 % higher with moderate/severe hepatic impairment; no relevant changes were observed with severe renal impairment. This article reviews a comprehensive pharmacology programme, including drug-drug interaction studies and mechanistic and special population studies, which has allowed a thorough understanding of idelalisib clinical pharmacokinetics and their impact on clinical safety and efficacy.

Related Concept Videos
 01:14
Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship
 01:24
Pharmacokinetic–Pharmacodynamic Relationship: Problems
 01:14
Pharmacokinetic–Pharmacodynamic Relationship: Model Components
 01:23
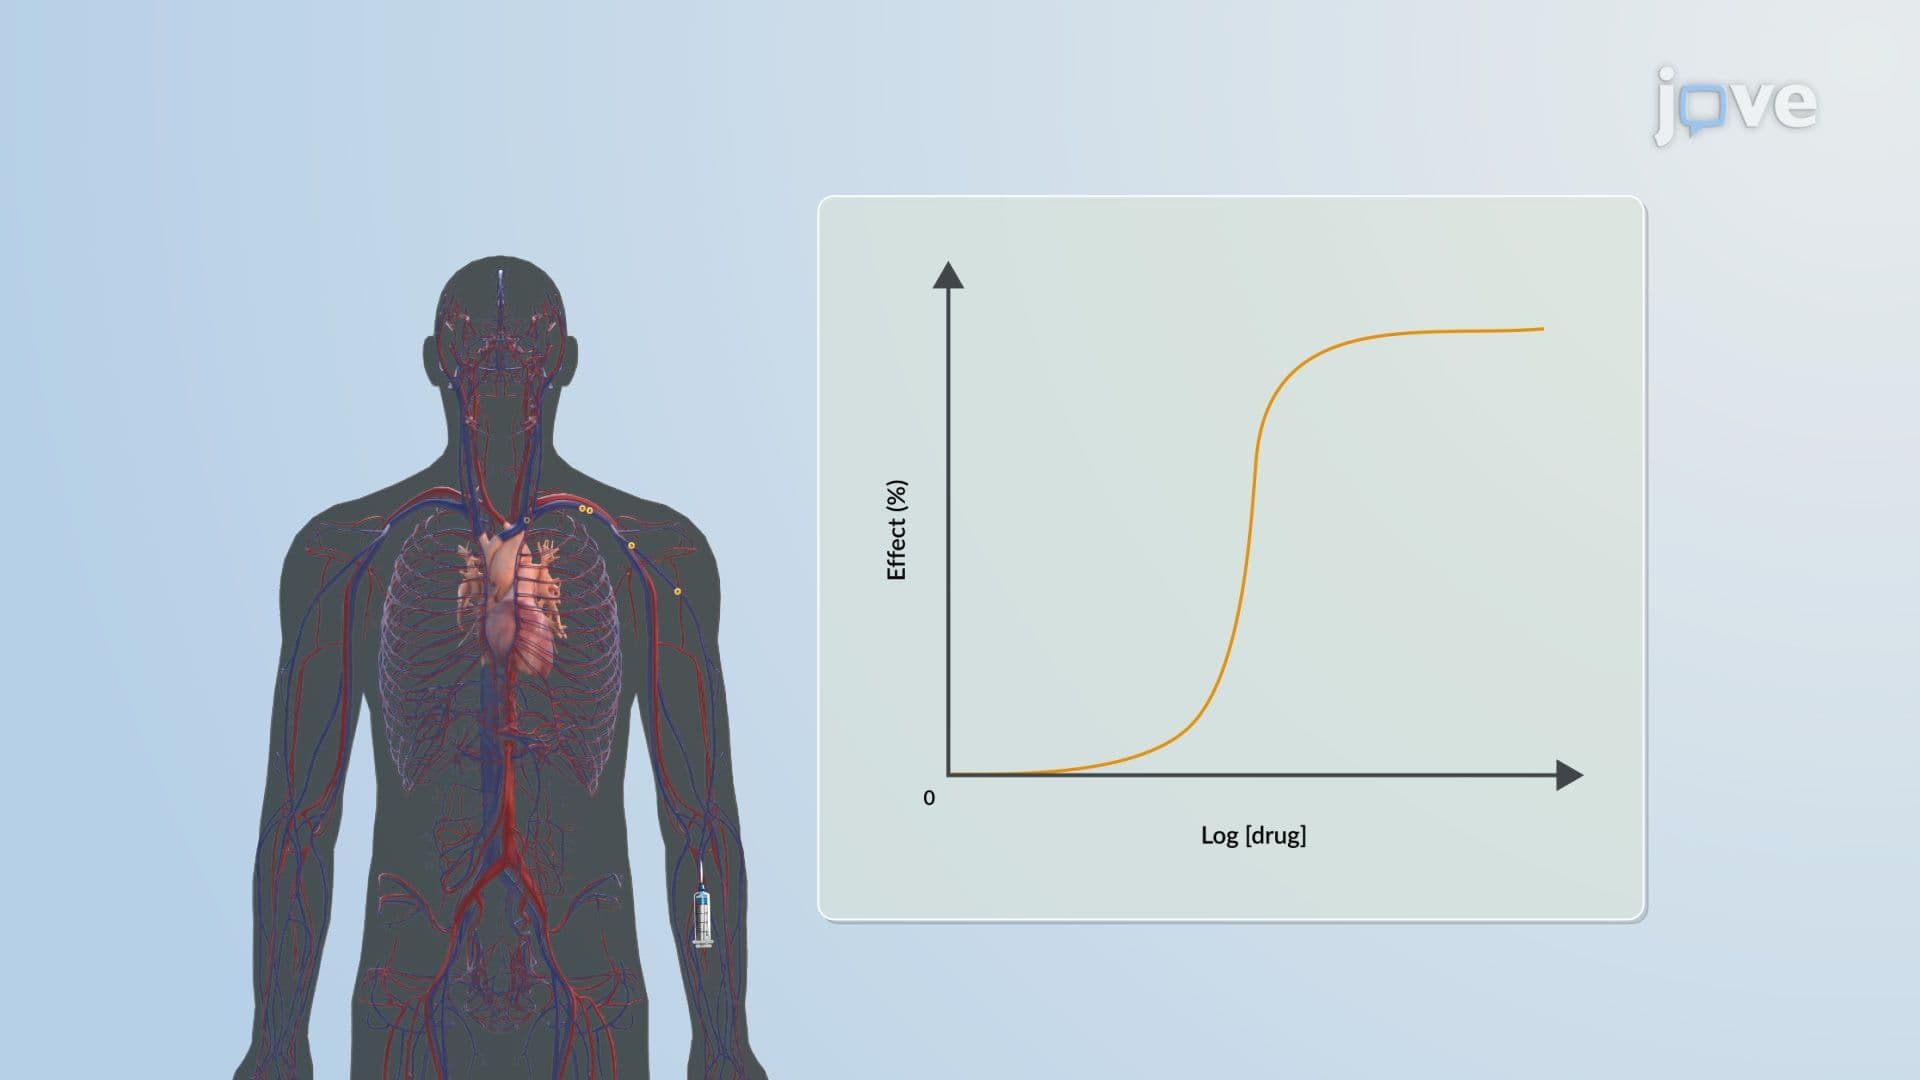
Pharmacokinetic–Pharmacodynamic Relationship: Intensity of Dose-Effect Relationship
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:26
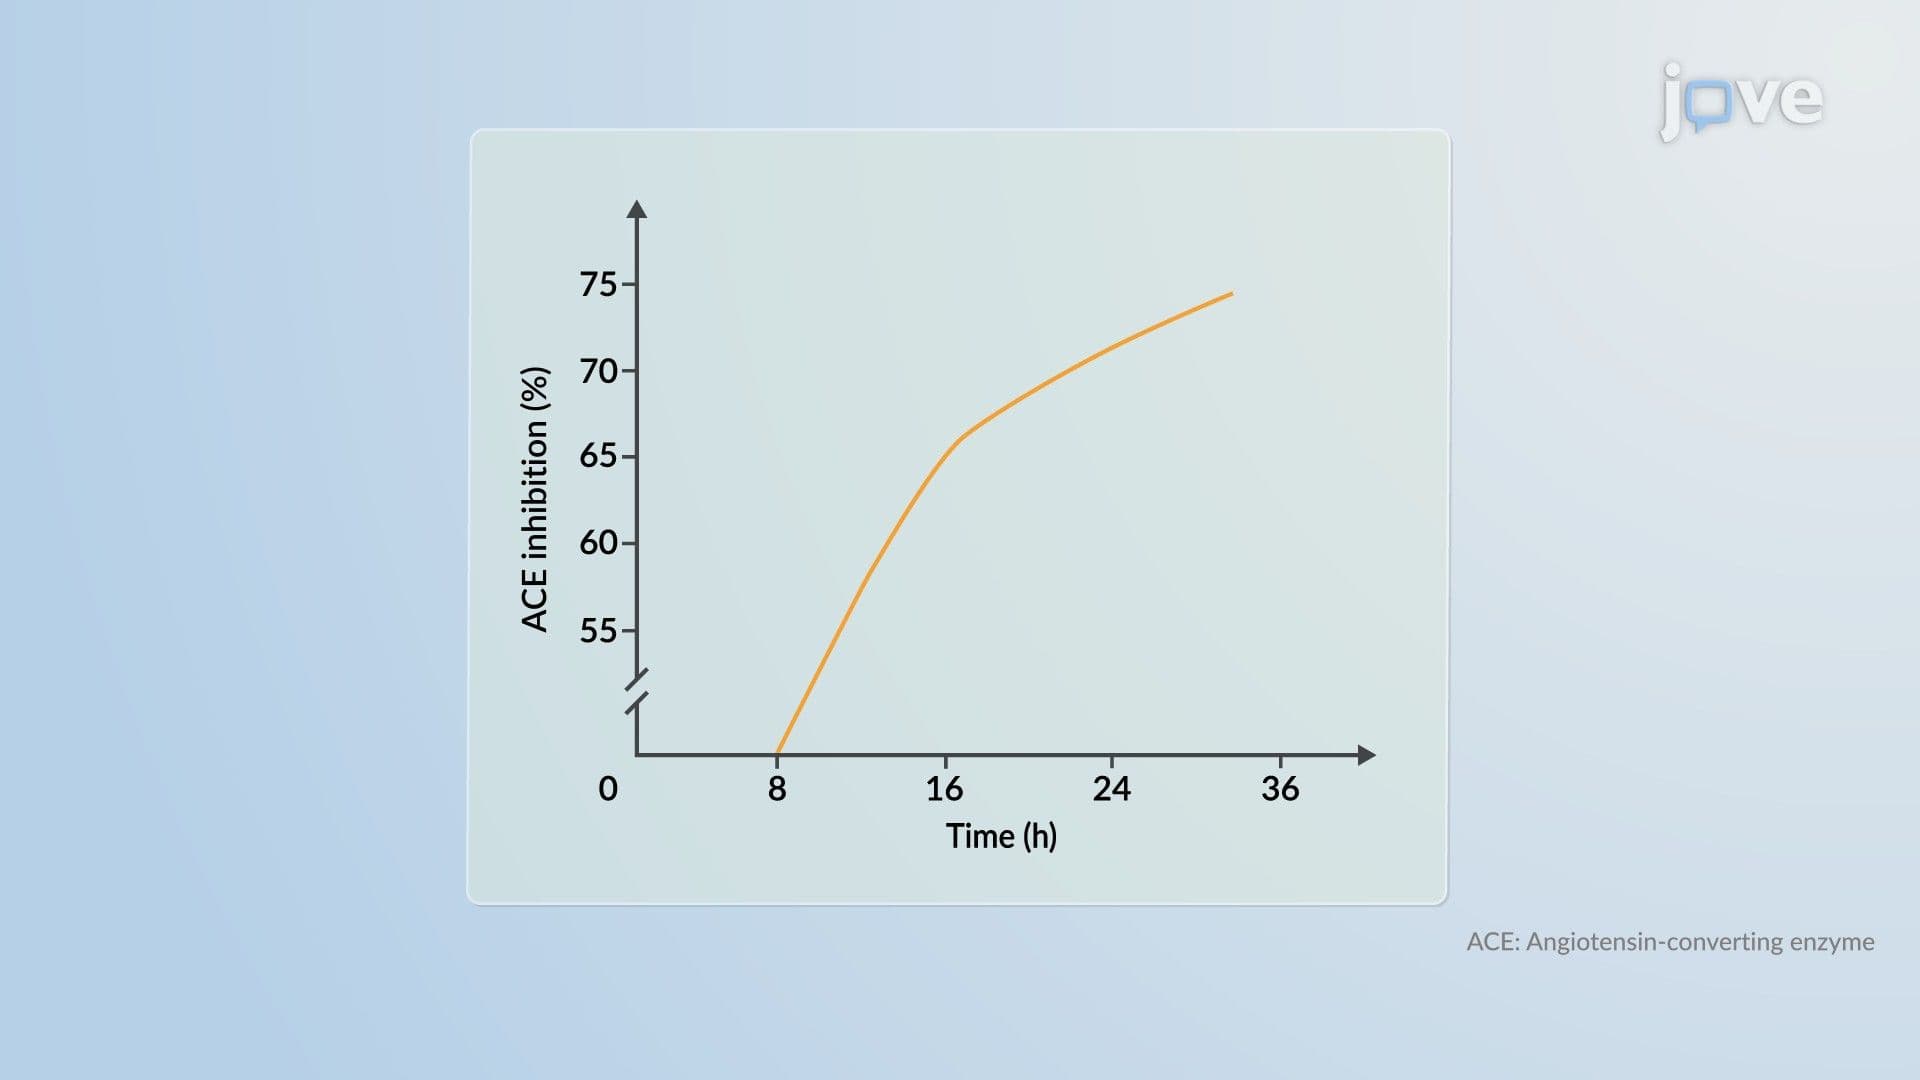
Pharmacokinetic–Pharmacodynamic Relationship: Exposure, Response and Effect