Related Experiment Video
Updated: Apr 6, 2026
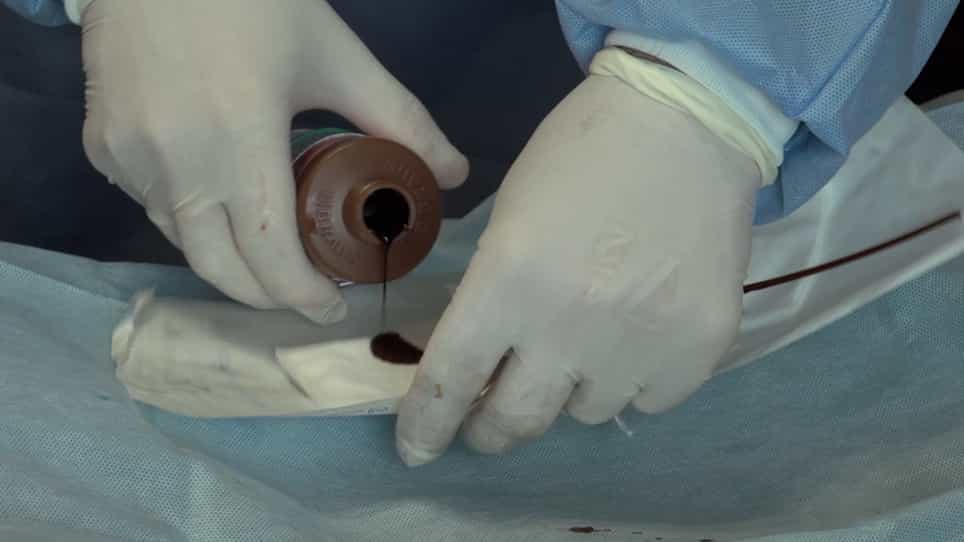

Application of Lucilia sericata Larvae in Debridement of Pressure Wounds in Outpatient Settings
Published on: December 4, 2021
Management of imported cutaneous larva migrans: A case series and mini-review
Leah Kincaid1, Michael Klowak2, Stefanie Klowak3
1Division of Dermatology, Department of Medicine, University of Toronto, Canada.

Background:
Cutaneous larva migrans (CLM), a zoonotic helminthiasis imported to Canada by travelers to the tropics, causes morbidity due to severe, intractable pruritus. Treatment in Canada is only available through the Special Access Program (SAP) of Health Canada, thus, many patients are prescribed ineffective courses of non-targeted therapy.
Objective:
We analyzed patients with CLM referred to our specialized Tropical Disease Unit (TDU) having failed non-targeted therapy prior to referral, and characterized demographic and travel related correlates of CLM.
Methods:
Patients with CLM evaluated between June 2012 and December 2014 were identified through our SAP application log, and charts were reviewed for demographic, clinical, and travel-related data following IRB approval.
Results:
25 patients with CLM were identified: 12 women, and 13 men. Median age was 35 years (range 4-58 years). Patients had primarily acquired their CLM in the Caribbean (80%), with Jamaica being the most well represented source destination (N = 10, 40%). Reported symptoms included intense, function-limiting pruritus (N = 25, 100%) and loss of sleep (N = 3, 12%). Twelve patients (48%) with CLM had received at least 1 course of non-targeted therapy prior to referral. Non-targeted therapies included topical steroids (N = 7), cryotherapy (N = 3), oral antibiotics (N = 2), and oral mebendazole (N = 11). Median duration of symptoms was 34 days (range 5-226 days). Of 25 patients with CLM, 23 (92%) were prescribed a single 3-day course of albendazole and responded appropriately, and 2 (8%) required a second 3-day course of albendazole.
Conclusions:
Although CLM is non-communicable and of little public health relevance in Canada, it causes significant morbidity. A substantial proportion of patients with CLM referred to our specialized TDU had a prolonged course of illness and were prescribed ineffective and non-targeted therapies. Oral albendazole or ivermectin, or topical thiabendazole, are the drugs of choice for CLM, and should be prescribed as first-line therapy.
More Related Videos
 11:36
Cutaneous Leishmaniasis in the Dorsal Skin of Hamsters: a Useful Model for the Screening of Antileishmanial Drugs
Published on: April 21, 2012
 12:14
Exploring Life History Choices: Using Temperature and Substrate Type as Interacting Factors for Blowfly Larval and Female Preferences
Published on: November 17, 2023
