Related Experiment Video
Updated: Apr 5, 2026

DUCT: Double Resin Casting followed by Micro-Computed Tomography for 3D Liver Analysis
Published on: September 28, 2021
Anatomic variability of the thoracic duct in pediatric patients with complex congenital heart disease
Ji Hyun Bang1, Sang Hwa Kim1, Chun Soo Park1
1Division of Pediatric Cardiac Surgery, Asan Medical Center, University of Ulsan College of Medicine, Seoul, Republic of Korea.

Objective:
Thoracic duct mass ligation (TDML) through a right thoracotomy (RT), regardless of the side of the pleural effusion, is a standard procedure for chylothorax that is refractory to medical treatment. This procedure may be unsuccessful in patients with complex congenital heart disease, which necessitates additional left thoracotomy (LT) for left periaortic mass ligation. We hypothesized that failure of the right-sided approach is attributable to the anatomic variation of the path of the thoracic duct.
Methods:
Of the children who underwent surgery for congenital heart disease between 1992 and 2014, a total of 70 of 8880 (0.8%) underwent TDML by RT (n = 57) or LT (n = 13; LT after RT in 10, and primary LT in 3).
Results:
Persistent chylothorax was successfully resolved in 65 patients (65 of 70; 93%) within 15 days (2-79 days) after the first or second TDML; 5 patients died with a chest-tube(s) in situ. After excluding mortality without chest-tube removal, we sought to identify the risk factor(s) necessitating LT in 65 patients (RT group: 54; LT group: 11). On logistic regression analysis, the LT group was more likely to have dextrocardia (odds ratio: 6.38; 95% confidence interval: 1.09-37.25; P = .04). The incidence of abnormal atrial situs, great arterial malposition, right descending thoracic aorta, and bilateral superior vena cavae were comparable in the 2 groups.
Conclusions:
The path of the thoracic duct may vary in pediatric patients with complex congenital heart disease. Left periaortic mass ligation should be considered in patients with chylothoraces that persist after the right-sided approach, especially in patients with dextrocardia.
More Related Videos
 09:31
Hemodynamic Precision in the Neonatal Intensive Care Unit using Targeted Neonatal Echocardiography
Published on: January 27, 2023
 06:02
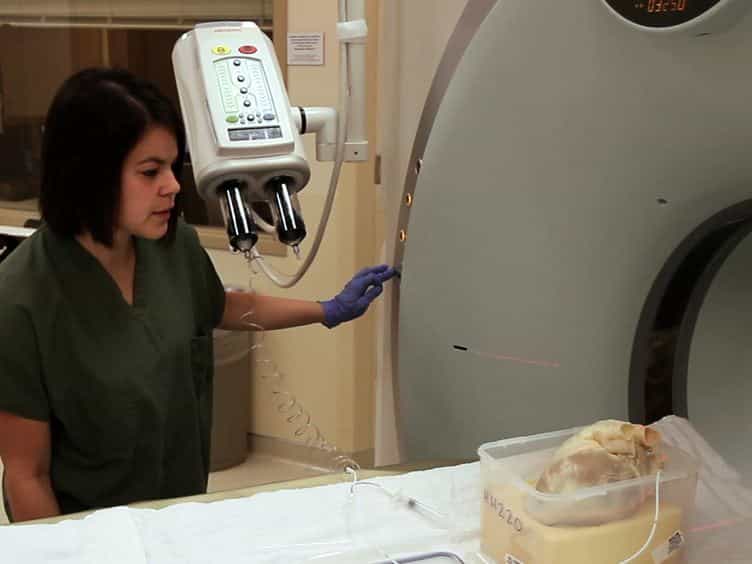
Anatomical Reconstructions of the Human Cardiac Venous System using Contrast-computed Tomography of Perfusion-fixed Specimens
Published on: April 18, 2013
Related Concept Videos
 01:16
Lymphatic Vessels and Lymph Transport
This one-way system allows fluids, solutes, and even pathogens to enter but prevents their return to the intercellular...
 01:15
Development of the Lymphatic System
The first lymph sacs to form are the paired jugular lymph sacs located at the junction of the internal jugular and subclavian veins. From these sacs, lymphatic capillary plexuses extend to the thorax, upper limbs, neck, and head, eventually forming lymphatic vessels. Each jugular lymph sac maintains a...
 01:19
Veins of Thorax
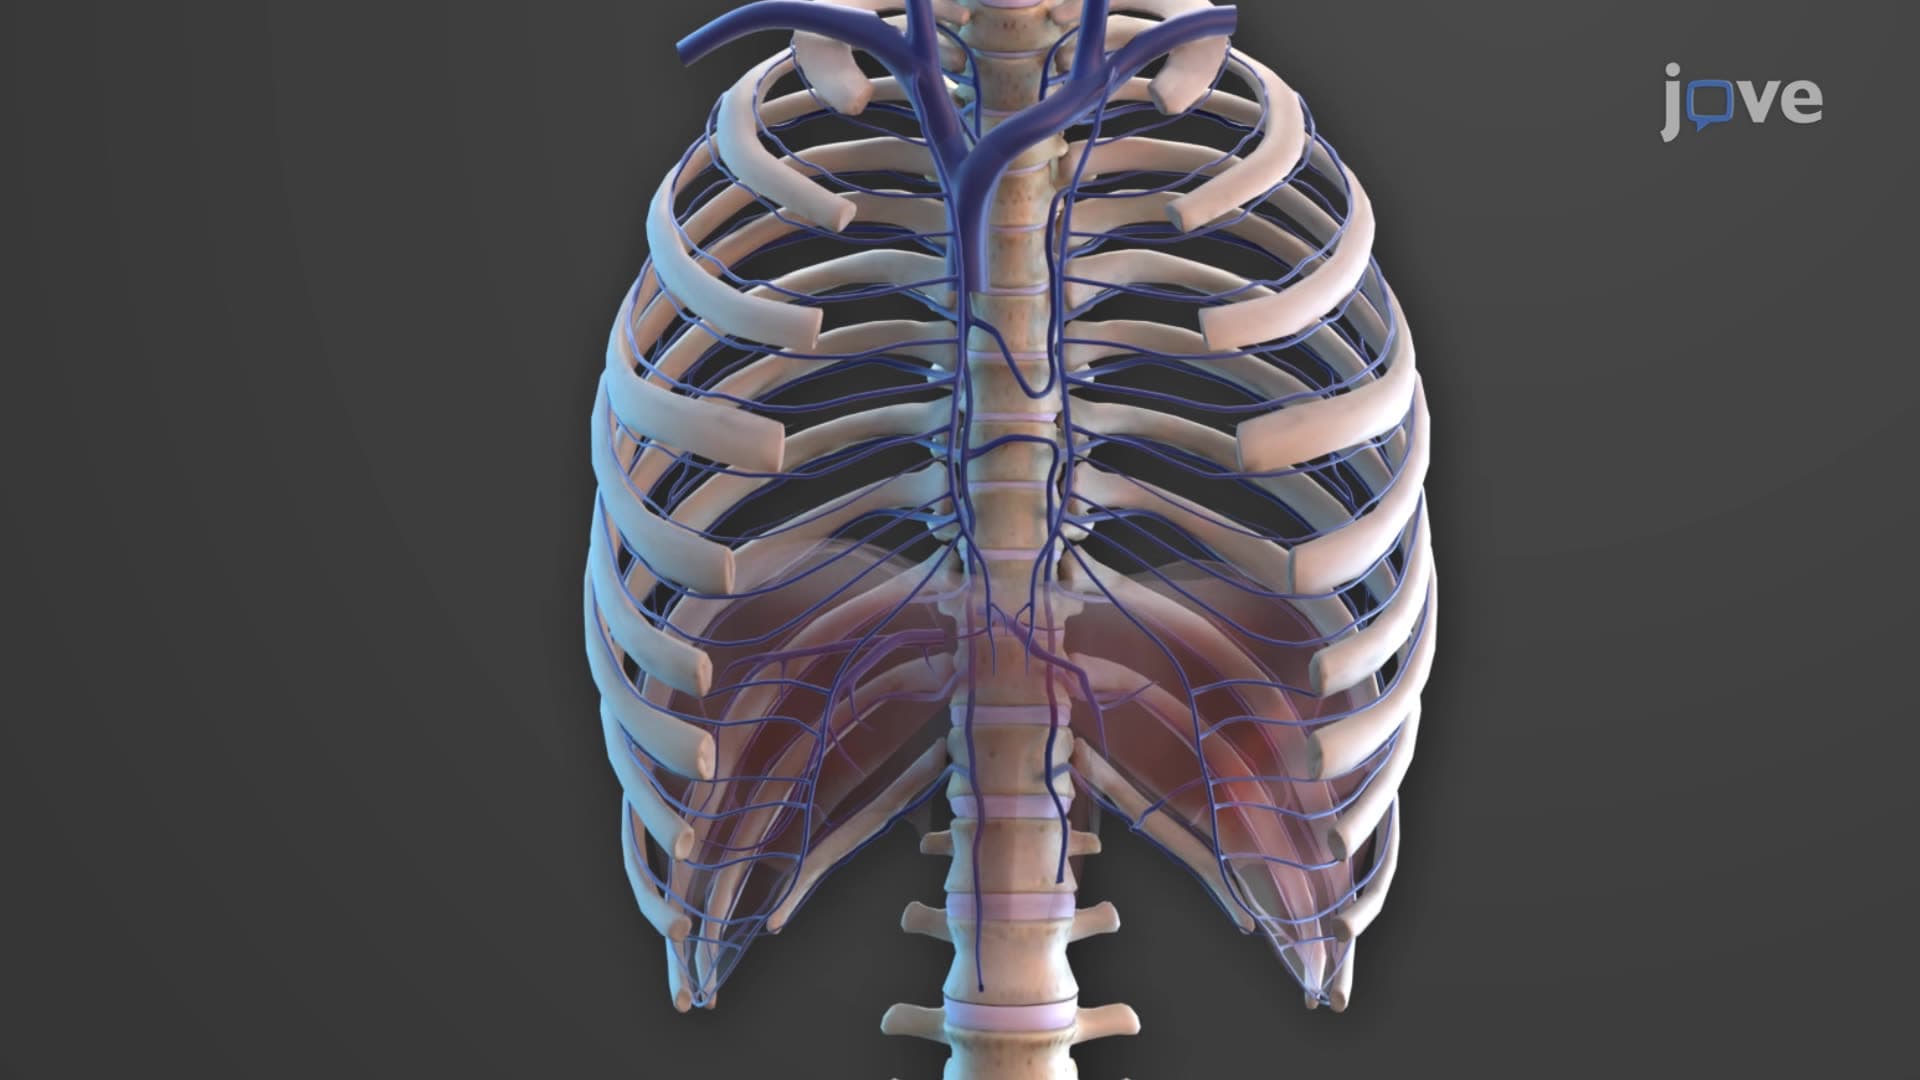
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 02:03
Anatomy of the Circulatory System
 01:15
Thoracic Aorta