
Relationships between craniocervical posture and pain-related disability in patients with cervico-craniofacial pain
Ibai López-de-Uralde-Villanueva1, Hector Beltran-Alacreu2, Alba Paris-Alemany1
1Department of Physiotherapy, Faculty of Health Science, The Center for Advanced Studies University La Salle, Universidad Autónoma de Madrid, Aravaca, Madrid, Spain ; Research Group on Movement and Behavioral Science and Study of Pain, The Center for Advanced Studies University La Salle, Universidad Autónoma de Madrid, Aravaca, Madrid, Spain ; Institute of Neuroscience and Craniofacial Pain (INDCRAN), Madrid, Spain ; Hospital La Paz Institute for Health Research, IdiPAZ, Madrid, Spain.

Objectives:
This cross-sectional correlation study explored the relationships between craniocervical posture and pain-related disability in patients with chronic cervico-craniofacial pain (CCFP). Moreover, we investigated the test-retest intrarater reliability of two craniocervical posture measurements: head posture (HP) and the sternomental distance (SMD).
Methods:
Fifty-three asymptomatic subjects and 60 CCFP patients were recruited. One rater measured HP and the SMD using a cervical range of motion device and a digital caliper, respectively. The Spanish versions of the neck disability index and the craniofacial pain and disability inventory were used to assess pain-related disability (neck disability and craniofacial disability, respectively).
Results:
We found no statistically significant correlations between craniocervical posture and pain-related disability variables (HP and neck disability [r=0.105; P>0.05]; HP and craniofacial disability [r=0.132; P>0.05]; SMD and neck disability [r=0.126; P>0.05]; SMD and craniofacial disability [r=0.195; P>0.05]). A moderate positive correlation was observed between HP and SMD for both groups (asymptomatic subjects, r=0.447; CCFP patients, r=0.52). Neck disability was strongly positively correlated with craniofacial disability (r=0.79; P<0.001). The test-retest intrarater reliability of the HP measurement was high for asymptomatic subjects and CCFP patients (intraclass correlation coefficients =0.93 and 0.81, respectively) and for SMD (intra-class correlation coefficient range between 0.76 and 0.99); the test-retest intrarater reliability remained high when evaluated 9 days later. The HP standard error of measurement range was 0.54-0.75 cm, and the minimal detectable change was 1.27-1.74 cm. The SMD standard error of measurement was 2.75-6.24 mm, and the minimal detectable change was 6.42-14.55 mm. Independent t-tests showed statistically significant differences between the asymptomatic individuals and CCFP patients for measures of craniocervical posture, but these differences were very small (mean difference =1.44 cm for HP; 6.24 mm for SMD). The effect sizes reached by these values were estimated to be small for SMD (d=0.38) and medium for HP (d=0.76).
Conclusion:
The results showed no statistically significant correlations between craniocervical posture and variables of pain-related disability, but a strong correlation between the two variables of disability was found. Our findings suggest that small differences between CCFP patients and asymptomatic subjects exist with respect to the two measurements used to assess craniocervical posture (HP and SMD), and these measures demonstrated high test-retest intrarater reliability for both CCFP patients and asymptomatic subjects.


Related Concept Videos
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
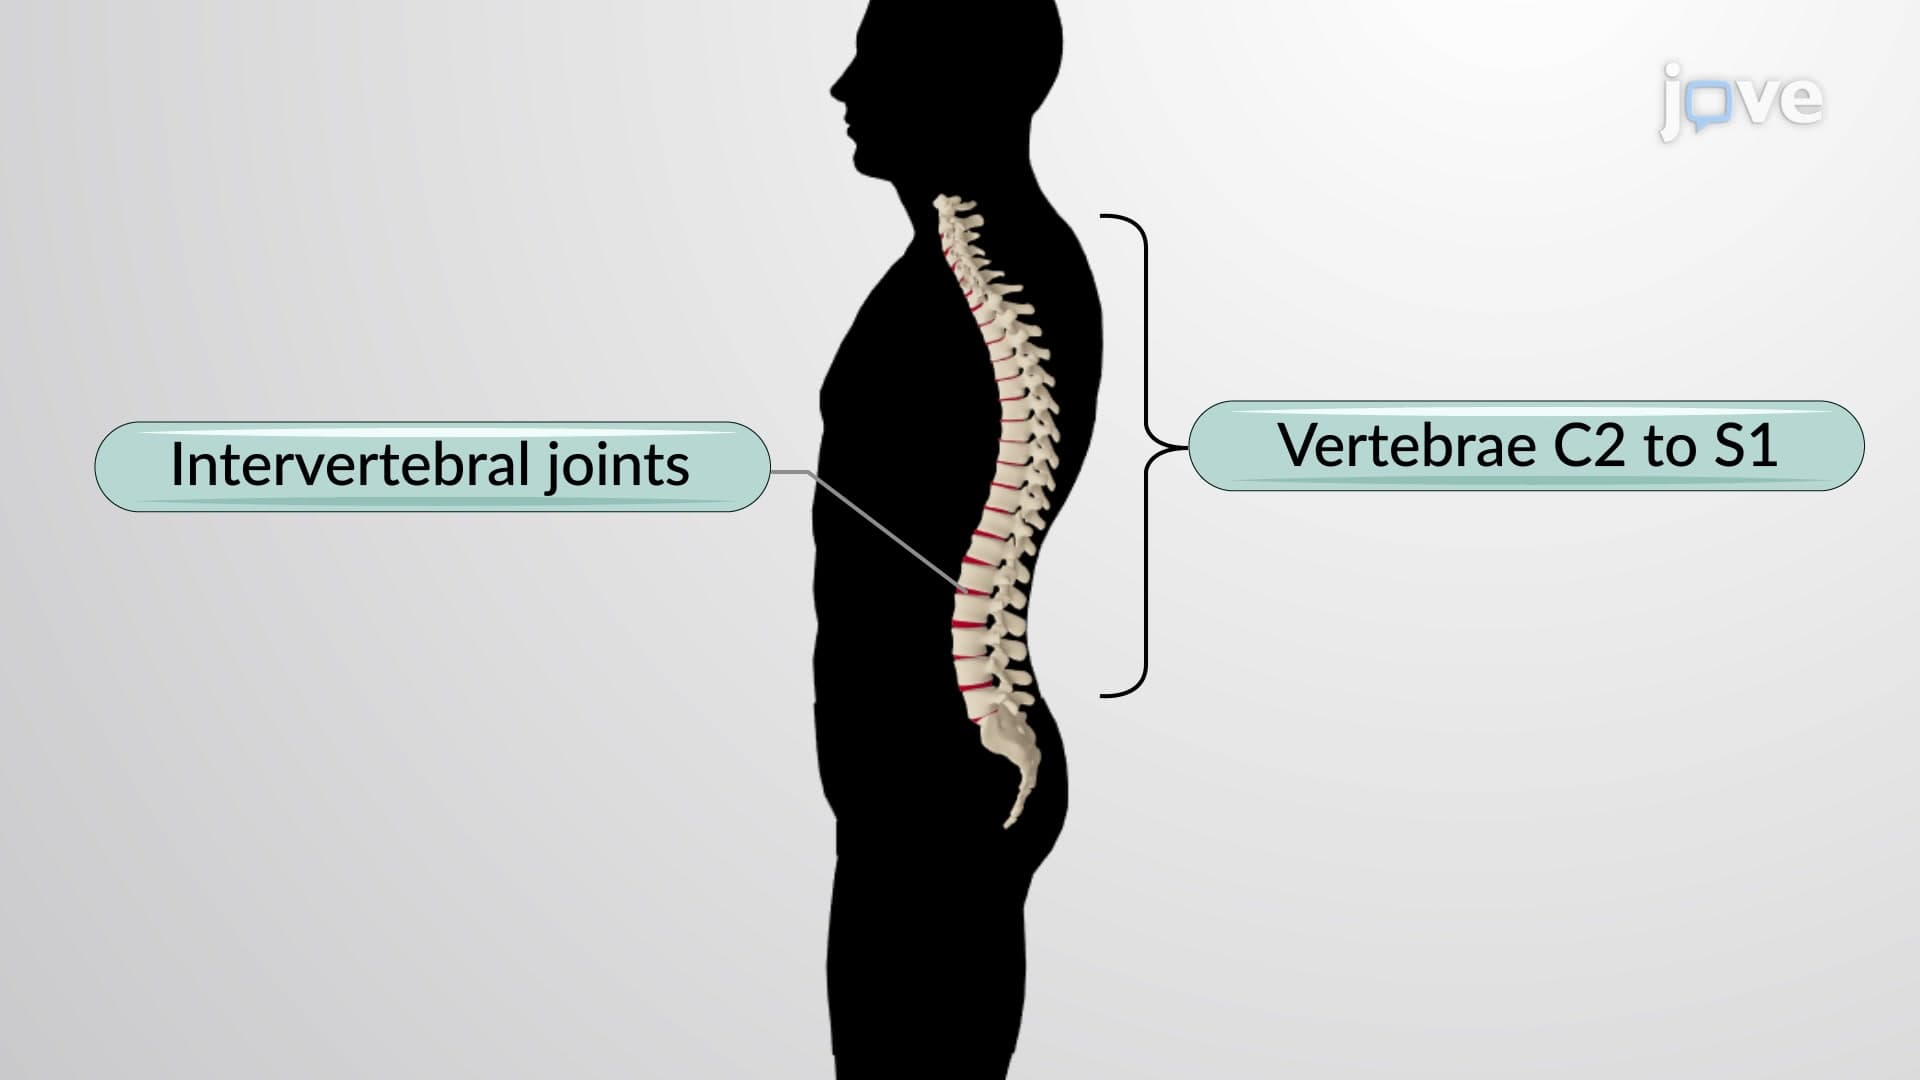 01:28
Articulations of the Vertebral Column
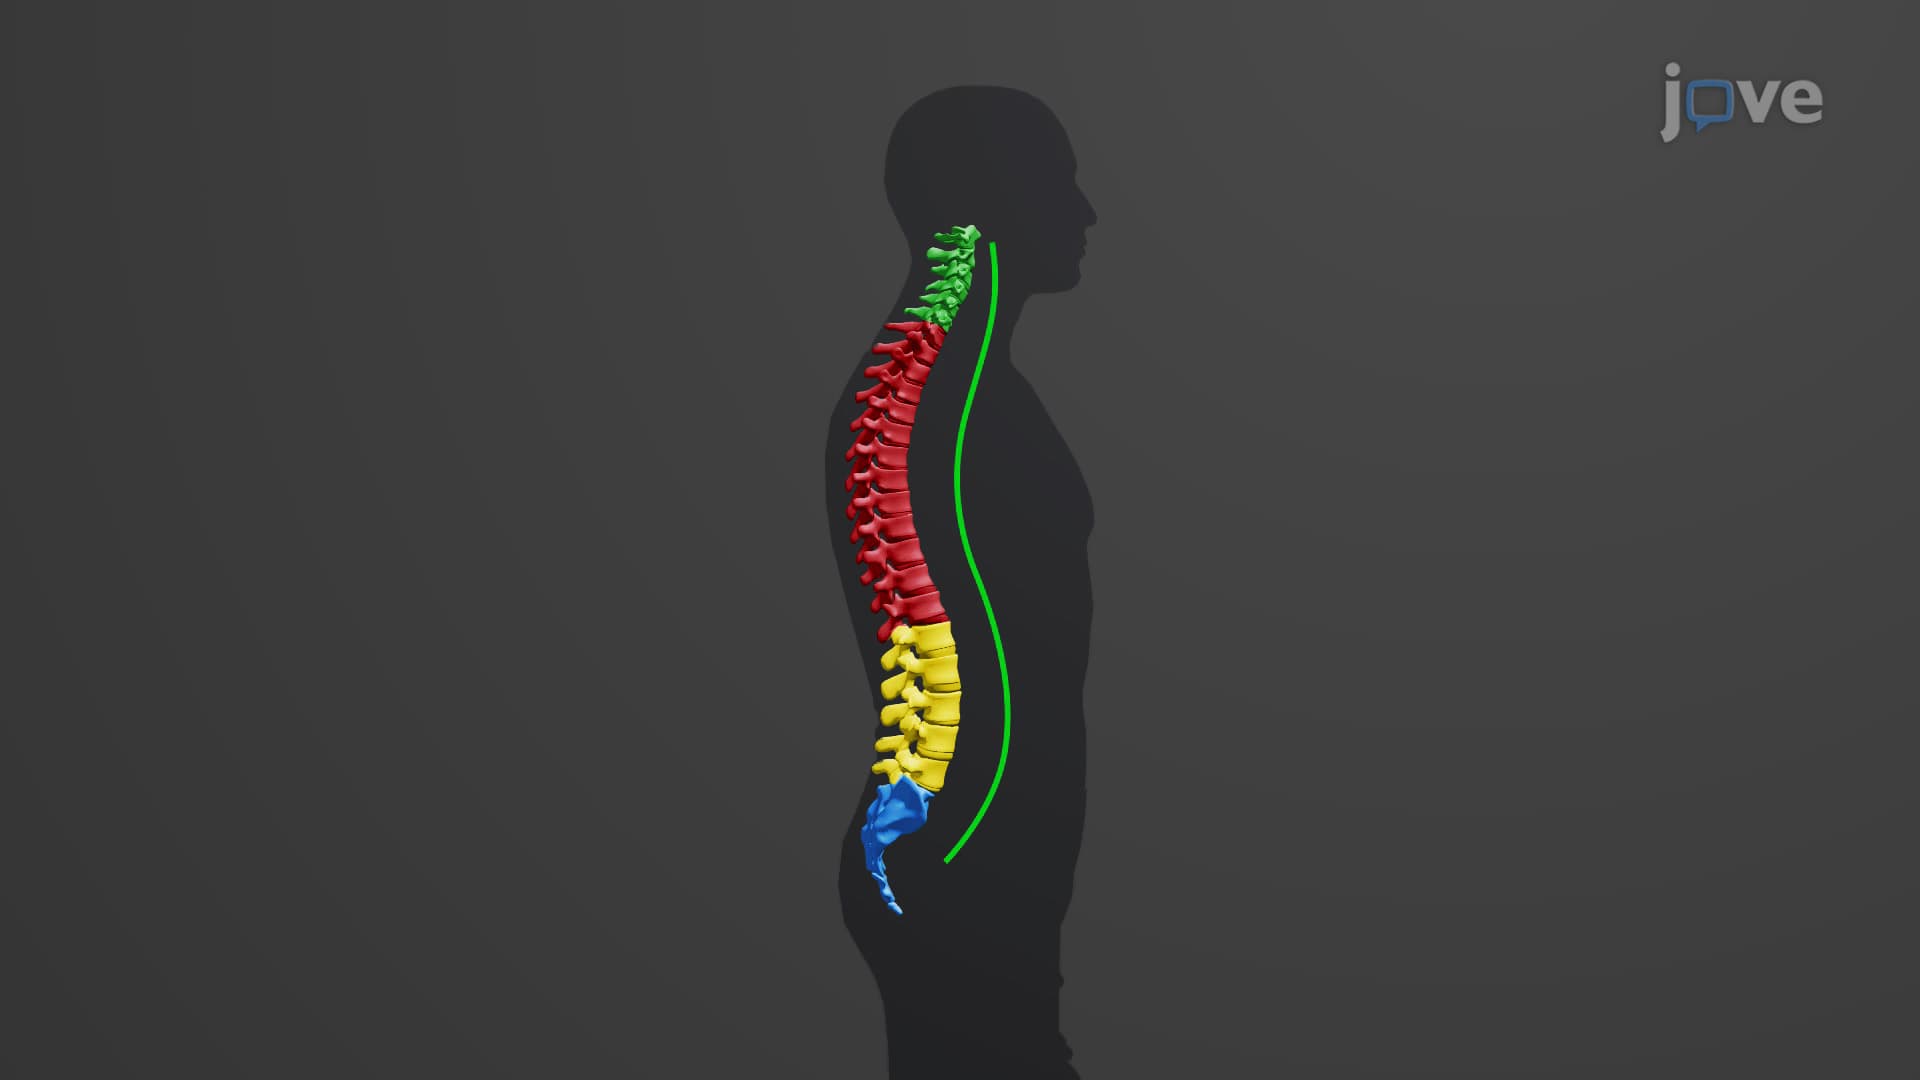 01:16
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...