Related Experiment Video
Updated: Apr 5, 2026
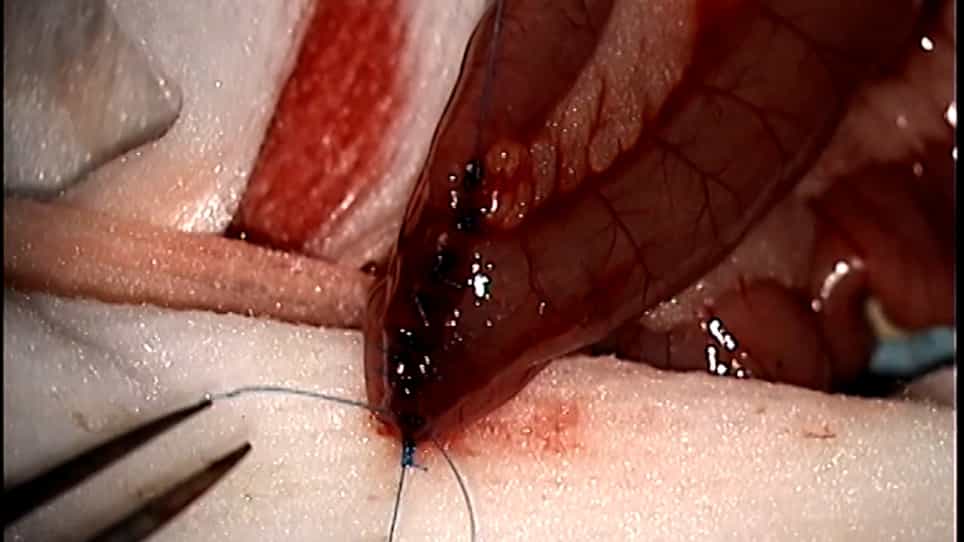

A Protocol for Roux-en-Y Gastric Bypass in Rats using Linear Staplers
Published on: August 21, 2021
Readmissions Following Gastric Bypass Surgery
Susie X Sun1, Christopher S Hollenbeak2,3, Ann M Rogers4
1Department of Surgery, College of Medicine, The Pennsylvania State University, 500 University Drive, H149, Hershey, PA, 17033-0850, USA. ssun1@hmc.psu.edu.

Insights
Preventing readmissions after gastric bypass (GB) is crucial. Factors like race, open surgery, and comorbidities increase readmission risk, suggesting targeted interventions can improve outcomes and reduce length of stay (LOS).
Area of Science:
- Bariatric surgery outcomes
- Healthcare quality improvement
- Patient safety in surgical procedures
Background:
- Growing emphasis on preventing patient readmissions due to evolving reimbursement models.
- Identification of factors contributing to 30-day readmissions post-gastric bypass (GB) is essential for improving care quality.
Purpose of the Study:
- To assess factors contributing to 30-day readmission after elective gastric bypass (GB).
- To determine the preventability of these readmissions.
- To analyze the impact on length of stay (LOS).
Main Methods:
- Utilized data from the Pennsylvania Health Care Cost Containment Council (PHC4) for elective GB patients in 2011 (n=4427).
- Analyzed outcomes including length of stay (LOS) and 30-day readmission rates.
- Employed univariate comparisons and multivariate logistic/linear regression models to identify predictors.
Main Results:
- Readmission occurred in 6.6% of patients, with bleeding, infection, and abdominal pain as primary causes.
- Black race, open GB, and history of myocardial infarction or rheumatoid arthritis were associated with higher readmission odds.
- Longer LOS predicted readmission; older age and comorbidities like congestive heart failure, peripheral vascular, and kidney diseases were linked to longer LOS.
Conclusions:
- Bleeding, infection, and abdominal pain are the most frequent causes of readmission after elective GB.
- Patient-specific factors are significantly associated with increased readmission risk and prolonged LOS.
- Opportunities exist for targeted interventions to prevent readmissions and reduce LOS in GB patients.
Background:
Interest is growing in preventing readmissions as payers start to link reimbursement to readmission rates. The purpose of this study was to assess factors contributing to 30-day readmission for patients undergoing gastric bypass (GB) and determine whether these readmissions may be preventable.
Methods:
Data were from the Pennsylvania Health Care Cost Containment Council (PHC4) and included all patients undergoing elective GB for obesity in 2011 (n = 4427). The outcomes measured were length of stay (LOS) and 30-day readmission. Univariate comparisons between characteristics of readmitted (n = 298) and non-readmitted (n = 4133) patients were performed. Readmission was modeled using multivariate logistic regression; LOS was modeled using linear regression.
Results:
Of the 298 (6.6%) patients who were readmitted, the most common causes for readmission were bleeding (11.84%), infection (8.88%), and abdominal pain (7.89%). In multivariate analyses, black race, open GB, and history of myocardial infarction or rheumatoid arthritis were associated with increased odds of readmission. Longer LOS was also predictive of readmission (OR 1.10, p = <0.0001). Patients who were >50 years old and those with history of congestive heart failure, peripheral vascular, and kidney diseases were more likely to have longer LOS. Black race, open surgery, and discharge to an extended care facility were also predictive of prolonged LOS.
Conclusions:
The most common causes of readmission following elective GB were bleeding, infection, and abdominal pain. Since several patient-specific factors were associated with higher odds of readmission and longer LOS, there are opportunities to design interventions to prevent readmissions and decrease LOS in this patient population.


Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to: