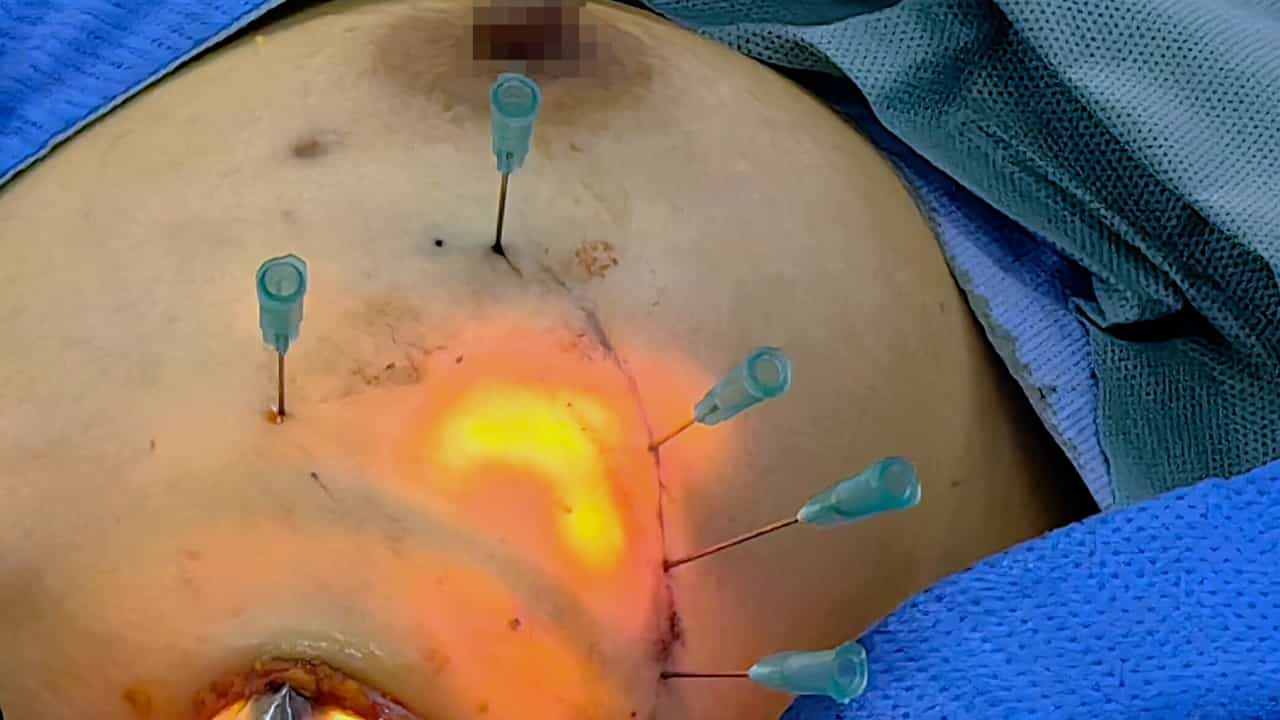
Related Experiment Video
Updated: Apr 5, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Extraperitoneal Para-aortic Lymphadenectomy by Robot-Assisted Laparoscopy in Gynecologic Oncology: Preliminary
Fabrice Narducci1, Eric Lambaudie, Daniele Mautone
1*Gynecologic Oncology Department, Centre Oscar Lambret Cancer Center, Lille, France; †Oncologic Surgery Department, Institut Paoli Calmettes Cancer Center, Marseille, France; and ‡Oncologic Surgery Department, Centre Georges-François Leclerc Cancer Center, Dijon, France.

Background:
We are reporting the preliminary multicentric experience in extraperitoneal para-aortic lymphadenectomy by robot-assisted laparoscopy (EPLRL) in gynecologic oncology.
Materials And Methods:
Two teams from the cancer centers performed EPLRL in 37 patients with gynecologic cancer.
Results:
There were 30 patients with cervical cancer, 6 with endometrial cancer, and 1 with adnexal cancer. The skin-to-skin operative time, mean lymph node count, and estimated blood loss were 221 (±61) minutes, 18.7 (±11), and 105 (±134) mL.There was no conversion to laparotomy, one laparoscopic conversion for hemorrhage lateral to the inferior mesenteric artery, and one use of hemostatic matrix for an injury to the left gonadal artery (2 nontransfused patients). The proportion of patients who reported postoperative complications was 32.5% (12/37): 7 with lymphocysts with computed tomographic scan drainage (19%), 3 with leg dysesthesia (left genitofemoral nerve), 1 with leg lymphedema, and 1 with lateral aortic hematoma not requiring a transfusion or return to the operating room.
Conclusion:
The EPLRL technique is feasible and efficient but with a high rate of symptomatic lymphocyst. A marsupialization could be useful to decrease the risk of lymphocyst.