Related Experiment Video
Updated: Apr 5, 2026
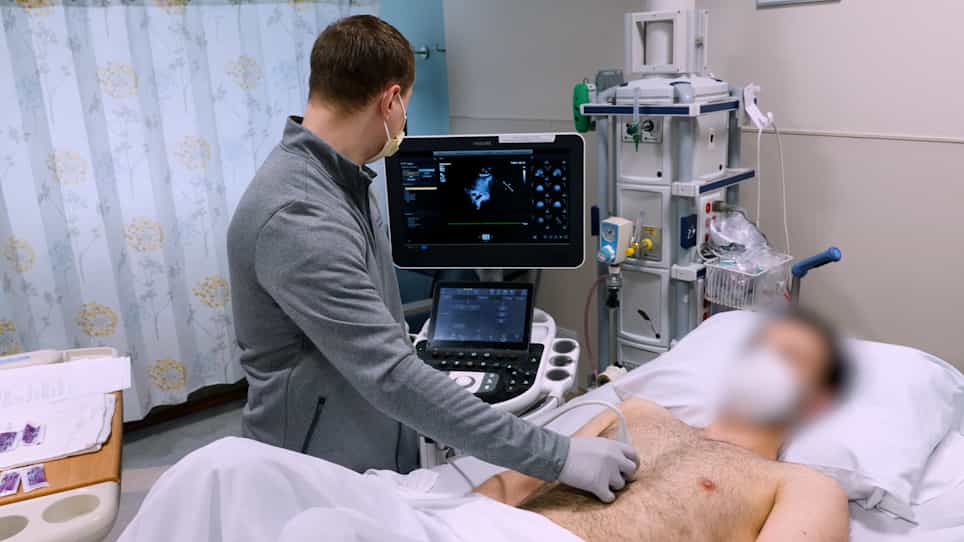

Image Acquisition Method for the Sonographic Assessment of the Inferior Vena Cava
Published on: January 13, 2023
Impact of Body Size on Inferior Vena Cava Parameters for Estimating Right Atrial Pressure: A Need for
Tatsunori Taniguchi1, Tomohito Ohtani1, Satoshi Nakatani1
1Department of Cardiovascular Medicine, Osaka University Graduate School of Medicine, Suita, Japan.

Background:
Inferior vena cava (IVC) diameter and its respiratory change, as determined using echocardiography, are commonly used to assess right atrial pressure (RAP). Despite the widespread use of the IVC approach for RAP assessment, the relations among body surface area (BSA), IVC diameter, and respirophasic change remain unclear. The aim of this study was to investigate the impact of BSA on IVC parameters for predicting elevated RAP.
Methods:
Ninety consecutive patients undergoing right-heart catheterization or central venous catheter insertion were prospectively included. To investigate the impact of BSA on IVC parameters, patients were divided into higher and lower BSA groups by comparing individual BSA measurements with the median value. Optimal cutoff points of IVC parameters for detecting RAP of ≥ 10 mm Hg were defined using receiver operating characteristic curves.
Results:
The median RAP and BSA were 8 mm Hg (range, 1-25 mm Hg) and 1.61 m(2) (range, 1.23-2.22 m(2)), respectively. In all patients, the optimal cutoff point for maximal IVC diameter (IVCDmax) and IVC collapsibility for the detection of RAP ≥ 10 mm Hg were 20 mm and 49.0%, respectively. The optimal cutoff point of IVCDmax for predicting RAP of ≥ 10 mm Hg was significantly larger in patients with higher BSAs than in those with lower BSAs (21 vs 17 mm, P = .0342). No differences in collapsibility indices were detected between the two groups. IVCDmax was larger in men (19 ± 5 vs 17 ± 5 mm in women, P = .0347) and weakly correlated with BSA (r = 0.35, P = .0007), whereas no relation was found between IVCDmax and age. However, the partial correlation coefficient of the entire cohort demonstrated that only BSA was still associated with IVCDmax after adjusting for age and gender (partial correlation coefficient = 0.32, P = .0020).
Conclusions:
Body size, measured as BSA, is important to consider when IVC diameter is used to assess RAP. The optimal cutoff point of IVCDmax was 21 mm for patients with larger BSAs and 17 mm for those with smaller BSAs. However, the cutoff point of IVC collapsibility was not influenced by the difference of BSA.

Related Concept Videos
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the...
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...