Related Experiment Video
Updated: Apr 5, 2026
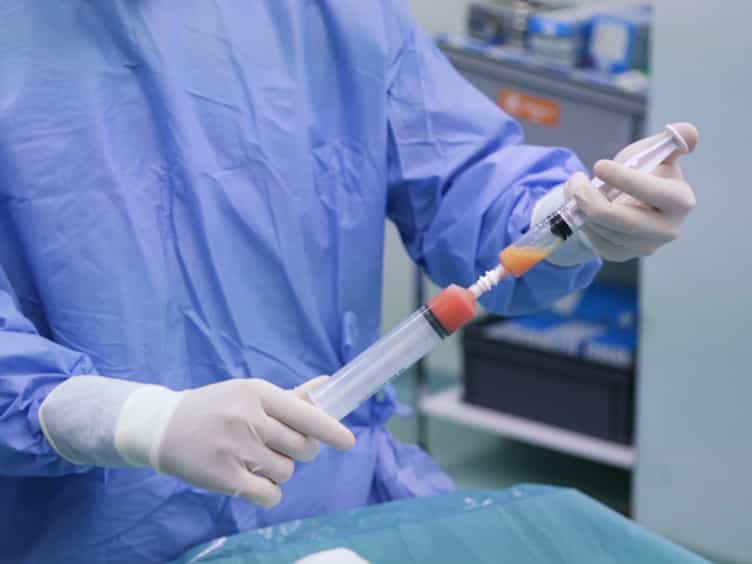

Autologous Microfractured and Purified Adipose Tissue for Arthroscopic Management of Osteochondral Lesions of the Talus
Published on: January 23, 2018
Radiographic identification of the primary structures of the ankle syndesmosis
Brady T Williams1, Evan W James1, Kyle A Jisa1
1Department of BioMedical Engineering, Steadman Philippon Research Institute, Vail, CO, USA.

Purpose:
The purpose of this study was to quantitatively describe the locations of the syndesmotic ligaments and the tibiofibular articulating cartilage surfaces on standard radiographic views using reproducible radiographic landmarks and reference axes.
Methods:
Twelve non-paired ankles were dissected to identify the anterior-inferior tibiofibular ligament (AITFL), posterior-inferior tibiofibular ligament (PITFL), interosseous tibiofibular ligament (ITFL), and the cartilage surfaces of the syndesmosis. Structures were marked with 2-mm radiopaque spheres prior to obtaining lateral and mortise radiographs. Measurements were performed by two independent raters to assess intra- and interobserver reliability via intraclass correlation coefficients (ICCs).
Results:
Measurements demonstrated excellent agreement between observers and across trials (all ICCs ≥ 0.960). On the lateral view, the AITFL tibial origin was 9.6 ± 1.5 mm superior and posterior to the anterior tibial plafond. Its fibular insertion was 4.4 ± 1.7 mm superior and posterior to the anterior fibular tubercle. The centre of the tibial cartilage facet of the tibiofibular contact zone was 8.4 ± 2.1 mm posterior and superior to the anterior plafond. The proximal and distal aspects of the ITFL tibial attachment were 45.9 ± 7.9 and 12.4 ± 3.4 mm proximal to the central plafond, respectively. The superficial and deep PITFL coursed anterior and distally from the posterior tibia to fibula. On the mortise view, the AITFL tibial attachment centre was 5.6 ± 2.4 mm lateral and superior to the lateral extent of the plafond (4.3 mm lateral, 3.3 mm superior), and its fibular insertion was 21.2 ± 2.1 mm superior and medial to the inferior tip of the lateral malleolus.
Conclusions:
Quantitative radiographic guidelines describing the locations of the primary syndesmotic structures demonstrated excellent reliability and reproducibility. Defined guidelines provide additional clinically relevant information regarding the radiographic anatomy of the syndesmosis and may assist with preoperative planning, augment intraoperative navigation, and provide additional means for objective postoperative assessment.


Related Concept Videos
 01:10
Ankle Joint
 01:09
Functional Classification of Joints
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An...
 01:10
Bones of the Lower Limb: Tibia and Fibula
 01:26
Joints
Structural joint classifications are based on the material that makes up the joint as well as whether or not the joint contains a space between the bones. Joints are structurally classified as fibrous, cartilaginous, or synovial.
Fibrous Joints Are Immovable
The bones of a...
 01:03
Structural Joints: Fibrous Joints
Suture
All the bones of the skull, except for the mandible, are joined to each other by a fibrous joint called a suture. The fibrous connective tissue found at a suture strongly unites the adjacent skull bones and thus helps to protect the brain and form the face. In...