Related Experiment Video
Updated: Apr 5, 2026
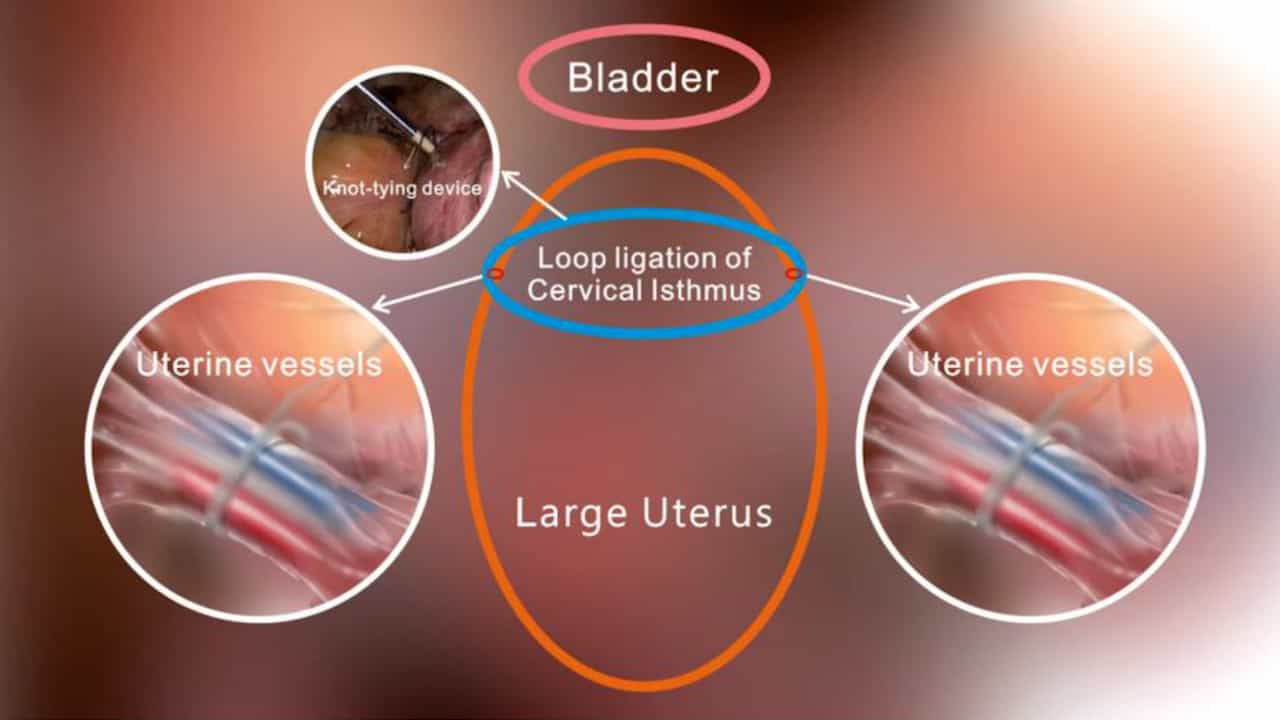
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Uterine exteriorization compared with in situ repair for Cesarean delivery: a systematic review and meta-analysis
Valerie Zaphiratos1, Ronald B George2, J Colin Boyd3
1Maisonneuve-Rosemont Hospital, University of Montreal, Montreal, QC, Canada.

Purpose:
To compare perioperative outcomes following uterine exteriorization vs in situ repair after Cesarean delivery.
Source:
We searched CENTRAL, MEDLINE®, EMBASE™, CINAHL, and ClinicalTrials.gov for randomized clinical trials that included any of our primary outcomes (blood loss, intraoperative nausea, vomiting, and pain), or secondary outcomes.
Principal Findings:
Sixteen studies were included. In total, 9,736 subjects underwent exteriorization, 9,703 had in situ uterine repair. Estimated blood loss was not statistically different between the two methods of uterine repair (mean difference [MD], -61.03 mL; 95% confidence interval [CI], -127.34 to 5.28); however, exteriorization reduced the decrease in hemoglobin (MD, -0.14 g·dL(-1); 95% CI, -0.22 to -0.07). Estimated blood loss was reduced with exteriorization in a sensitivity analysis that excluded an outlier study. There was no statistically significant difference in intraoperative nausea (odds ratio [OR], 0.99; 95% CI, 0.74 to 1.34), vomiting (OR, 0.94; 95% CI, 0.66 to 1.35), or pain (OR, 1.52; 95% CI, 0.86 to 2.71) between the two repair techniques. In situ repair was associated with faster return of bowel function (MD, 3.09 hr; 95% CI, 2.21 to 3.97). An association between exteriorization and endometritis did not reach statistical significance (OR, 1.25; 95% CI, 0.96 to 1.62).
Conclusion:
Uterine repair by exteriorization may reduce blood loss and the associated decrease in hemoglobin, but the difference may not be clinically relevant. There was no statistically significant difference between the two repair techniques for intraoperative nausea, vomiting, or pain. In situ repair may be associated with a faster return of bowel function.