Related Experiment Video
Updated: Apr 5, 2026
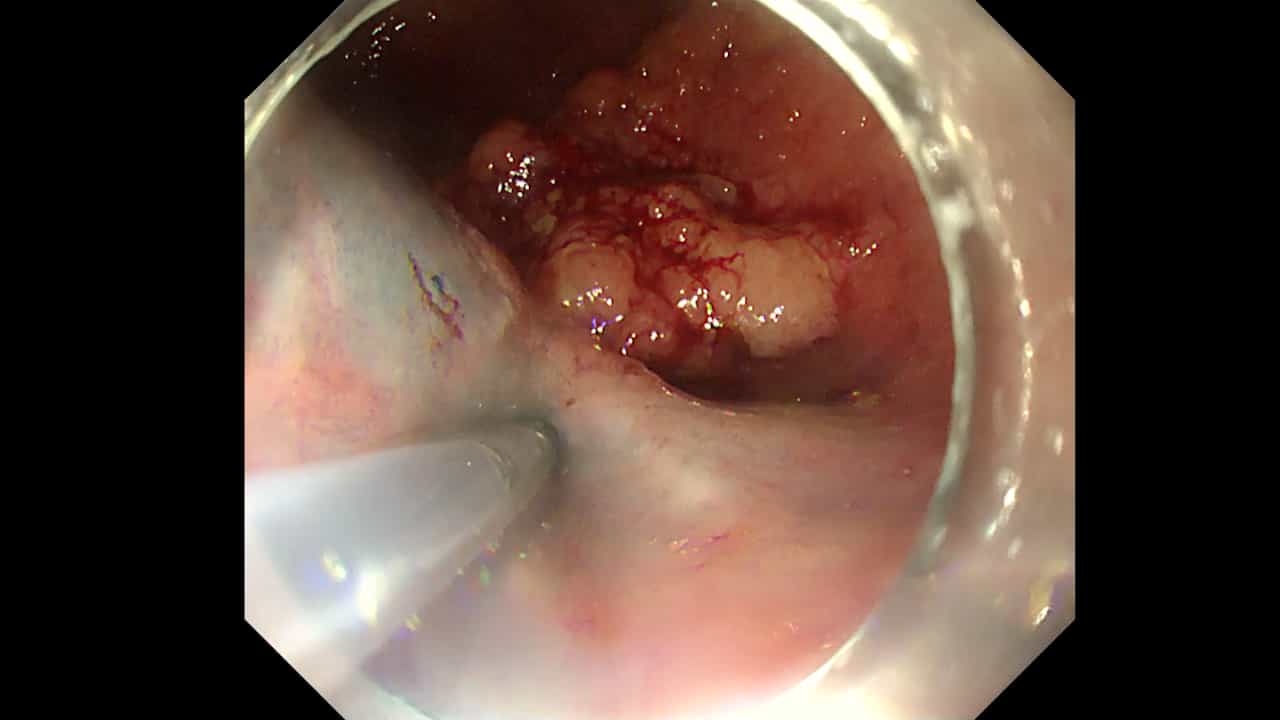
The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Preoperative indicators of failure of en bloc resection or perforation in colorectal endoscopic submucosal
Kenichiro Imai1, Kinichi Hotta1, Yuichiro Yamaguchi1
1Division of Endoscopy, Shizuoka Cancer Center, Shizuoka, Japan.

Background And Aims:
The technical difficulties inherent in endoscopic submucosal dissection (ESD) for colorectal neoplasms may result in the failure of en bloc resection or perforation. The aim of this retrospective study was to assess the predictors of en bloc resection failure or perforation by using preoperatively available factors.
Methods:
Between September 2002 and March 2013, 716 colorectal ESDs in 673 consecutive patients were performed at a tertiary cancer center. Patient characteristics, tumor location, tumor type, colonoscopy-related factors, and endoscopist experience were assessed based on a prospectively recorded institutional ESD database. Logistic regression analysis was performed to identify predictors of failure of en bloc resection or perforations, with subgroup analyses of ESDs performed by endoscopists less experienced in colorectal ESD (<40 cases) and for colonic lesions only.
Results:
On multivariate analysis, independent predictors of failure of en bloc resection or perforations were the presence of fold convergence (odds ratio [OR] 4.4; 95% confidence interval [95% CI], 1.9-9.9), protruding type (OR 3.6; 95% CI, 1.8-7.1), poor endoscope operability (OR 3.5; 95% CI, 1.8-6.9), right-sided colonic lesions (OR 3.0; 95% CI, 1.5-6.3 vs rectal lesions), left-sided colonic lesions (OR 3.2; 95% CI, 1.7-6.3, vs rectal lesions), the presence of an underlying semilunar fold (OR 2.1; 95% CI, 1.3-3.6), and a less-experienced endoscopist (OR 2.1; 95% CI, 1.3-3.6). Among less-experienced endoscopists, colonic lesions were independent predictors (right-sided colonic lesions 8.1; 95% CI, 2.9-25.1; left-sided colonic lesions 8.1; 95% CI, 2.5-28.3 vs rectal lesions). For colonic lesions, the presence of fold convergence (OR 3.7; 95% CI, 1.6-8.6), poor endoscope operability (OR 3.6; 95% CI, 1.8-7.2), a less-experienced endoscopist (OR 3.0; 95% CI, 1.7-1.8), and the presence of an underlying semilunar fold (OR 2.7; 95% CI, 1.5-4.7) were identified predictors.
Conclusion:
This study successfully identified predictors of en bloc resection failure or perforation. Understanding these indicators could help to accurately stratify lesions according to technical difficulty and to appropriately select endoscopists.
More Related Videos
 08:26
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
 15:49
Flexible Colonoscopy in Mice to Evaluate the Severity of Colitis and Colorectal Tumors Using a Validated Endoscopic Scoring System
Published on: October 16, 2013
Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:25
Endoscopic Procedures II: Colonoscopy