Related Experiment Video
Updated: Apr 5, 2026


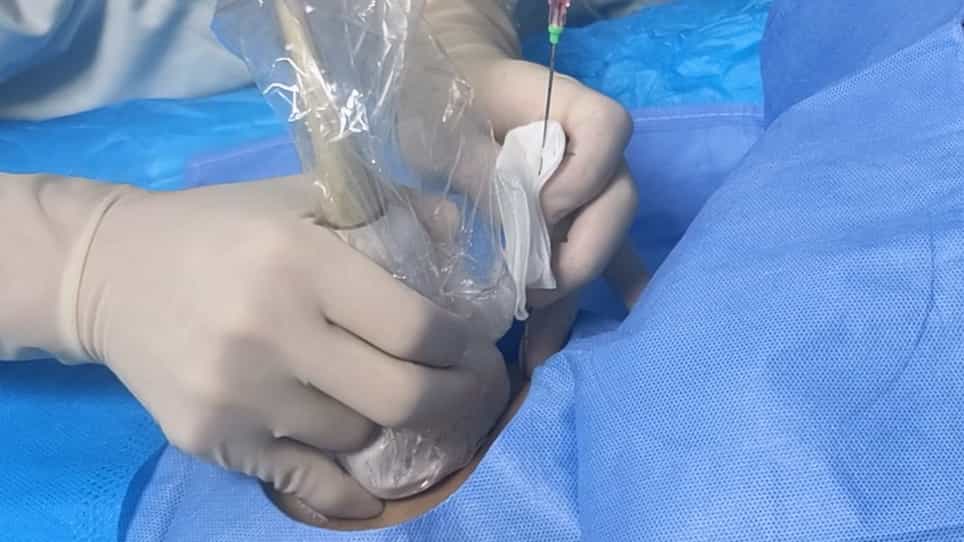
Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
[Is suprastenotic dilatation a mandatory symptom of impaired bile outflow?]

Objective:
To study the rate, nature, and symptoms of bile flow impairments running without developing suprastenotic dilatation.
Material And Methods:
A total of 1082 patients undergoing endoscopic retrograde cholangiopancreatography for the differential diagnosis of jaundices were followed up. According to the diameter of the common bile duct, the patients were classified into cholangioectasia and non-cholangioectasia groups. The investigators studied the causes of bile evacuation disorders; the levels of bilirubin, hepatic transferases, and alkaline phosphatase; the duration and periodicity of obstructive jaundice; extended compression of suprastenotic dilatation; the occurrence of other symptoms; and the efficiency of additional procedures for the differential diagnosis of hepatic and obstructive jaundices.
Results:
There was no suprastenotic dilatation in 11 cases: in noncircular amorphous internal hepatocholedochal blocks, in cicatrical stenoses of the hepatocholedoch, in excessive metastatic spread into the hepatic portal and parenchyma, extended stenosis of the common bile duct does not lead to intrahepatic cholangiectasia. In 9 cases, instrumental palpation and aspiration biopsy were used to visualize common bile duct stenosis in order to elucidate its nature, degree, and rigidity. Endobiliary stenting was employed for the differential diagnosis of jaundices.
Conclusion:
No suprastenotic dilatation was seen in 0.8% of patients with organic bile flow impairment. In these cases, obstacles to bile flow may be suggested by clear-cut variations in the diameter of the hepaticocholedoch and its deformity. The absence of suprastenotic dilatation may be partly explained by excessive metastatic liver involvement and malignant hepatoduodenal ligament infiltration. When suprastenotic dilatation is absent, instrumental palpation and diagnostic and therapeutic stenting may be used for the differential diagnosis of obstructive and hepatic jaundices.
Related Concept Videos
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not...
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:24
Esophageal Varices-I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...