Related Experiment Video
Updated: Apr 5, 2026


Transuterine Fetal Tracheal Occlusion Model in Mice
Published on: February 5, 2021
Differences in mortality and morbidity according to gestational ages and birth weights in infants with trisomy 18
Ken Imai1, Atsushi Uchiyama1, Tomoka Okamura1
1Department of Neonatology, Maternal and Perinatal Center, Tokyo Women's Medical University, Tokyo, Japan.

Insights
Gestational age significantly impacts survival in infants with trisomy 18, with preterm infants having no survival to discharge. Shorter gestational age, more than low birth weight, negatively affects outcomes for these infants.
Area of Science:
- Neonatal Medicine
- Genetics
- Pediatric Cardiology
Background:
- Trisomy 18 (Edwards syndrome) is a severe chromosomal disorder associated with high infant mortality.
- Understanding factors influencing survival in trisomy 18 is crucial for clinical management and parental counseling.
- Gestational age and birth weight are known determinants of neonatal outcomes, but their specific impact in trisomy 18 requires further clarification.
Purpose of the Study:
- To investigate the independent effects of gestational age and birth weight on the survival of infants diagnosed with trisomy 18.
- To compare clinical characteristics and management strategies between term and preterm infants with trisomy 18.
- To identify critical factors predicting survival to discharge in this vulnerable population.
Main Methods:
- Retrospective review of medical records for 36 infants with trisomy 18 admitted between 1991 and 2012.
- Comparison of clinical data between term (gestational age ≥37 weeks) and preterm (gestational age <37 weeks) infants.
- Analysis of outcomes, including survival to discharge, and causes of mortality, stratified by gestational age and birth weight categories (very-low-birth-weight vs. non-VLBW).
Main Results:
- None of the 21 preterm infants survived to discharge, compared to 29% (6/21) of term infants (P < 0.05).
- Very-low-birth-weight (VLBW) status was more prevalent in preterm infants (80%) than term infants (5%).
- Multiple logistic regression indicated that shorter gestational age was a stronger negative predictor of survival to discharge than lower birth weight in trisomy 18 infants.
Conclusions:
- Gestational age is a more critical determinant of survival to discharge in infants with trisomy 18 than birth weight.
- Preterm birth is associated with a significantly poorer prognosis, with no survivors to discharge in this cohort.
- Respiratory failure or apnea were common causes of early mortality (<30 days), while heart failure was more prevalent in later deaths among survivors.
Abstract:
The aim of this study was to clarify the effects of gestational age and birth weight on outcomes of the infants. Medical records of 36 infants with trisomy 18 admitted to Tokyo Women's Medical University Hospital from 1991 to 2012 were reviewed retrospectively. We compared clinical characteristics between term infants (n = 15) and preterm infants (n = 21). There were one very-low-birth-weight (VLBW) term infant (5%) and 12 VLBW preterm infants (80%). Although there were no significant differences in clinical characteristics and provided management between the two groups, none of the preterm infants achieved survival to discharge. On the other hand, 6 of 21 term infants (29%) achieved survival to discharge (P < 0.05). Similar results were obtained for comparisons between the VLBW infants and non-VLBW infants. Multiple logistic regression analysis revealed that shorter gestational age had a more negative impact than lower birth weight to survival to discharge in infants with trisomy 18. In both preterm and term groups, the infants who died before 30 days commonly died of respiratory failure or apnea. Whereas, the infants who survived more than 30 days mostly died of heart failure.


Related Concept Videos
 02:57
Meiosis vs. Mitosis
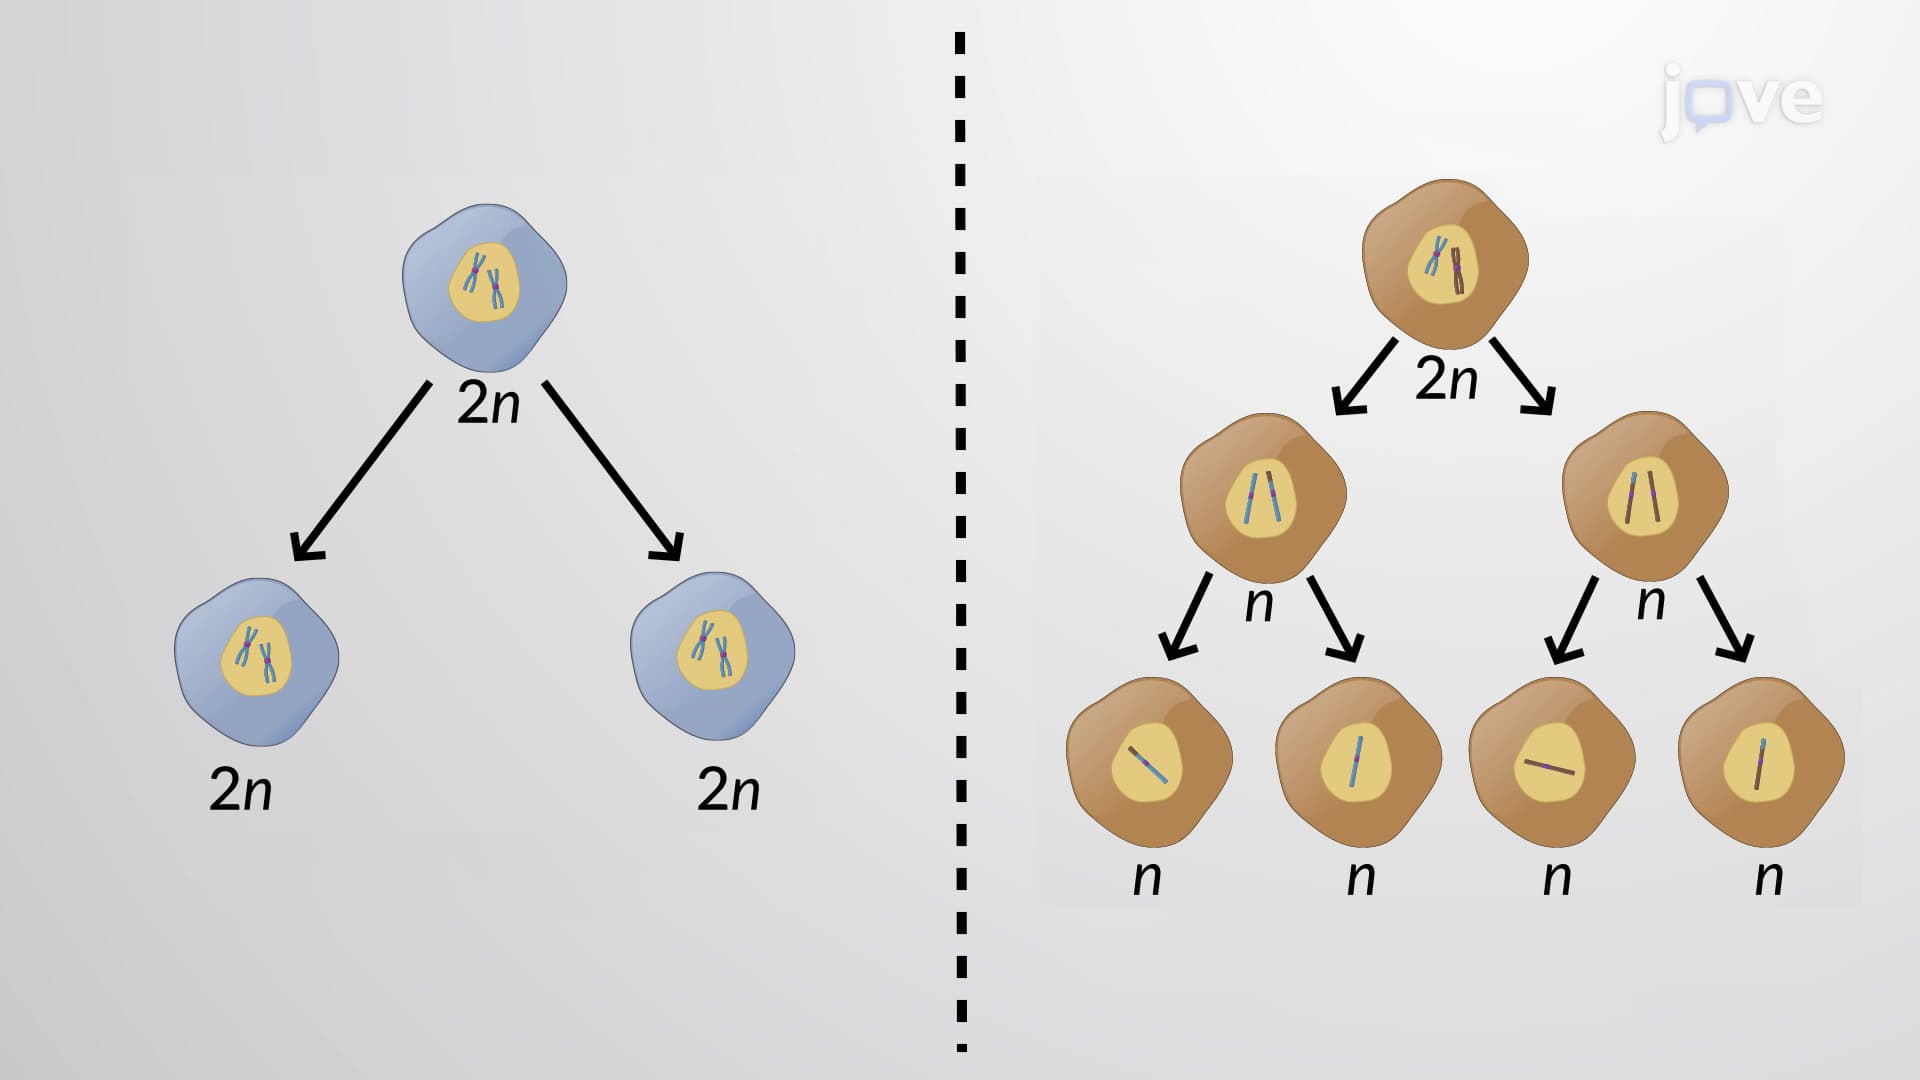
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...
 01:07
Teratogenicity
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:52
Regression Toward the Mean
 01:49
Meiosis I