Related Experiment Video
Updated: Apr 3, 2026

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Evaluation of stroke volume variation and pulse pressure variation as predictors of fluid responsiveness in patients
Qiang Fu1, Mingda Duan, Feng Zhao
1Department of Anesthesiology, General Hospital of People's Liberation Army.

Abstract:
In order to investigate whether the hemodynamic indices, including stroke volume variation (SVV) and pulse pressure variation (PPV) could predict fluid responsiveness in patients undergoing protective one-lung ventilation. 60 patients scheduled for a combined thoracoscopic and laparoscopic esophagectomy were enrolled and randomized into two groups. The patients in the protective group (Group P) were ventilated with a tidal volume of 6 mL/kg, an inspired oxygen fraction (FiO2) of 80%, and a positive end expiratory pressure (PEEP) of 5 cm H2O. Patients in the conventional group (Group C) were ventilated with a tidal volume of 8 mL/kg and a FiO2 of 100%. Dynamic variables were collected before and after fluid loading (7 mL/kg hydroxyethyl starch 6%, 0.4 mL/kg/min). Patients whose stroke volume index (SVI) increased by more than 15% were defined as responders. Data collected from 45 patients were finally analyzed. Twelve of 24 patients in Group P and 10 of 21 patients in Group C were responders. SVV and PPV significantly changed after the fluid loading. The receive operating characteristic (ROC) analysis showed that the thresholds for SVV and PPV to discriminate responders were 8.5% for each, with a sensitivity of 66.7% (SVV) and 75% (PPV) and a specificity of 50% (SVV) and 83.3% (PPV) in Group P. However, the thresholds for SVV and PPV were 8.5% and 7.5% with a sensitivity of 80% (SVV) and 90% (PPV) and a specificity of 70% (SVV) and 80% (PPV) in Group C. We found SVV and PPV could predict fluid responsiveness in protective one-lung ventilation, but the accuracy and ability of SVV and PPV were weak compared with the role they played in a conventional ventilation strategy.
Related Concept Videos
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:15
Respiratory Volumes
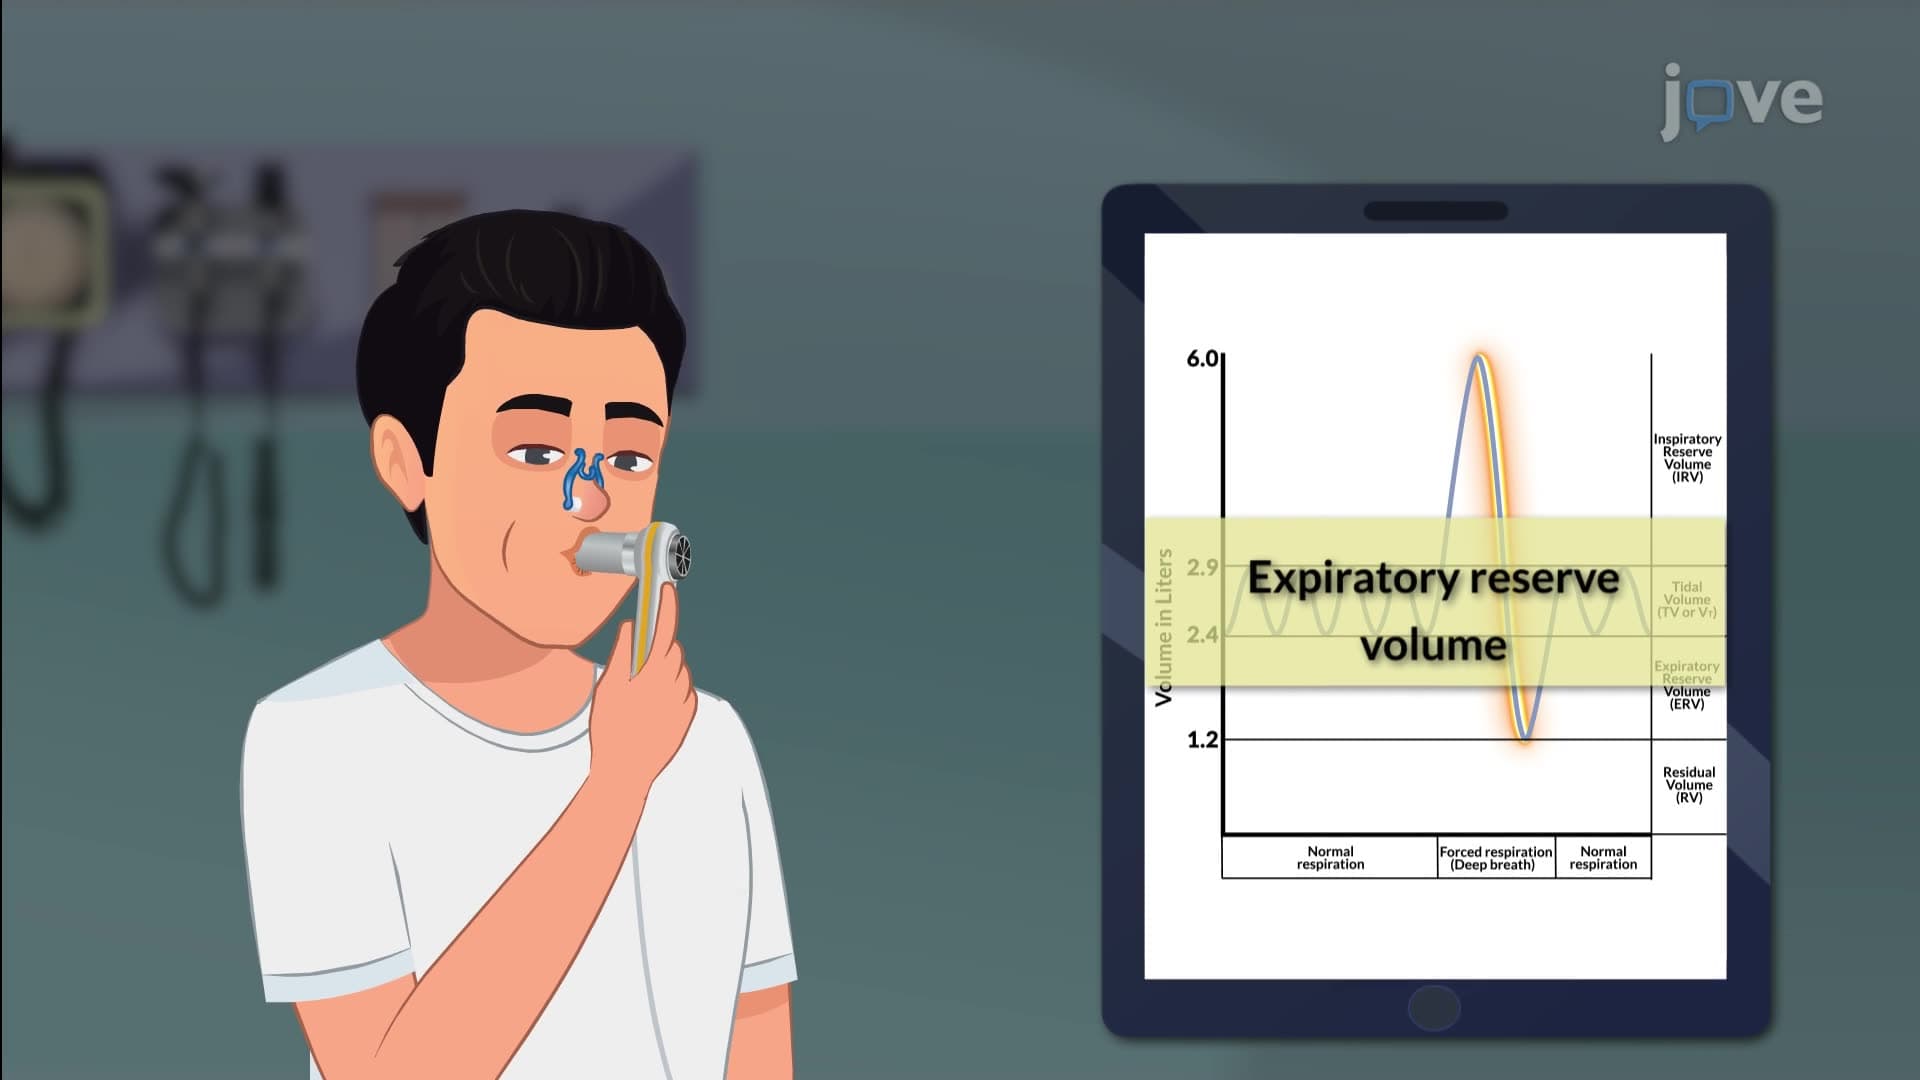
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: