Related Experiment Video
Updated: Apr 3, 2026
Author Spotlight: Genetic Profiling for Fluorouracil Response in Gastric Cancer
Published on: May 10, 2024
Mutation in the Monocarboxylate Transporter 12 Gene Affects Guanidinoacetate Excretion but Does Not Cause Glucosuria
Nasser Dhayat1, Alexandre Simonin2, Manuel Anderegg3
1Division of Nephrology, Hypertension and Clinical Pharmacology, and Department of Clinical Research, University of Bern, Switzerland;

Abstract:
A heterozygous mutation (c.643C>A; p.Q215X) in the monocarboxylate transporter 12-encoding gene MCT12 (also known as SLC16A12) that mediates creatine transport was recently identified as the cause of a syndrome with juvenile cataracts, microcornea, and glucosuria in a single family. Whereas the MCT12 mutation cosegregated with the eye phenotype, poor correlation with the glucosuria phenotype did not support a pathogenic role of the mutation in the kidney. Here, we examined MCT12 in the kidney and found that it resides on basolateral membranes of proximal tubules. Patients with MCT12 mutation exhibited reduced plasma levels and increased fractional excretion of guanidinoacetate, but normal creatine levels, suggesting that MCT12 may function as a guanidinoacetate transporter in vivo However, functional studies in Xenopus oocytes revealed that MCT12 transports creatine but not its precursor, guanidinoacetate. Genetic analysis revealed a separate, undescribed heterozygous mutation (c.265G>A; p.A89T) in the sodium/glucose cotransporter 2-encoding gene SGLT2 (also known as SLC5A2) in the family that segregated with the renal glucosuria phenotype. When overexpressed in HEK293 cells, the mutant SGLT2 transporter did not efficiently translocate to the plasma membrane, and displayed greatly reduced transport activity. In summary, our data indicate that MCT12 functions as a basolateral exit pathway for creatine in the proximal tubule. Heterozygous mutation of MCT12 affects systemic levels and renal handling of guanidinoacetate, possibly through an indirect mechanism. Furthermore, our data reveal a digenic syndrome in the index family, with simultaneous MCT12 and SGLT2 mutation. Thus, glucosuria is not part of the MCT12 mutation syndrome.
More Related Videos
 09:34
Targeted Next-generation Sequencing and Bioinformatics Pipeline to Evaluate Genetic Determinants of Constitutional Disease
Published on: April 4, 2018
 08:04
Identification and Classification of Position-specific GABAA Receptor Subunit Missense Variants for Their Role In Hippocampal Pyramidal Neurons
Published on: June 6, 2025
Related Concept Videos
 01:16
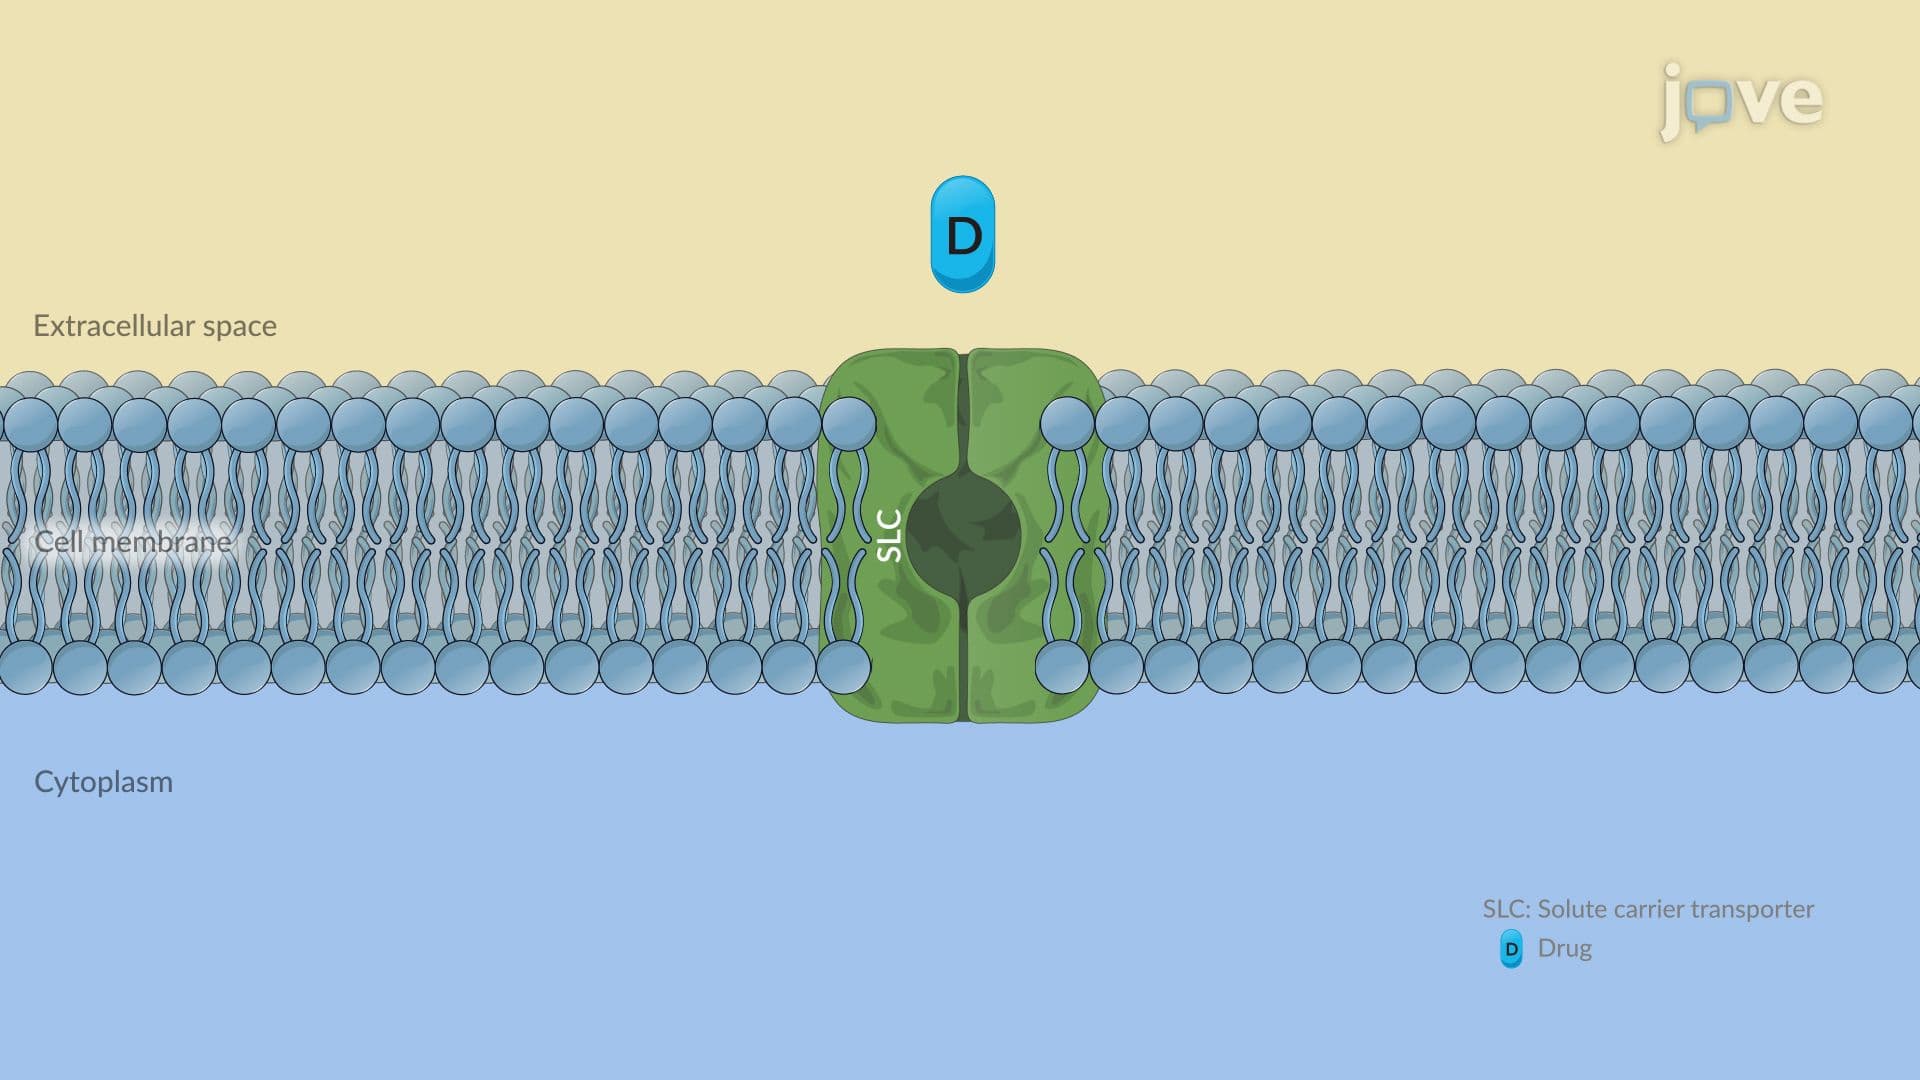
Pharmacogenetics of Drug Transporters: P-Glycoprotein and Solute Carrier Transporters
 01:27
Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase
 01:11
Pharmacogenetics of Drug Targets: β₂-Adrenergic Receptors, Apo E, Thymidylate Synthase
 01:27
Glucose Transporters
Facilitated diffusion-glucose transporters (GLUTs) are encoded by the solute-linked carrier (SLC) family 2, subfamily A gene family, or SLC2A. The 14 GLUT protein members are distributed into three classes:
 01:15
Drug Elimination by Renal Route: Tubular Secretion
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu